1.1.1 - Primary Care NP Scope
Why it matters
- Many board questions are not testing rare diseases; they are testing whether you choose the safest action within role for the child in front of you.
- Wrong answers are often tempting because they are medically reasonable in a different setting, such as the ED, inpatient unit, or subspecialty clinic.
- Scope errors on exam day usually come from missing one clue: instability, age-inappropriateness, legal risk, or need for escalation.
- Strong scope recognition improves every later topic in this course because it tells you whether the task is to manage, monitor, counsel, refer, or transfer.
Key Terms & Must-Know Facts
1.1.1.1 Key terms
- Scope of practice: The set of patient care activities appropriate to the pediatric primary care NP role.
- Primary care setting: Outpatient and community-based care, including well visits, sick visits, follow-up, and triage.
- Disposition: The safest next location and level of care.
- Red flag: A finding that raises concern for instability, serious disease, abuse, or urgent deterioration.
- Stabilize and refer: Initial within-office safety actions followed by appropriate transfer or consultation.
- Age-based decision-making: Choosing actions based on developmental stage and pediatric norms.
- Family-centered care: Care that integrates caregiver perspective, education, and shared planning.
- Mandated reporting: Required reporting of suspected abuse or neglect.
- Confidential adolescent care: Developmentally appropriate privacy within legal and safety limits.
- Ambulatory diagnostics: Tests commonly ordered or interpreted in outpatient pediatric practice.
- Urgent referral: Same-day escalation when office care is not sufficient.
- Emergency transfer: Immediate EMS or ED referral for instability or high-risk findings.
1.1.1.2 Must-know facts
- The exam expects you to act as a pediatric primary care NP, not as a hospitalist, intensivist, surgeon, or subspecialist.
- The safest exam answer often prioritizes recognition of severity before disease labeling.
- Office management is appropriate only when the child is stable and the problem fits routine outpatient care.
- Age matters: normal findings, screening choices, medication safety, and urgency all shift by age band.
- Primary care scope includes prevention, screening, growth/development surveillance, common acute illness care, chronic follow-up, and caregiver education.
- Primary care scope does not include inpatient management plans, operative decisions, ventilator management, or specialty-only procedures.
- When local rules vary, the exam-safe principle is to follow current official guidance and stay within jurisdictional scope.
- If abuse, suicidality, respiratory distress, sepsis concern, severe dehydration, or altered mental status is present, escalation outranks routine office completion.
Exam takeaway: Separate outpatient management from urgent escalation by asking whether the child is stable and whether the needed intervention is available in primary care.
flowchart TD
A[Question stem] --> B{Stable child?}
B -- No --> C[Emergency evaluation or EMS]
B -- Yes --> D{Fits routine pediatric primary care?}
D -- Yes --> E[Assess, manage, counsel, follow up]
D -- No --> F[Consult or refer]
F --> G{Needs same-day action?}
G -- Yes --> H[Urgent referral]
G -- No --> I[Planned specialty follow-up]
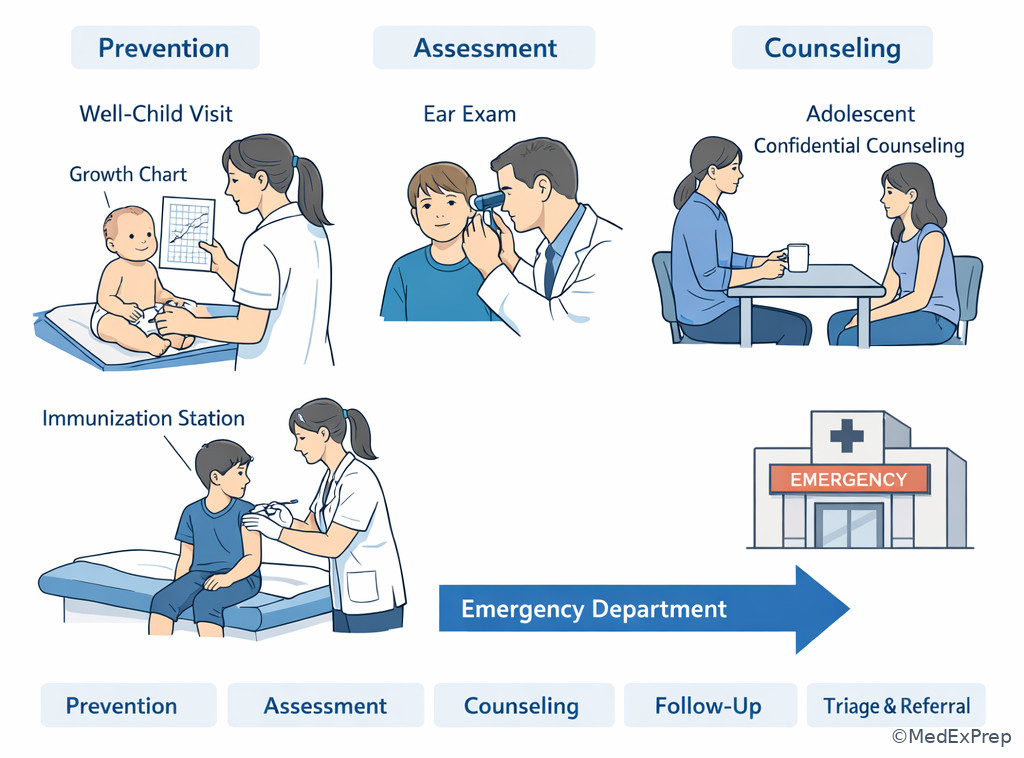
Use this frame repeatedly across the course. See Fig 1.
Exam takeaway: Visualize the clinic-based role as prevention, assessment, education, monitoring, and referral rather than hospital-level intervention.
Core content
1.1.1.3 Foundational scope: what the pediatric primary care NP is expected to do
A Explanation
The first decision conflict is simple but heavily tested: Is this a routine outpatient pediatric problem that can be assessed and managed longitudinally, or is the stem pushing you beyond primary care scope? The resolving rule is this: choose the answer that matches clinic-based, age-appropriate, family-centered care for stable patients. Reject answers that assume inpatient resources, specialty-only diagnostics, or advanced resuscitation authority.
Core scope includes health supervision, developmental surveillance, immunization counseling, common acute visit assessment, common chronic follow-up, medication safety, caregiver teaching, and outpatient monitoring. It also includes recognizing when a problem exceeds office capability. WHY THIS IS TESTED: the exam often gives one very detailed option that sounds clinically sophisticated but actually belongs to the ED or inpatient unit, not pediatric primary care.
Choose actions such as focused history and exam, age-based interpretation, routine screening, basic ambulatory testing, initial supportive care, education, and scheduled reassessment. Reject actions such as managing ventilator settings, directing inpatient admission plans, determining operative approach, or independently running a subspecialty treatment pathway.
B Worked example
A 7-year-old with mild persistent asthma and allergic rhinitis presents for cough for 2 days. He is eating less but still drinking, has a temperature of 37.8°C, oxygen saturation 98% on room air, mild end-expiratory wheeze, and no retractions. His mother reports “he probably needs a chest CT because his cousin had pneumonia.” He also had one episode of emesis after coughing. The task is the most appropriate next step in a primary care office.
Reasoning chain: Identify task: outpatient acute management, not hospital stabilization. Extract key facts: stable vitals, normal oxygenation, mild wheeze, no distress, common comorbidity pattern. Apply rule: stable child with common ambulatory problem stays in primary care scope. Eliminate distractors: chest CT is tempting because of caregiver anxiety and cough, but it is not first-line and exceeds routine need here. Hospital admission planning is wrong because the child is not unstable. Verify: focused asthma/viral assessment, office-appropriate treatment, education, and follow-up fit scope.
C Exam trap
Why it is tempting: Test-takers often equate more testing with safer care, especially when the parent is worried or the child has a chronic condition.
Single clue that eliminates it: The child is stable, oxygenating well, and the problem is a common outpatient presentation.
D Checkpoint
Question: A 10-year-old presents for follow-up of constipation. He has autism spectrum disorder and obesity. His mother asks whether the clinic can arrange inpatient bowel cleanout today because he has not stooled in 4 days. He is afebrile, playful, hydrated, and has a soft abdomen without guarding. Which action is most appropriate?
- Develop an outpatient bowel regimen, provide caregiver teaching, and arrange follow-up.
- Arrange direct inpatient management for bowel cleanout from the clinic.
- Order urgent abdominal CT to exclude surgical abdomen.
- Delay intervention until the child develops vomiting or fever.
- A: Tempting because it seems simple; correct because stable functional constipation belongs in outpatient primary care management.
- B: Tempting because stool burden can sound severe; wrong because no instability or red flags justify hospital-level disposition.
- C: Tempting because abdominal imaging feels definitive; wrong because the exam lacks peritoneal signs or acute abdomen features.
- D: Tempting if you want more diagnostic certainty; wrong because delaying treatment ignores an appropriate office-based management opportunity.
1.1.1.4 Foundational boundary line: what must be escalated, referred, or transferred
A Explanation
The next decision conflict is manage here versus escalate now. The single finding/rule that resolves it is instability or high-risk red flags. Pediatric primary care NPs are expected to recognize danger early, begin office-appropriate stabilization within capability, and secure a higher level of care. The exam rewards prompt escalation; it penalizes overconfident in-office management when the child is ill-appearing or the condition is time-sensitive.
Escalate for respiratory distress, oxygenation concerns, severe dehydration, altered mental status, concern for sepsis, anaphylaxis, suspected abuse, mental health crisis, severe abdominal findings, or any condition needing hospital-only resources. This is not “doing less”; it is the safest scope-appropriate action. WHY THIS IS TESTED: stems often include a child with just enough detail to tempt office treatment, but one red flag changes the entire answer.
Choose-vs-reject framing helps: choose emergency transfer when the problem threatens airway, breathing, circulation, neurologic status, or safety. Choose urgent same-day referral when the child is stable but needs specialty, ED, or hospital assessment beyond primary care resources. Reject routine follow-up when time-sensitive deterioration is plausible.
Exam takeaway: The correct answer often depends more on disposition urgency than on naming the exact diagnosis.
flowchart LR
A[Clinic/triage contact] --> B{Stable?}
B -- No --> C[EMS or ED now]
B -- Yes --> D{Needs resources beyond office?}
D -- Yes, same day --> E[Urgent referral/ED]
D -- Yes, not same day --> F[Specialty referral]
D -- No --> G[Outpatient management + follow-up]
Disposition is a high-yield exam skill. See Fig 2.
B Worked example
A 3-month-old with a history of prematurity and reflux is brought for “poor feeding and cough.” He has nasal flaring, subcostal retractions, a respiratory rate of 68/min, and oxygen saturation of 90% on room air. His grandmother also mentions he has mild cradle cap, which is distracting but irrelevant. The most appropriate next step is not to optimize outpatient reflux care. The reasoning chain is: identify task as disposition; extract key facts of age, distress, hypoxemia, and tachypnea; apply rule that instability overrides routine office management; eliminate distractors such as same-day recheck or oral feeding trial; verify that urgent emergency evaluation/EMS activation is indicated.
C Exam trap
Why it is tempting: In many primary care stems, supportive care and close follow-up are exactly right.
Single clue that eliminates it: Objective respiratory distress with low oxygen saturation changes the setting from routine outpatient care to emergency escalation.
D Checkpoint
Question: A 15-year-old with depression and migraine presents for headache follow-up. During the visit she discloses current suicidal thoughts with a plan and says she does not want her parent told. Which action is most appropriate?
- Maintain confidentiality because adolescent privacy is generally protected.
- Complete routine headache counseling and schedule close follow-up next week.
- Initiate immediate safety assessment and urgent emergency mental health evaluation.
- Refer to outpatient counseling without involving the parent today.
- A: Tempting because confidentiality is an important adolescent principle; wrong because imminent safety risk overrides routine privacy limits.
- B: Tempting because headache was the original reason for visit; wrong because the new safety issue is higher priority.
- C: Tempting because it is more intensive; correct because suicidal ideation with plan requires immediate escalation.
- D: Tempting because counseling is appropriate long term; wrong because outpatient referral alone is insufficient for active danger.
- The most common reason to leave routine scope on exam stems is a red flag affecting disposition.
- True or False: A stable child who needs a subspecialty procedure but not immediate stabilization usually needs planned referral, not emergency transfer. True.
- Name 3 escalation triggers: respiratory distress, altered mental status, imminent safety risk.
1.1.1.5 Applied scope in everyday pediatric primary care: prevention, common illness, and follow-up
A Explanation
Once you know the child is stable and the problem fits outpatient care, the decision conflict becomes what is the NP expected to own longitudinally? The rule: primary care scope is broad in prevention and common ambulatory problems. It includes growth and development review, age-based screening, immunization counseling, common acute illness management, chronic condition follow-up, medication teaching, and return precautions.
This is where many learners under-call their role. The exam does expect you to make practical clinic decisions: which screening fits age, what counseling matters now, what follow-up interval is safe, and when a common problem can be treated without referral. WHY THIS IS TESTED: candidates sometimes defer too much because they are worried about overstepping. The correct answer is often an evidence-based outpatient plan with education, not unnecessary referral.
Choose management that includes assessment, action, family guidance, and monitoring. Reject answers that stop at diagnosis labeling without practical follow-up. In pediatric primary care, safe care nearly always includes caregiver instructions, developmental context, and a return plan.
Exam takeaway: Match the visit task to the child's age band to narrow the most appropriate outpatient action.
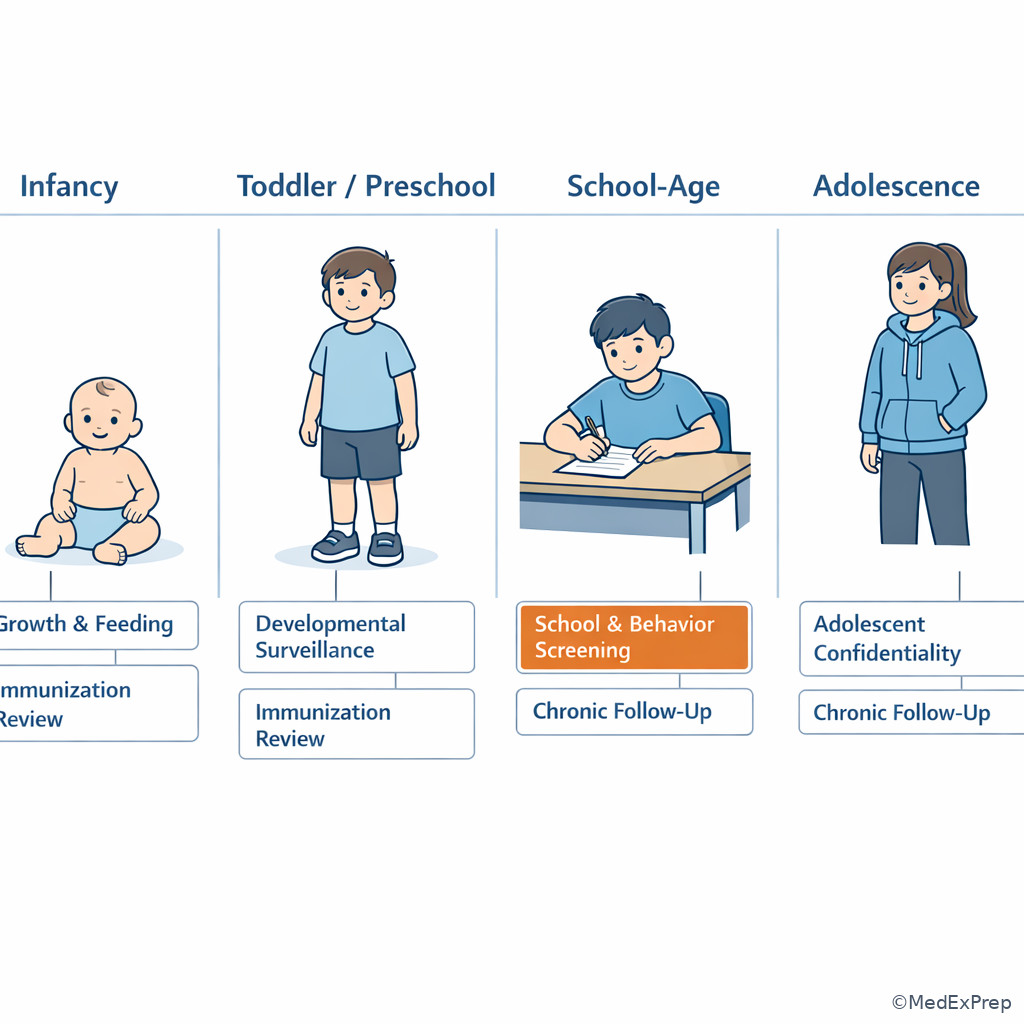
Age band is not decoration; it changes normal findings, screenings, counseling, and disposition thresholds. See Fig 3.
B Worked example
An 18-month-old with eczema and a history of prematurity comes for a well visit. The father is worried that the child “still hates vegetables” and asks for a GI referral. The child is growing along prior percentiles, has normal energy, a normal exam, and no vomiting or diarrhea. A recent cousin’s celiac diagnosis is a tempting-but-wrong clue. Reasoning chain: identify task as preventive primary care. Extract key facts: age 18 months, stable growth, no alarm GI symptoms, typical feeding concern. Apply rule: primary care scope includes nutrition counseling, growth interpretation, developmental surveillance, and follow-up. Eliminate referral because there are no red flags. Verify: provide anticipatory guidance, monitor growth, address picky eating within primary care.
C Exam trap
Why it is tempting: Family worry and family history can make routine issues sound pathologic.
Single clue that eliminates it: Normal growth trajectory and absence of alarm features support primary care counseling and monitoring.
D Checkpoint
Question: A 12-year-old with ADHD and obesity presents for routine follow-up. Blood pressure is mildly elevated on one reading, she is due for immunization review, and her parent asks whether the NP should “wait for a specialist before discussing diet and activity.” Which action is most appropriate?
- Provide age-appropriate counseling, reassess the elevated reading properly, and continue primary care follow-up.
- Defer all counseling until subspecialty evaluation is complete.
- Refer immediately for inpatient blood pressure workup.
- Focus only on ADHD symptoms because that is the chronic diagnosis already established.
- A: Tempting because it requires doing several routine tasks; correct because preventive counseling and reassessment fit longitudinal primary care scope.
- B: Tempting when a family requests specialist input; wrong because primary care should not withhold basic counseling and monitoring.
- C: Tempting because hypertension can be important; wrong because one mildly elevated reading in a stable child does not require inpatient evaluation.
- D: Tempting because ADHD is the scheduled focus; wrong because primary care visits often address multiple preventive issues safely.
1.1.1.6 Integration: role limits in testing, treatment intensity, and consultation
A Explanation
Another common exam conflict is how much testing or treatment intensity is appropriate before referral? The single rule is proportionality: in pediatric primary care, choose the least invasive, guideline-consistent outpatient step that safely answers the clinical question. Reject specialty-only or hospital-level intensity when a focused outpatient approach is sufficient.
This section is not about doing too little. It is about sequencing. A stable child with common symptoms usually gets a focused evaluation, not an exhaustive workup. A child with a likely office-manageable condition receives first-line care and monitoring, not escalation just because the diagnosis sounds important. Conversely, if the workup or treatment required is beyond office resources, referral is appropriate. WHY THIS IS TESTED: many distractors are “technically useful eventually” but wrong as the next step.
Choose-vs-reject examples: choose point-of-care or common outpatient labs when they inform immediate primary care management; reject subspecialty diagnostics not needed to make the next safe decision. Choose first-line education and follow-up for stable chronic issues; reject tertiary care plans that bypass the primary care role.
Exam takeaway: Choose the lowest-intensity safe next step that fits outpatient pediatric primary care, then escalate only if the child's condition or required resources demand it.
flowchart TB
A[Need a decision today] --> B[Focused history and exam]
B --> C{Can routine outpatient test or treatment answer it?}
C -- Yes --> D[Use primary care step]
C -- No --> E[Consult or refer]
D --> F{Improving?}
F -- Yes --> G[Continue follow-up]
F -- No --> E
When two answers both sound medically reasonable, the lower-intensity guideline-consistent outpatient step is often right. See Fig 4.
B Worked example
A 13-year-old with obesity and allergic rhinitis presents for 2 weeks of nasal congestion and cough. She has normal oxygen saturation, no fever, clear lungs, and no facial swelling. Her parent requests “the strongest antibiotic” because school testing is next week. There is also a distracting history of one prior pneumonia 3 years ago. Reasoning chain: identify the task as outpatient management of a common complaint. Extract key facts: stable, no severe features, short duration, benign pulmonary exam. Apply rule: primary care should use focused assessment and guideline-consistent management, not treatment intensity driven by request alone. Eliminate inpatient evaluation, imaging, and unnecessarily broad therapy. Verify: office-appropriate symptomatic management and follow-up are within scope.
C Exam trap
Why it is tempting: Family pressure, chronic comorbidities, and remote past serious illness can make escalation feel safer.
Single clue that eliminates it: Current exam and vital signs do not show severity requiring high-intensity testing or treatment.
D Checkpoint
Question: A 6-year-old with eczema and iron deficiency anemia follow-up presents with mild dysuria but is afebrile, well-appearing, and drinking normally. Which action best fits pediatric primary care scope?
- Obtain a focused history/exam and use common outpatient testing as indicated before deciding next steps.
- Arrange direct admission for IV antibiotics because urinary complaints can become serious.
- Order a subspecialty imaging panel before basic outpatient assessment.
- Reassure only and avoid any evaluation because the child is stable.
- A: Tempting because it sounds basic; correct because primary care scope includes ambulatory assessment and common testing for stable complaints.
- B: Tempting because urinary infection matters; wrong because the child lacks instability or severity demanding hospital care.
- C: Tempting because structural causes are possible; wrong because specialty-level workup is not the first outpatient step in this stable presentation.
- D: Tempting because the child looks well; wrong because stable does not mean ignore symptoms requiring standard evaluation.
- The best next step is often the lowest-intensity safe outpatient action.
- True or False: A subspecialty test can still be the wrong answer if it does not change the immediate primary care decision. True.
- Name the sequence: focused assessment → routine outpatient step → reassess → escalate if needed.
1.1.1.7 Integration: legal, ethical, and communication responsibilities within scope
A Explanation
The final high-yield conflict is respect autonomy and confidentiality versus protect safety and meet legal duties. The single rule is this: family-centered and adolescent-sensitive care is expected, but safety, mandated reporting, and urgent risk management override routine confidentiality boundaries. The primary care NP must also communicate clearly about why escalation, reporting, or shared decision-making is required.
This includes informed, developmentally appropriate communication; confidentiality for adolescents when appropriate; mandated reporting for suspected abuse or neglect; culturally responsive care; medication safety teaching; and coordination of follow-up. WHY THIS IS TESTED: exam items often present a communication dilemma, but the real discriminator is whether a safety or legal threshold has been crossed.
Choose actions that preserve trust while meeting duty: explain confidentiality limits up front, involve caregivers when safety requires it, and report suspected maltreatment rather than “waiting for proof.” Reject answers that hide behind privacy, avoid difficult conversation, or delay action until certainty is complete. In primary care, communication is not separate from clinical care; it is part of safe disposition.
Exam takeaway: Confidential care is important, but active self-harm risk, abuse, or immediate danger requires disclosure and escalation.
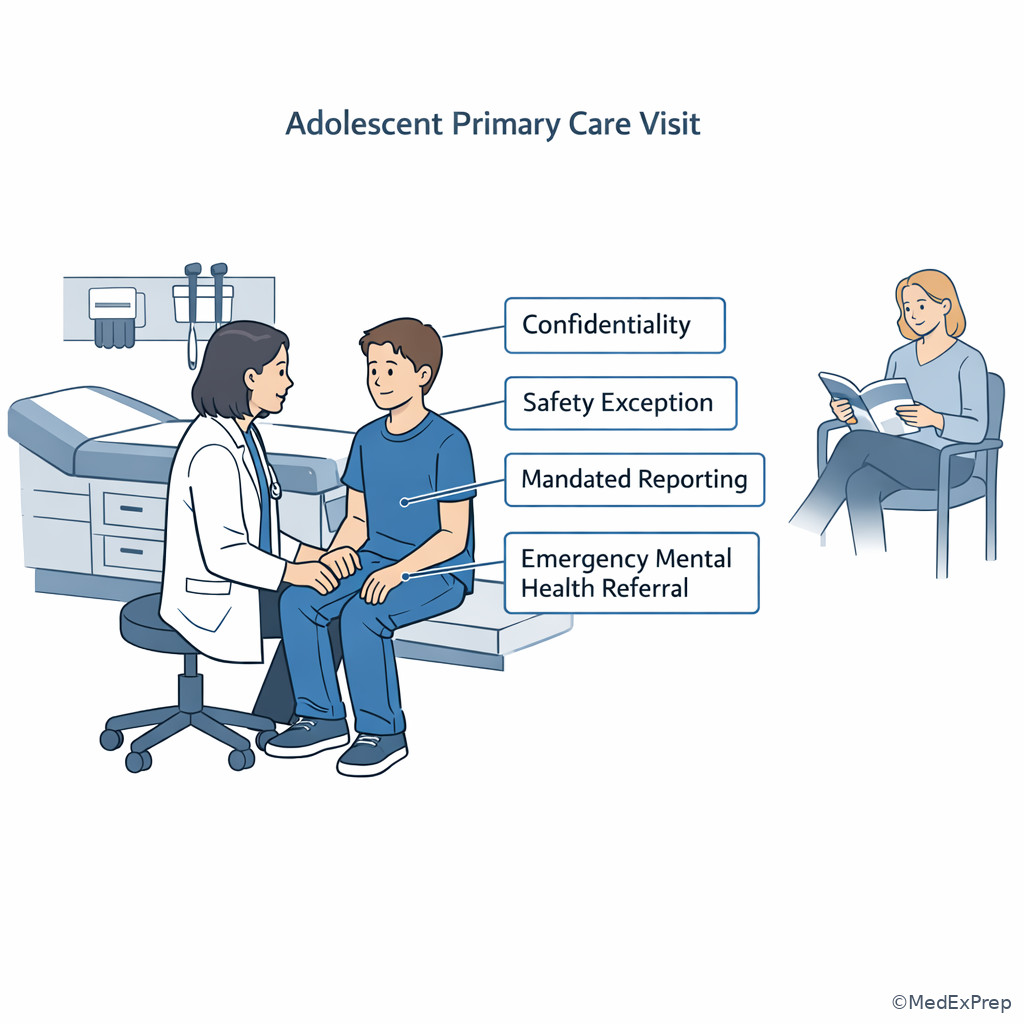
Confidentiality questions are really safety and legal threshold questions. See Fig 5.
B Worked example
A 14-year-old presents for sports clearance with her mother. During confidential discussion, she reports that her mother’s boyfriend “sometimes hits my little brother” and asks the NP not to tell anyone. She also notes mild acne and wants treatment, which is distracting because it is a manageable primary care issue but not the priority. Reasoning chain: identify task as professional/legal action. Extract key facts: disclosure of suspected child abuse in the home, request for secrecy, no need for proof before action. Apply rule: mandated reporting overrides routine confidentiality. Eliminate distractors such as waiting to gather more evidence independently or simply encouraging the teen to tell a parent first. Verify: ensure immediate safety assessment, follow reporting requirements, document objectively, and coordinate next steps.
C Exam trap
Why it is tempting: Learners worry about overreporting or damaging trust with the family.
Single clue that eliminates it: The duty is to report suspicion, not to prove the case before acting.
D Checkpoint
Question: A 16-year-old asks for confidential counseling about sexual health. She denies coercion, suicidal thoughts, and abuse, and she feels safe at home. Which action is most appropriate?
- Refuse any confidential discussion because the parent is in the room.
- Provide developmentally appropriate confidential counseling within legal and clinic guidelines.
- Notify the parent of all details before any counseling begins.
- Refer automatically to a specialist because confidentiality issues are outside primary care scope.
- A: Tempting if you are cautious about consent; wrong because routine adolescent confidential discussion is part of primary care practice.
- B: Tempting because it balances privacy and safety; correct because no immediate danger or legal exception is present in the stem.
- C: Tempting because family involvement can help; wrong because automatic disclosure is not required when no safety exception exists.
- D: Tempting if legal issues feel uncomfortable; wrong because confidential adolescent counseling is a core primary care competency.
Tables
| Primary care NP responsibility | Typical examples | Exam cue |
|---|---|---|
| Preventive care | Well visits, growth review, screening, immunization counseling | Stable child, age-banded tasks, anticipatory guidance needed |
| Common acute illness management | URI care, mild asthma follow-up, constipation, uncomplicated skin concerns | Common complaint without instability |
| Chronic follow-up | ADHD follow-up, obesity counseling, eczema monitoring, asthma check-ins | Longitudinal monitoring and education |
| Common ambulatory testing | Point-of-care tests, routine outpatient labs, common office diagnostics | Test changes clinic decision today |
| Family education and return precautions | Medication teaching, hydration advice, red-flag guidance | Board stems ask for best next step plus follow-up plan |
| Referral/consultation recognition | Specialty referral, urgent same-day evaluation, ED transfer | Beyond office resources or unstable child |
| Setting choice | Choose when | Reject when | Typical wording in stems |
|---|---|---|---|
| Routine outpatient management | Stable, common problem, no red flags | Any ABC compromise or immediate danger | “Most appropriate next step in clinic” |
| Urgent same-day referral | Stable but needs resources beyond office capability | If child is actively unstable and needs emergency transfer | “Requires urgent evaluation today” |
| Emergency department / EMS | Respiratory distress, severe dehydration, altered status, safety crisis | Stable minor illness | “Immediate evaluation” or “most appropriate disposition” |
| Planned specialty referral | Persistent problem needing nonurgent subspecialty input | When first-line primary care steps have not yet been tried without reason | “Follow current official guidance and coordinate care” |
| Look-alike scenario | Seems like | Actually is | Single discriminator |
|---|---|---|---|
| Well-appearing child with common complaint | Needs exhaustive workup | Focused outpatient management | Stable vitals and no red flags |
| Teen requesting privacy | Absolute confidentiality | Confidential care with safety exceptions | Presence or absence of imminent risk/abuse |
| Concerning chronic symptom with no instability | Emergency transfer | Urgent or planned specialty referral | Stable child but beyond office resources |
| Parent requests aggressive therapy | Do the strongest option | Use guideline-consistent lowest safe intensity | Current severity, not family pressure |
| Possible maltreatment disclosure | Need proof before acting | Mandated report of suspicion | Duty is triggered by suspicion, not confirmation |
Exam takeaway: Red-flag assessment findings should trigger escalation before routine office problem-solving.
{"prompt":"Clean nursing-education illustration on white background showing pediatric triage escalation: child with respiratory distress signs, pulse oximeter reading low, clinician assessing work of breathing, arrow pathway from clinic room to EMS/ED, labels for retractions, tachypnea, hypoxemia, altered mental status, severe dehydration; realistic ambulatory care style.","caption":"Pediatric triage escalation illustration\nExam takeaway: Red-flag assessment findings should trigger escalation before routine office problem-solving.","size":"1024x1024"} Exam takeaway: In suspected abuse, objective documentation and prompt reporting outrank efforts to personally confirm the diagnosis.
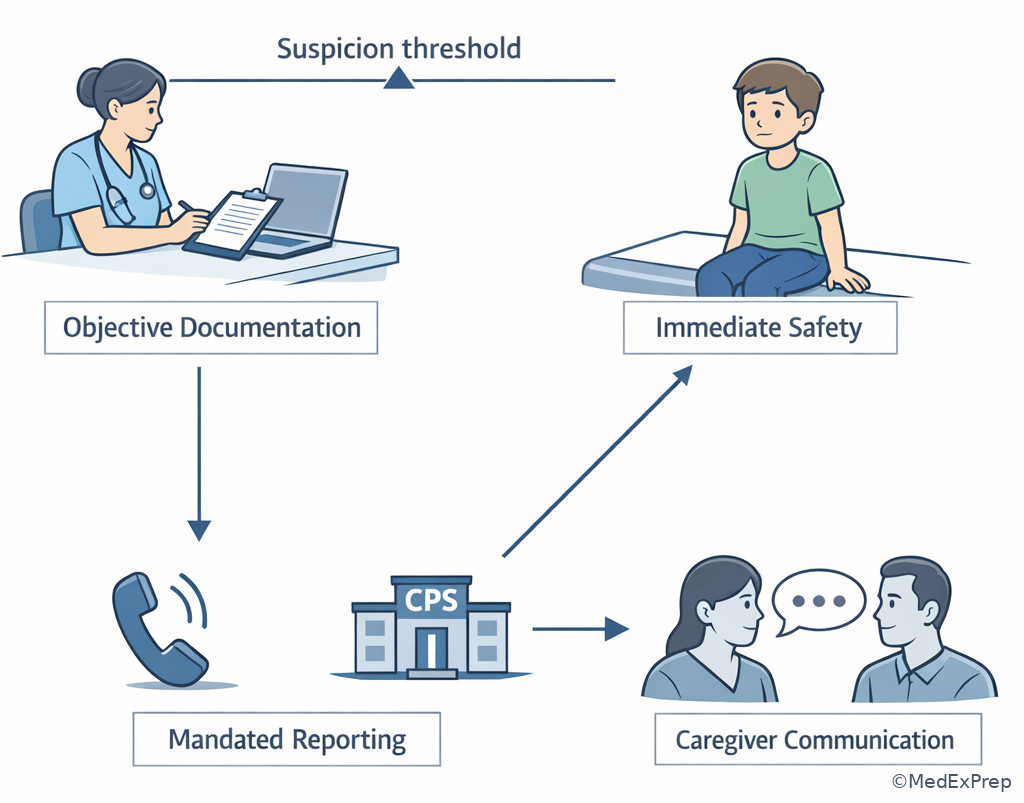
Exam Traps & Differentiators
- Most common wrong answer and why: The “most advanced” intervention. It is tempting because it sounds comprehensive, but the exam usually wants the safest role-appropriate next step.
- Looks similar but isn't: Stable-but-complex is not the same as unstable. A child can have multiple comorbidities and still be appropriate for outpatient management.
- If the stem says low oxygen saturation, severe work of breathing, lethargy, dehydration signs, or suicidal plan, think emergency disposition first.
- If the stem says normal growth, reassuring exam, common complaint, and parent anxiety, think outpatient counseling and follow-up rather than reflex referral.
- If the stem says adolescent asks for privacy but denies safety concerns, think confidential counseling within legal limits.
- If the stem says suspected abuse or neglect, think mandated reporting based on suspicion, not proof.
- If the stem says test or treatment request “because a relative had something serious,” think current child’s presentation drives scope and intensity.
| Stem clue | Think | Avoid |
|---|---|---|
| Stable vital signs, common complaint, no red flags | Manage in primary care | Hospital-level plan |
| Normal growth despite feeding concern | Counsel and monitor | Immediate GI referral without alarm signs |
| Respiratory distress or hypoxemia | Emergency escalation | Trial of routine outpatient reassessment only |
| Teen requests confidentiality with no danger | Private counseling | Automatic disclosure of all details |
| Suicidal plan or abuse concern | Safety exception and escalation | Preserve secrecy or wait for proof |
Exam takeaway: When two options seem reasonable, choose the one that matches the child's severity and the NP's outpatient role.
flowchart TD
A[Two plausible answers] --> B{One assumes hospital/specialty resources?}
B -- Yes --> C{Does the stem show instability or beyond-office need?}
C -- No --> D[Reject aggressive option]
C -- Yes --> E[Choose escalation/referral]
B -- No --> F{Which one adds counseling and follow-up?}
F -- More complete --> G[Prefer that option]
F -- Less complete --> H[Reject incomplete plan]
When answer choices feel close, use severity plus setting as your tiebreaker. See Fig 6.
Algorithm / Approach
Rapid Review
- Stable common complaint → primary care management beats reflex referral.
- Respiratory distress → disposition question before diagnosis question.
- Normal growth with feeding concern → counsel and monitor, not automatic GI referral.
- Teen confidentiality → routine unless safety/legal exception appears.
- Suicidal plan → immediate safety escalation overrides routine privacy.
- Suspected abuse → report suspicion; do not wait for proof.
- Parent requests “strongest” treatment → current severity determines action, not family pressure.
- Advanced diagnostic option → wrong if it does not change today’s outpatient decision.
- Multiple comorbidities → do not assume beyond-scope if the child is stable.
- Primary care answer choice → usually includes counseling, monitoring, and follow-up.
- Referral choice → right when resources needed exceed office capability despite stability.
- Hospital-level answer → right only when instability or hospital-only need is clearly present.
Self-check quiz
1. A 9-year-old presents for follow-up of allergic rhinitis and mild eczema. He is afebrile, playful, and breathing comfortably. His parent asks whether the NP should “send him to the hospital to finally figure everything out.” Which action is most appropriate?
- Provide routine outpatient follow-up, symptom review, and caregiver teaching.
- Arrange inpatient evaluation because he has more than one chronic condition.
- Request emergency transfer because chronic conditions can worsen unexpectedly.
- Delay all management until a specialist has evaluated both conditions.
2. A 16-year-old requests time alone during a routine visit to discuss sexual health. She denies abuse, coercion, suicidal thoughts, and feeling unsafe. Which action is most appropriate?
- Provide confidential counseling within legal and clinic guidelines.
- Refuse confidentiality because a caregiver brought her to the visit.
- Disclose all details to the caregiver immediately after the discussion.
- Refer all confidential adolescent issues out because they are outside primary care scope.
3. A 2-month-old with a history of late preterm birth presents for cough and decreased feeding. He has nasal flaring, retractions, respiratory rate 66/min, and oxygen saturation 91% on room air. His parent also mentions a mild diaper rash. Which action is most appropriate?
- Discuss diaper skin care and recheck breathing after feeding.
- Initiate urgent emergency evaluation/EMS based on respiratory distress.
- Schedule follow-up tomorrow because infants often look worse before improving.
- Provide routine outpatient cough guidance and return precautions.
4. A 13-year-old with obesity and ADHD presents for routine follow-up. One blood pressure reading is mildly elevated; she feels well and has no headache, chest pain, or neurologic symptoms. Her parent asks whether all counseling should wait until a cardiology visit. Which action is most appropriate?
- Repeat the blood pressure properly, provide counseling, and continue primary care follow-up.
- Arrange emergency transfer for possible hypertensive emergency.
- Defer all counseling until cardiology has evaluated her.
- Ignore the blood pressure because the child is asymptomatic.
5. A 5-year-old with constipation and autism spectrum disorder presents for abdominal discomfort. He is hydrated, afebrile, playful, and has a soft abdomen without guarding. A grandparent requests hospital admission for bowel cleanout because “he always gets worse.” Which action is most appropriate?
- Develop an outpatient bowel plan with education and follow-up.
- Arrange direct admission because constipation can become severe.
- Order advanced imaging before attempting primary care management.
- Do nothing today because the abdomen is soft.
6. A 15-year-old presents for sports clearance. During confidential discussion, he reports intermittent sadness for months and then states he has current suicidal thoughts with access to pills at home. He asks the clinician not to tell his father, who is in the waiting room. Which action is most appropriate?
- Maintain confidentiality and schedule urgent outpatient therapy within 48 hours.
- Conduct immediate safety intervention and arrange emergency mental health evaluation.
- Finish the sports physical first to reduce his anxiety before addressing the disclosure.
- Encourage him to tell his father at home and call back if thoughts worsen.
7. A 14-year-old presents for acne follow-up and privately reports that her stepfather “gets rough” with her younger sibling. She asks the NP not to document it until she can “figure things out.” She otherwise feels safe today and has normal vital signs. Which action is most appropriate?
- Delay action until the adolescent provides more detail at a later visit.
- Document objective information and follow mandated reporting procedures for suspected abuse.
- Call the stepfather directly to hear his explanation before deciding.
- Honor confidentiality fully because the disclosure involved a sibling, not the patient.
8. An 11-year-old with asthma, obesity, and anxiety presents with 3 days of cough. He is afebrile, oxygen saturation is 99% on room air, there are no retractions, and lungs have faint end-expiratory wheeze only. His mother requests chest CT and direct hospital admission because he had pneumonia at age 4. Which action is most appropriate?
- Arrange direct admission because the history of pneumonia raises the risk of rapid decline.
- Order advanced imaging now because multiple comorbidities make outpatient assessment unreliable.
- Use focused outpatient assessment and management with clear return precautions.
- Refer immediately to pulmonology before changing any outpatient plan.
Answer key
1.1.1.8 1. Answer: A
A. Tempting because it seems almost too basic; correct because the child is stable and the conditions are routine outpatient chronic problems. The discriminating clue is the well-appearing child with no red flags, which fits longitudinal primary care management. Source support: outpatient chronic symptom follow-up and family education align with pediatric primary care standards and nursing process prioritization of safe, least intensive appropriate care.
B. Tempting because multiple chronic diagnoses can feel complex; incorrect because complexity alone does not equal inpatient need. The discriminating clue is stability without acute deterioration, making hospital evaluation disproportionate.
C. Tempting because chronic disease can worsen; incorrect because emergency transfer is reserved for current instability or time-sensitive danger. The discriminating clue is normal appearance and comfortable breathing.
D. Tempting if the learner is overly cautious about scope; incorrect because routine management of allergic rhinitis and eczema remains squarely within pediatric primary care. The discriminating clue is that both conditions are common outpatient problems.
1.1.1.9 2. Answer: A
A. Tempting because confidentiality questions can feel legally risky; correct because routine adolescent confidential counseling is part of primary care when no danger or mandatory disclosure trigger is present. The discriminating clue is explicit denial of abuse, coercion, suicidality, and unsafe home environment.
B. Tempting because the caregiver is physically present; incorrect because adolescent care commonly includes private discussion. The discriminating clue is absence of a safety exception.
C. Tempting because family involvement may be beneficial; incorrect because automatic disclosure would violate the expected confidentiality framework when no risk threshold is crossed. The discriminating clue is no stated legal or safety reason to disclose.
D. Tempting if confidentiality feels outside scope; incorrect because it is a core outpatient pediatric role. The discriminating clue is that the issue is common primary care counseling, not specialty-only management.
1.1.1.10 3. Answer: B
A. Tempting because diaper rash is a treatable outpatient issue and feeding matters in infants; incorrect because ABCs outrank minor skin care. The discriminating clue is nasal flaring, retractions, and low oxygen saturation.
B. Tempting because it is the highest-acuity option; correct because the infant shows objective respiratory distress requiring emergency-level evaluation. The discriminating clue is hypoxemia with increased work of breathing in a young infant.
C. Tempting because close follow-up is common in primary care; incorrect because waiting is unsafe when current distress is already present. The discriminating clue is that the child is unstable now, not possibly worse later.
D. Tempting because cough often receives supportive outpatient care; incorrect because routine guidance alone is inadequate in the setting of distress and low oxygen saturation. The discriminating clue is abnormal respiratory status, not the symptom label of cough.
1.1.1.11 4. Answer: A
A. Tempting because it requires doing several ordinary tasks rather than a dramatic action; correct because a stable adolescent with one mildly elevated reading needs proper reassessment, counseling, and follow-up in primary care. The discriminating clue is mild elevation without symptoms of hypertensive emergency.
B. Tempting because blood pressure abnormalities can be serious; incorrect because emergency transfer is for severe symptoms or instability. The discriminating clue is the absence of headache, chest pain, neurologic symptoms, or severe acute illness.
C. Tempting because specialty input may eventually be helpful; incorrect because it delays appropriate primary care counseling and reassessment. The discriminating clue is that the NP can act safely now within scope.
D. Tempting because a single mildly elevated reading may normalize; incorrect because ignoring it misses an appropriate primary care follow-up responsibility. The discriminating clue is that reassessment is still required even in asymptomatic patients.
1.1.1.12 5. Answer: A
A. Tempting because it seems conservative; correct because the child is stable, hydrated, and has no acute abdominal red flags. The discriminating clue is the soft, non-guarded abdomen with playful appearance, supporting outpatient management.
B. Tempting because constipation can become severe and the family is worried; incorrect because there is no current instability or failure of reasonable outpatient scope in the stem. The discriminating clue is the reassuring exam.
C. Tempting because advanced imaging sounds thorough; incorrect because specialty-level testing is not the first step for stable functional constipation without alarm findings. The discriminating clue is lack of peritoneal or obstructive signs.
D. Tempting because the child appears well; incorrect because symptoms still warrant standard outpatient management and counseling. The discriminating clue is that stable does not mean no action is needed.
1.1.1.13 6. Answer: B
A. Tempting because outpatient therapy is appropriate for many adolescents with depression; incorrect here because active suicidal thoughts with access to pills create an immediate safety risk. The discriminating clue is current suicidal ideation plus means.
B. Tempting because it is the most urgent option; correct because safety overrides confidentiality and routine visit goals. The discriminating clue is imminent self-harm risk, which requires emergency mental health evaluation.
C. Tempting because maintaining rapport can matter; incorrect because finishing the sports physical delays a life-safety intervention. The discriminating clue is that the urgent issue emerged during the visit and now outranks the original purpose.
D. Tempting because involving family is important and may reduce harm; incorrect because delaying until home without immediate safety response is unsafe. The discriminating clue is active current risk, not passive history alone.
1.1.1.14 7. Answer: B
A. Tempting because more detail can feel necessary before a serious report; incorrect because mandated reporting is triggered by suspicion, not certainty. The discriminating clue is disclosure suggesting possible abuse of a child in the home.
B. Tempting because it may feel uncomfortable or adversarial; correct because the clinician must document objective information and follow reporting procedures when abuse is suspected. The discriminating clue is that the obligation does not depend on proving the allegation personally.
C. Tempting because gathering both sides may seem fair; incorrect because confronting the alleged perpetrator is not the clinician’s investigative role and may increase risk. The discriminating clue is that safe reporting pathways, not independent investigation, are within scope.
D. Tempting because the teen requested privacy and the sibling is not the patient; incorrect because mandated reporting applies to suspected child maltreatment, not only direct abuse of the patient. The discriminating clue is safety duty to the child at risk.
1.1.1.15 8. Answer: C
A. Tempting because asthma history, obesity, and prior pneumonia can make the case feel high risk; incorrect because the child is currently stable without respiratory distress or hypoxemia. The discriminating clue is normal oxygen saturation and lack of retractions.
B. Tempting because advanced imaging seems thorough in a child with comorbidities; incorrect because it exceeds the needed intensity for a stable outpatient cough/wheeze visit. The discriminating clue is the mild current exam, not the remote past pneumonia.
C. Tempting because it may feel less decisive than admission or imaging; correct because focused outpatient management with return precautions matches both severity and setting. The discriminating clue is stable status with only faint wheeze.
D. Tempting because pulmonology may be useful eventually; incorrect because immediate specialty referral before outpatient management is not the best next step for this stable presentation. The discriminating clue is that the problem remains within routine primary care scope today.
Keep going with the full CPNP-PC Prep Course (CPNP-PC)
You just studied the way members do, in the same lesson interface. Full access unlocks every lesson, the question bank and flashcards for a full year.
One payment · 1 year of access · No auto-renewal