1.1.1 - USP And Regulatory Sources
Why it matters BCSCP questions often test which source governs before they test…
- 1 Why it matters BCSCP questions often test which source governs before they test… 1:31
- 2 Key Terms & Must-Know Facts Key terms USP: United States Pharmacopeia; publishe… 5:12
- 3 Accreditation standards matter operationally, but on exam questions the primary… 1:36
- 4 Core content 1.1.1.1 Foundational source hierarchy for sterile compounding deci… 3:32
- 5 Body 3:03
- 6 SAY “I need to verify the governing source before release or continued compound… 4:20
- 7 Verify safest compliant action: hold use of the shortcut, compare the local gui… 4:18
- 8 If you missed this: Review 1.1.1.1 Foundational source hierarchy for sterile co… 4:05
- 9 Body 3:45
- 10 Know both where a requirement originates and how it is documented locally for e… 4:21
- 11 Verify safest compliant action: stop preparation until the product-specific ins… 3:56
- 12 True or False: Accreditation findings usually replace drug-specific labeling wh… 3:24
- 13 Body 3:31
- 14 SAY “This looks like a source-selection issue, so I will identify the governing… 4:33
- 15 The SINGLE CLUE that eliminates it: the product in the stem is nonhazardous, so… 4:01
- 16 The tested conflict is not “Can you quote a rule?” but “What is the safest comp… 2:50
- 17 Body 3:40
- 18 Worked example A pharmacist reviewing a batch worksheet for cefepime 2 g in 100… 3:38
- 19 Checkpoint Question: A sterile compounding pharmacist finds that an internal wo… 3:46
- 20 The best routine is: identify the task → identify the governing source category… 2:58
- 21 5 Document outcome Create traceability for any deviation, clarification, or rel… 4:03
- 22 Eliminate distractors: patient anxiety is irrelevant; technician experience doe… 4:06
- 23 If you missed this: Review 1.1.1.5 Integration: building a practical pharmacist… 1:26
- 24 Exam Traps & Differentiators Most common wrong answer and why: choosing the mos… 4:21
- 25 Eliminating clue: accreditation recollection does not replace the governing com… 3:14
- 26 Tables Source Best use in exam stems Common trap USP <797> Nonhazardous sterile… 2:36
- 27 escalation chain Assuming it is always current and valid without checking autho… 3:20
- 28 Choose USP for process; choose labeling/drug info for product specifics USP vs… 3:27
- 29 Algorithm / Approach Concept flow: Five-step approach to source-based sterile c… 2:15
- 30 Rapid Review USP <797> → first stop for nonhazardous sterile process questions,… 3:46
- 31 Self-check quiz 1. 6:11
- 32 Release the bag because the label is complete and the drug is urgently needed H… 5:25
- 33 A pharmacist is asked whether a technician can continue compounding a hazardous… 5:00
- 34 Answer key 1. 4:14
- 35 B: Tempting because it directly addresses product-specific preparation; correct… 4:10
- 36 C: Tempting because product inserts can be authoritative; incorrect because man… 3:38
- 37 D: Tempting because nurses may know the product’s routine use; incorrect becaus… 3:45
- 38 If you missed this: Review 1.1.1.2 What each major source contributes — focus o… 4:17
- 39 Correct answer: C — Stop the affected workflow, verify the governing hazardous… 3:15
- 40 Correct answer: B — Manufacturer labeling or authoritative drug information, th… 3:18
Why it matters
- BCSCP questions often test which source governs before they test the technical detail itself.
- The safest compliant answer usually depends on recognizing whether the issue is compendial, regulatory, accreditation, or local policy.
- Wrong answers are commonly attractive because they cite a real source that is relevant, but not the best governing source for the specific scenario.
- When source authority is unclear, the pharmacist’s best move is typically to stop unsafe processing, verify the applicable source, and escalate through policy.
Key Terms & Must-Know Facts
1.1.1.1 Key terms
- USP: United States Pharmacopeia; publishes compendial standards.
- Compendial standard: Official standard that may become enforceable through law, regulation, or adoption.
- USP <797>: Sterile compounding standard for compounded sterile preparations.
- USP <800>: Hazardous drug handling standard.
- FDA: Federal agency overseeing drugs, manufacturing, labeling, and certain compounded product frameworks.
- State board of pharmacy: Jurisdictional regulator for pharmacy practice and facility operations.
- The Joint Commission / accreditation body: Accrediting organization; influential but not itself a substitute for compendial requirements.
- Institutional policy: Local procedures that operationalize standards and regulations.
- Enforceable: A requirement that can be required by law, rule, regulation, or adopted standard.
- Guidance: Influential interpretation or recommendation that may not independently function as the primary governing rule.
- SOP: Standard operating procedure; local document specifying how a site implements requirements.
- Insanitary condition: Condition creating contamination risk or rendering product quality questionable.
- Escalation pathway: Required chain for reporting, halting, investigating, and resolving risk.
1.1.1.2 Must-know facts
- USP chapters are central sources for sterile compounding questions, especially <797> and <800>.
- FDA labeling can guide product-specific handling and compatibility questions, but it does not replace sterile compounding standards.
- State law and board rules may be more specific or more restrictive; follow current applicable requirements.
- Institutional policy can be stricter than baseline standards and usually governs internal workflow if it does not conflict with higher authority.
- Accreditation standards matter operationally, but on exam questions the primary issue is often the most directly applicable sterile compounding standard.
- If facts are incomplete, do not guess; hold unsafe processing and verify the governing source.
- The exam tests pharmacist scope: interpret, verify, hold, clarify, document, and escalate.
- Do not answer from the perspective of an engineer, regulator issuing citations, or prescriber establishing therapy.
Core content
1.1.1.3 Foundational source hierarchy for sterile compounding decisions
A Explanation
The first decision conflict in this topic is simple but heavily tested: Which source should the pharmacist use first when a sterile compounding question asks for the safest compliant response? The resolution rule is: choose the source most directly governing the activity in the stem, then apply any more restrictive law or institutional policy that also validly applies. For sterile compounding operations, that usually means starting with USP sterile compounding standards rather than a general hospital policy memo or a broad accreditation manual. WHY THIS IS TESTED: exam writers know candidates can recognize terms like FDA, Joint Commission, and board of pharmacy, but the score turns on whether you can identify the best governing source for the precise task.
Use a layered approach. If the stem is about sterile preparation design, environmental controls, aseptic processing, personnel practices, release conditions, or documentation tied to sterile preparation quality, start with USP sterile compounding standards. If the stem turns on hazardous drug handling, containment, PPE, or hazardous workflow, bring USP hazardous drug standards to the front. If the stem focuses on a product-specific issue like reconstitution instruction, storage after vial puncture, light protection, concentration limits, or container recommendations, manufacturer labeling and authoritative drug information become highly relevant—but still within the compounding framework. If the stem asks about licensure, legal operation, or jurisdictional pharmacy requirements, state law and board rules may control.
The most common mistake is choosing the most famous source instead of the most applicable source. For example, FDA is critical in drug oversight, but many day-to-day sterile compounding exam questions are really asking about USP implementation. Likewise, a local SOP matters greatly in practice, but it must rest on a valid standard or institutional adoption pathway. See Fig 1.
Exam takeaway: Start with the most directly applicable compendial or legal source, then apply stricter local policy if it validly fits.
flowchart TD
A[Identify the task in the stem] --> B{What is being governed?}
B -->|Sterile compounding process| C[Start with USP 797]
B -->|Hazardous drug handling| D[Start with USP 800]
B -->|Product-specific use/storage info| E[Check FDA labeling or authoritative drug info]
B -->|Licensure or jurisdiction rule| F[Check state law or board rule]
C --> G[Apply local policy if stricter and consistent]
D --> G
E --> G
F --> G
G --> H[If unclear or unsafe: hold, verify, escalate] Exam takeaway: The fastest correct answer starts with classifying the problem before looking for details.
B Worked example
A 450-bed hospital pharmacy receives an order to compound vancomycin 1.5 g in 250 mL D5W IV every 12 hours for a 67-year-old patient with heart failure, obesity, and chronic kidney disease. During verification, a new pharmacist notices that the unit’s laminated “cleanroom quick guide” permits a workflow shortcut for staging supplies on a cart near the PEC. The cleanroom technician also mentions that “the accreditor was okay with our setup last year.” An irrelevant distraction in the chart shows mildly elevated AST/ALT. The question asks for the most appropriate next step from the sterile compounding pharmacist perspective.
Identify task: This is not a dosing question; it is a sterile compounding workflow and source-authority question. Extract key facts: local quick guide suggests a shortcut, accreditor comment is secondhand, and the issue affects PEC workflow. Apply rule: workflow in and around sterile compounding operations is governed primarily by applicable USP sterile compounding standards and valid institutional policy implementing them—not by hearsay about accreditation impressions. Eliminate distractors: do not accept the shortcut because it appears efficient; do not rely on an accreditation anecdote; do not change drug therapy because the patient’s AST/ALT is irrelevant here. Verify safest compliant action: hold use of the shortcut, compare the local guide with current governing standards and policy, and escalate for correction if inconsistent.
C Exam trap
D Checkpoint
Question: A pharmacist is asked to verify whether a nonhazardous sterile compounding workflow change near the PEC is acceptable for cefazolin 2 g in 100 mL NS IV every 8 hours. Which source should be checked first as the most directly applicable primary source?
- USP <797>
- Manufacturer package insert for cefazolin
- Accreditation survey tracer notes
- Unit nursing preference document
Answer: A
- A is tempting and right because the question is about nonhazardous sterile compounding workflow near the PEC, which points directly to the sterile compounding standard.
- B is tempting but wrong because package inserts help with product-specific preparation and storage, not primary governance of cleanroom workflow design.
- C is tempting but wrong because accreditation findings matter operationally, yet they are not the primary sterile compounding standard for this question.
- D is tempting but wrong because local preference documents are low-authority unless supported by the governing standard and institutional policy chain.
1.1.1.4 What each major source contributes: USP, FDA, state law, accreditation, and policy
A Explanation
The second major conflict is not “Which source exists?” but “What does each source actually do?” Candidates lose points by overextending a source beyond its proper role. USP supplies practice standards for compounding. FDA supplies federal oversight, approved labeling, manufacturing distinctions, and product-specific information. State boards and state law control practice authority, licensure, and jurisdiction-specific implementation. Accreditation organizations evaluate compliance structures and system performance. Institutional policy translates all of that into daily steps, logs, forms, restrictions, and escalation rules.
A fast exam strategy is to sort sources by function. USP answers “How should sterile compounding be performed safely and compliantly?” FDA labeling answers “What does the approved product information say about formulation, storage, handling, dilution, and stability constraints?” State law answers “What is legally required in this jurisdiction for the pharmacy’s operations?” Accreditation answers “What organizational systems and documentation structures are being assessed?” Institutional policy answers “How does this organization implement the requirements in day-to-day workflow?” This framework is especially useful when two answers are both true statements but only one is the best source for the action in the stem. See Fig 2.
Forward reference: in the upcoming lesson on Standards Conflict Resolution, you will build from this section to decide what to do when two sources appear to disagree. For now, learn the distinct function of each source before trying to resolve conflicts among them.
Exam takeaway: Source questions are easiest when you classify each authority by what kind of answer it is designed to provide.
flowchart LR
A[USP] --> A1[Compounding process standards]
B[FDA labeling and oversight] --> B1[Product-specific instructions]
C[State law and board rules] --> C1[Jurisdiction requirements]
D[Accreditation] --> D1[System evaluation expectations]
E[Institutional policy] --> E1[Local implementation steps]
A1 --> F[Daily sterile compounding decisions]
B1 --> F
C1 --> F
D1 --> F
E1 --> F
Exam takeaway: Visualize USP standards at the operational core with state law and institutional policy layered around day-to-day implementation.
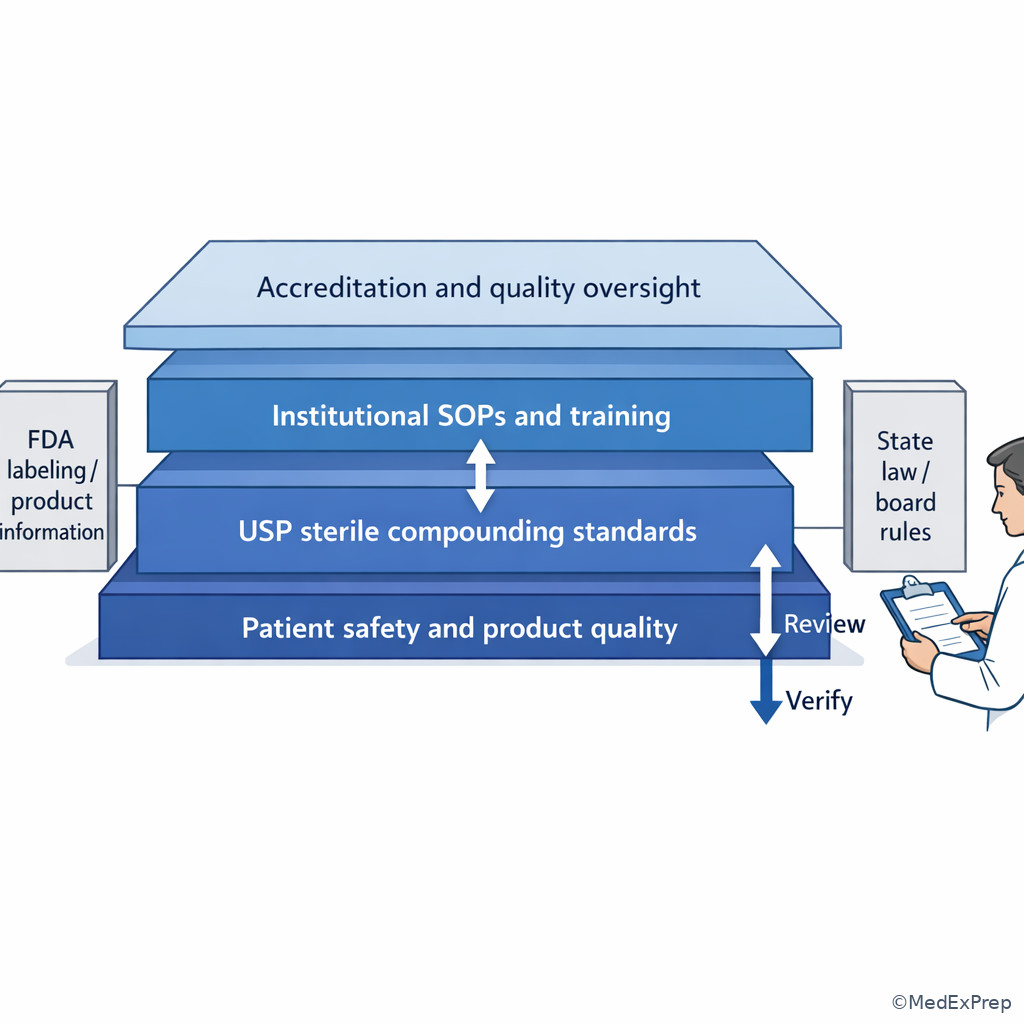
Exam takeaway: Pick the source by function, not by fame.
B Worked example
A pharmacist verifies amphotericin B liposomal 50 mg IV to be prepared in D5W, while a covering technician references a homegrown dilution chart that lists NS as an option. The patient is 58 years old with acute leukemia, diabetes, and a tunneled central catheter. A distracting lab shows mild hypomagnesemia. Another pharmacist says, “Our accreditor mostly focuses on documentation, so it’s probably fine.” The question asks which source is most appropriate to clarify immediately.
Identify task: This is a product-specific compatibility and preparation instruction question, not a general cleanroom workflow question. Extract key facts: amphotericin B liposomal has specific dilution constraints, and the chart may be wrong. Apply rule: use authoritative product-specific information such as FDA-approved labeling or authoritative drug information, while keeping compounding standards in mind for the sterile process. Eliminate distractors: accreditation comments do not answer the diluent question; the electrolyte abnormality is clinically relevant but does not govern compounding feasibility. Verify safest compliant action: stop preparation until the product-specific instruction is confirmed through the proper source and correct the local chart if inaccurate.
C Exam trap
D Checkpoint
Question: Which source is usually most helpful first when a pharmacist must confirm whether a specific lyophilized injectable product may be reconstituted with sterile water versus normal saline before compounding?
- FDA-approved product labeling or authoritative drug information
- Accreditation tracer methodology documents
- Environmental monitoring trend reports
- General orientation slides for new technicians
Answer: A
- A is tempting and right because the question is product-specific and turns on reconstitution instructions.
- B is tempting but wrong because accreditation documents assess systems, not the exact drug’s approved reconstitution details.
- C is tempting but wrong because trend reports inform quality management, not product formulation instructions.
- D is tempting but wrong because training slides may summarize practice but are not the authoritative first source for drug-specific preparation details.
- The primary sterile compounding process standard for most nonhazardous CSP workflow questions is USP <797>.
- True or False: Accreditation findings usually replace drug-specific labeling when a diluent question arises. False.
- Name the 3 most common source categories in exam stems: compendial standard, product-specific information, jurisdiction/policy.
1.1.1.5 Applied source recognition in common sterile compounding scenarios
A Explanation
Once the source types are clear, the next exam move is pattern recognition: what kind of scenario points to what source? Foundational exam stems often hide this behind clinical noise, staffing distractions, or references to previous survey comments. The deciding rule is to classify the trigger in the stem. If the trigger is facility, garbing, PEC use, workflow, aseptic manipulations, environmental quality, labeling elements, or release process, think USP sterile compounding standard first. If the trigger is hazardous drug receipt, compounding, containment, PPE, decontamination, waste, or exposure response, think hazardous drug standard. If the trigger is specific vial handling, required diluent, light protection, filter use, concentration limit, or compatibility, think product-specific source plus compounding standard. If the trigger is who may perform an activity, registration, permit, or legal requirement, think law and board rules.
This is where test writers insert attractive distractors. A statement like “the vendor trainer said this is acceptable” sounds experienced but is not the governing source. Likewise, “the technician has done it that way for years” tests whether you recognize habit as a poor authority. See Fig 4 for a quick scenario-to-source map.
Exam takeaway: Match the trigger word in the stem to the source category before evaluating the options.
flowchart TD
A[Read the trigger in the stem] --> B{Trigger type?}
B -->|Garbing, PEC, airflow, release, aseptic workflow| C[USP 797 pathway]
B -->|Hazardous drug, PPE, containment, spill, waste| D[USP 800 pathway]
B -->|Diluent, filter, concentration, storage, vial instruction| E[Product-specific pathway]
B -->|License, permit, jurisdiction, practice authority| F[State law pathway]
C --> G[Then verify local SOP]
D --> G
E --> G
F --> G
G --> H[If conflict or uncertainty: hold and escalate] Exam takeaway: Trigger words in the stem often tell you which source to open before reading answer choices.
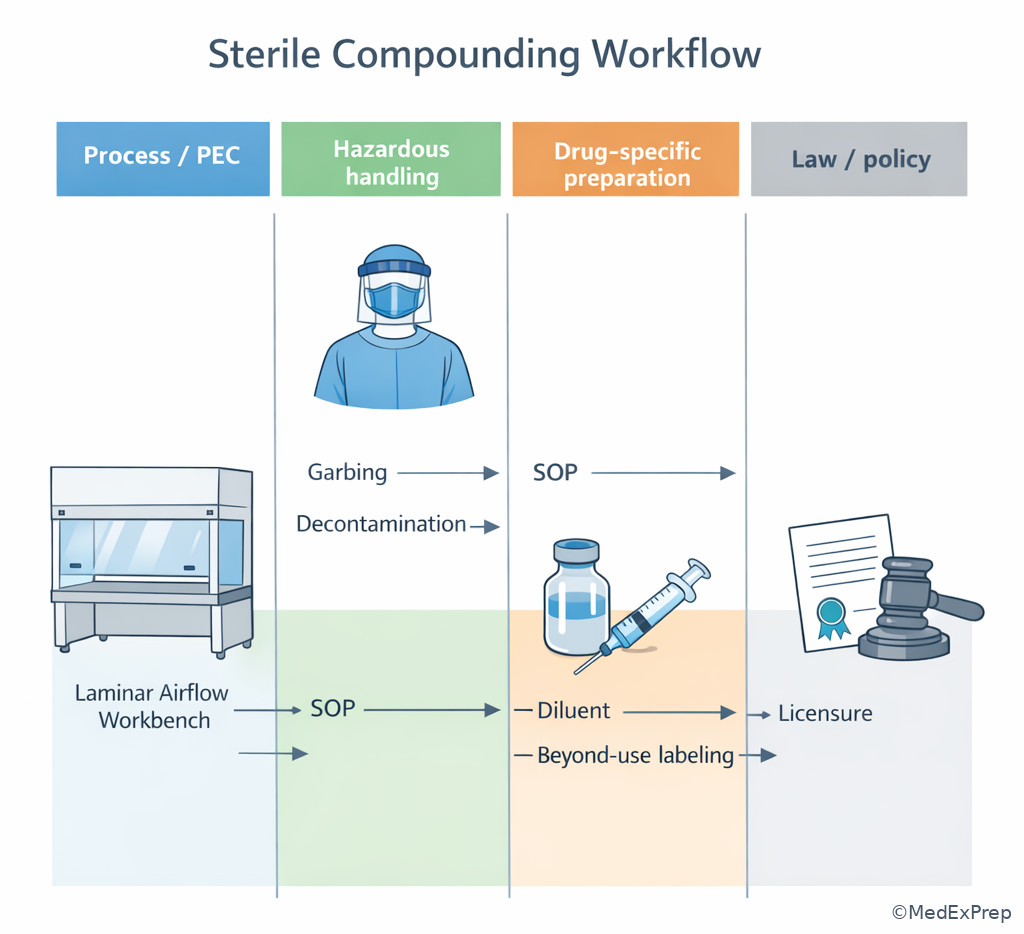
Exam takeaway: Classify the risk source before deciding whether to continue, hold, or escalate.
B Worked example
A batch of norepinephrine 4 mg in 250 mL D5W for ICU use is being prepared during a staffing shortage. A technician asks whether a face shield is required for a step involving a nonhazardous sterile preparation. Another staff member references the hazardous drug spill kit checklist because “it has all the PPE rules.” The patient linked to the first bag is a 72-year-old with septic shock, atrial fibrillation, and chronic anemia; a distracting chart note documents a penicillin allergy. The pharmacist must choose the most appropriate source category to answer the PPE question.
Identify task: PPE question in nonhazardous sterile compounding. Extract key facts: nonhazardous, sterile process, not spill response, not hazardous drug handling. Apply rule: use the source governing sterile compounding garbing and aseptic process expectations, not the hazardous drug checklist. Eliminate distractors: the spill kit checklist is attractive because it mentions PPE; the patient allergy is irrelevant; ICU urgency does not remove the need to use the right standard. Verify safest compliant action: answer the PPE question using the nonhazardous sterile compounding source and applicable local garbing policy.
C Exam trap
D Checkpoint
Question: A pharmacist must clarify whether a technician’s decontamination step after compounding cyclophosphamide 1 g IV is sufficient. Which source category is most directly applicable first?
- USP hazardous drug handling standard
- Manufacturer insert for cyclophosphamide alone
- Accreditation environment-of-care chapter
- Nursing infusion administration manual
Answer: A
- A is tempting and right because the issue is hazardous drug handling, decontamination, and exposure control.
- B is tempting but wrong because manufacturer information may help with reconstitution but does not primarily govern hazardous area decontamination workflow.
- C is tempting but wrong because accreditation language is broader and less direct than the hazardous compounding standard for this task.
- D is tempting but wrong because administration manuals do not govern hazardous compounding cleanup steps.
1.1.1.6 Handling ambiguity, apparent conflict, and missing information
A Explanation
The final foundational skill is what to do when the source answer is not immediately clean. This is the bridge to pharmacist judgment. Board-style questions often present outdated internal documents, partial facts, ambiguous references, or competing expectations. The tested conflict is not “Can you quote a rule?” but “What is the safest compliant response while authority is uncertain?” The single resolving rule is conservative: if uncertainty could affect sterility, product quality, containment, worker safety, or patient safety, do not continue on assumption alone. Hold the affected process or product as appropriate, verify facts against the governing source, document the issue, and escalate through the proper pathway.
Important nuance: “escalate” does not mean abandon judgment. The pharmacist is expected to recognize the risk, stop unsafe continuation, and involve the right operational owner—quality leader, designated supervisor, infection prevention, occupational safety, or prescriber when order clarification is needed. You are not expected to redesign HVAC systems or certify engineering controls; those are out of role. But you are absolutely expected to identify when uncertified, unclear, or conflicting conditions make continued compounding unsafe.
See Fig 5 for a practical conflict pathway. This same stop-verify-escalate approach will recur across future topics such as environmental monitoring excursions, documentation defects, and beyond-use dating uncertainty.
Exam takeaway: If unresolved uncertainty affects sterility, quality, or safety, stop the process, verify the source, document, and escalate.
flowchart TD
A[Potential conflict or missing fact] --> B{Could safety, sterility, or containment be affected?}
B -->|Yes| C[Hold product or stop processing]
B -->|No immediate risk| D[Verify source before proceeding]
C --> E[Check governing source and current policy]
D --> E
E --> F[Document discrepancy]
F --> G[Escalate to quality or responsible leader]
G --> H[Resume only when clarified and compliant] Exam takeaway: When documents conflict, the pharmacist protects the patient first by holding risky work and tracing authority.
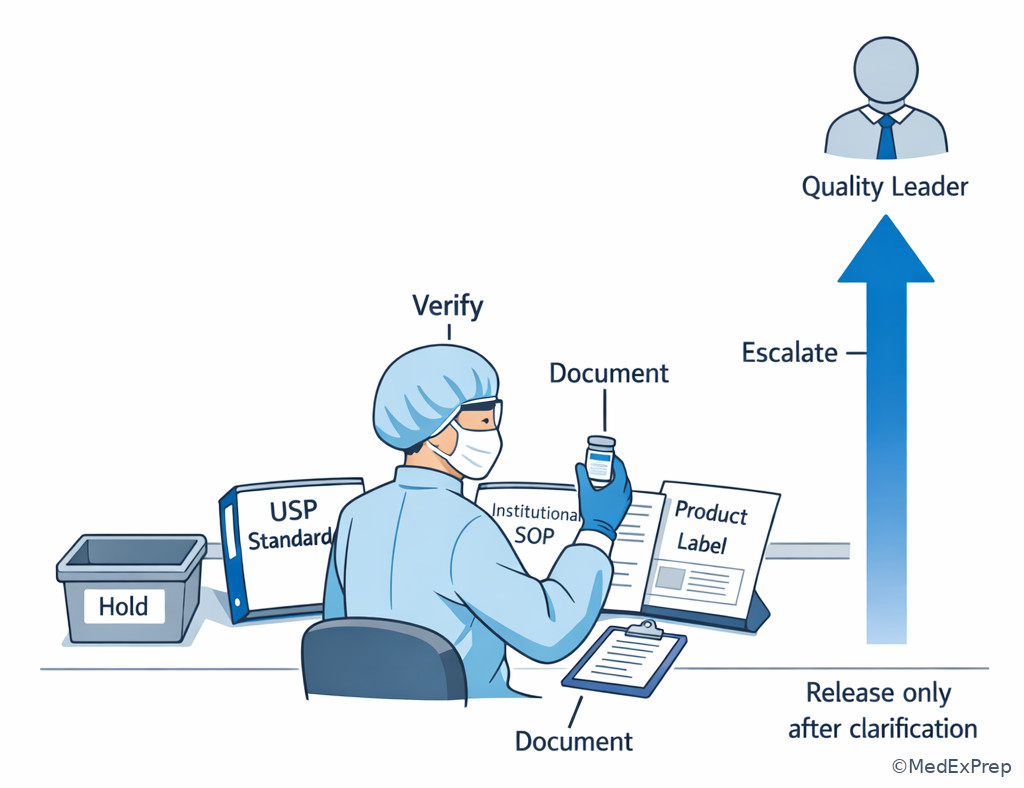
Exam takeaway: The correct board answer usually favors patient and product protection over convenience when facts are incomplete.
B Worked example
A pharmacist reviewing a batch worksheet for cefepime 2 g in 100 mL NS IV every 8 hours notices that the institutional SOP revision date is older than the current compendial reference kept in the department binder. The batch is intended for a 64-year-old patient with neutropenia, hypertension, and type 2 diabetes. A distracting note indicates the patient prefers evening infusions earlier in the night. A technician says the batch should go out now because “we passed inspection with this SOP.” The question asks for the safest compliant response.
Identify task: source discrepancy affecting sterile compounding procedure. Extract key facts: local SOP may be outdated relative to current governing reference; product release is pending. Apply rule: do not rely on an outdated local procedure when a current governing source may require different practice; verify and hold if the discrepancy could matter. Eliminate distractors: inspection history is not proof of current compliance; patient scheduling preference is irrelevant; there is no basis to improvise a middle-ground procedure without verification. Verify safest compliant action: quarantine or pause affected workflow as appropriate, compare current standards and SOP requirements, document the discrepancy, and escalate for quality review before release.
C Exam trap
D Checkpoint
Question: A sterile compounding pharmacist finds that an internal worksheet for a hazardous CSP conflicts with the current departmental hazardous drug policy, and the discrepancy could change cleaning steps after compounding. What is the best initial action?
- Continue using the worksheet because it was approved when created
- Choose the faster method to avoid delaying therapy
- Hold the affected workflow, verify the governing source and current policy, then escalate
- Ask the prescriber which cleaning method is preferred
Answer: C
- A is tempting but wrong because historical approval does not override a current conflict that may affect safety.
- B is tempting but wrong because speed is never the deciding factor when source ambiguity could affect hazardous cleaning compliance.
- C is tempting and right because it protects safety, establishes authority, and follows pharmacist-level escalation responsibilities.
- D is tempting but wrong because the prescriber does not govern sterile compounding cleaning procedures.
- True or False: Prior successful use of a workflow proves current compliance. False.
- The safest first action when a source conflict could affect sterility is hold or stop the affected process.
- Name the 3 immediate moves after a meaningful source conflict is identified: verify, document, escalate.
1.1.1.7 Integration: building a practical pharmacist source-check routine
A Explanation
For exam performance, you need a repeatable routine that works under pressure. The best routine is: identify the task → identify the governing source category → check for stricter overlays → decide whether risk requires hold → document and escalate when needed. This routine keeps you inside pharmacist scope and prevents common reasoning errors. It also protects against the exam’s favorite distractor pattern: a locally convenient answer that sounds practical but bypasses source verification.
This section is integrative because it combines source recognition with action discipline. A pharmacist does not need to memorize every line from every authority to answer many exam questions. Instead, the pharmacist must know which source to consult first, when a product can proceed, and when uncertainty itself requires interruption. See Fig 6. In the next two topics, this framework will extend to role boundaries and formal conflict resolution.
Exam takeaway: A consistent source-check routine improves both compliance and exam accuracy when answer choices are all plausible.
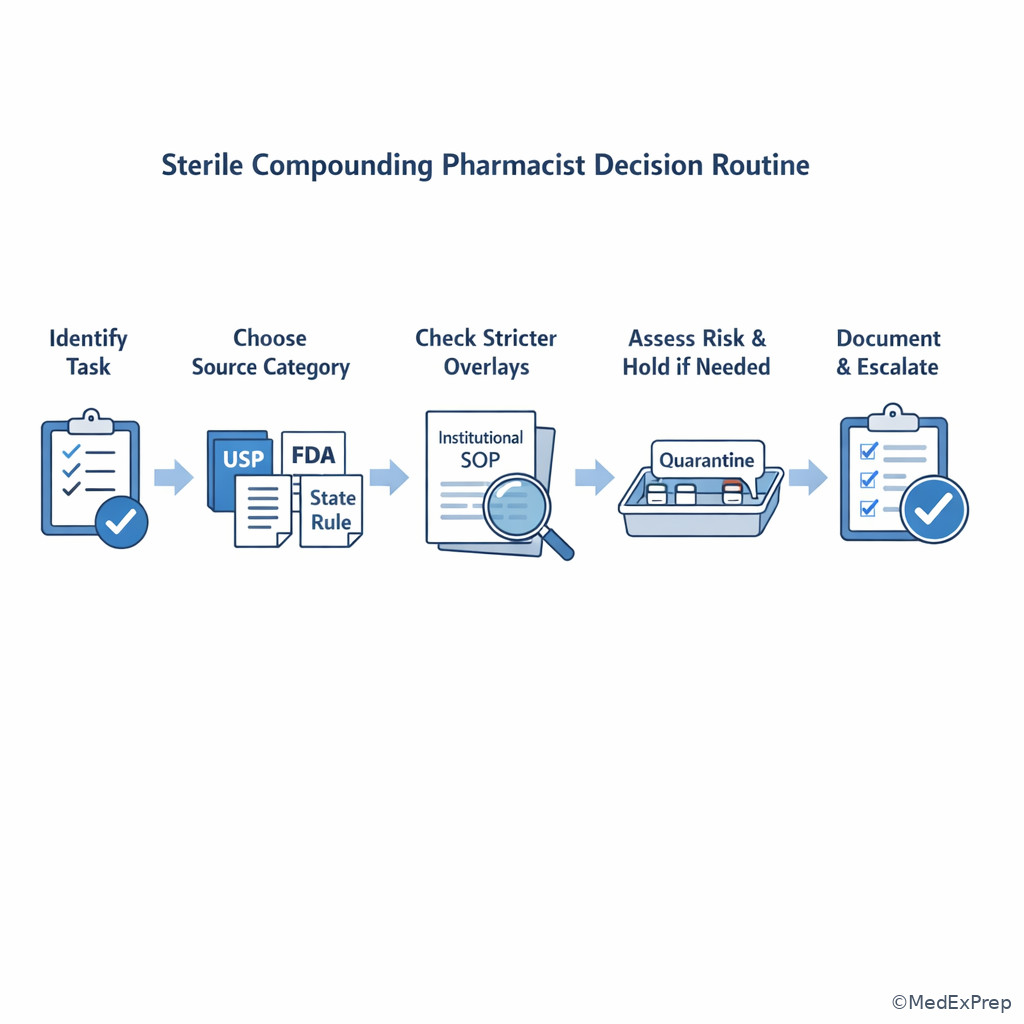
Exam takeaway: Organizing source checkpoints visually helps separate process standards from product instructions and local implementation documents.
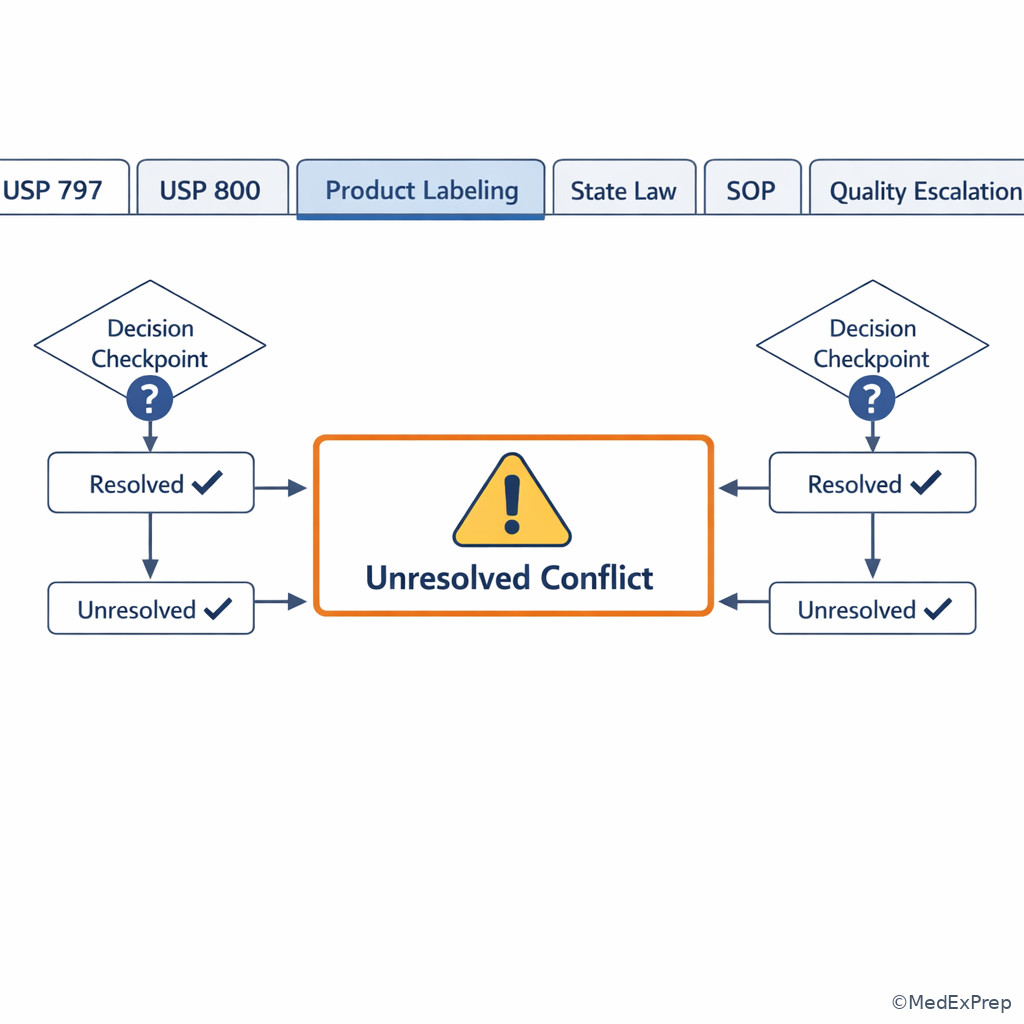
Exam takeaway: Use the same disciplined sequence on every stem to avoid being distracted by operational noise.
B Worked example
A pharmacist covering evening operations is asked to release an epidural infusion bag prepared earlier: fentanyl 2 mcg/mL with bupivacaine 0.125% in 250 mL NS, route epidural, continuous infusion. The patient is 41 years old with obesity and sleep apnea; a distracting note says the patient is anxious about needles. The bag label appears complete, but the preparation record references an institutional worksheet that lacks a recent revision date. A senior technician reports that the formula and label format are “what we’ve always used.” The question asks for the best pharmacist response before release.
Identify task: product release decision with documentation/source validity concern. Extract key facts: unclear document currency; release depends on confidence that current source-based requirements were met. Apply rule: release should not rely only on tradition; verify the current governing procedure and documentation basis. Eliminate distractors: patient anxiety is irrelevant; technician experience does not establish current compliance; a superficially complete label does not resolve whether the workflow was governed by a current approved process. Verify safest compliant action: hold release pending verification of the current source-backed worksheet/SOP, document the discrepancy, and escalate if needed.
C Exam trap
D Checkpoint
Question: Which sequence best reflects a pharmacist’s repeatable source-check routine on BCSCP-style questions?
- Read the answer choices first, choose the strictest-sounding one, then document if needed
- Identify the task, choose the governing source, check stricter overlays, assess risk, then hold/escalate if unresolved
- Ask the technician how the task is usually done, then compare with accreditation comments
- Use product labeling for all compounding decisions, then consult policy only if a survey is pending
Answer: B
- A is tempting but wrong because “strictest-sounding” is not a substitute for identifying the governing source.
- B is tempting and right because it reflects the disciplined order needed for safe source-based decision making.
- C is tempting but wrong because habit and survey recollection are not primary decision authorities.
- D is tempting but wrong because product labeling does not govern all sterile compounding process questions.
Exam Traps & Differentiators
Most common wrong answer and why: choosing the most familiar authority instead of the most directly applicable one. FDA, accreditation, local policy, and senior staff habits all sound authoritative. The exam rewards choosing the source that actually governs the task in the stem.
| Looks similar | But isn't the best answer because | Think instead |
|---|---|---|
| FDA labeling | It gives drug-specific instructions, not the full sterile compounding process standard | Use it for product-specific preparation details |
| Accreditation language | It evaluates systems but is often less direct than USP for compounding procedure questions | Use USP for process questions first |
| Institutional SOP | It may be outdated or incomplete if not aligned with current authority | Confirm it is current and supported by higher authority |
| Vendor training | Operationally helpful but not itself the governing authority | Verify against official standards and local policy |
| Technician habit | Experience does not establish compliance | Follow source-based workflow, not custom |
- If the stem says garbing, PEC, first air, compounding area workflow, release checks think USP sterile compounding standard.
- If the stem says hazardous drug, containment, PPE, decontamination, spill, waste think hazardous drug handling standard.
- If the stem says reconstitute with, dilute in, protect from light, use filter, concentration limit think product-specific labeling or authoritative drug information.
- If the stem says license, permit, legal authority, jurisdiction requirement think state law and board rules.
- If the stem says policy conflict, outdated SOP, uncertain applicability think hold/verify/document/escalate.
- “The accreditor accepted it.” Tempting because it sounds validated. Eliminating clue: accreditation recollection does not replace the governing compendial source.
- “We always do it this way.” Tempting because habit suggests reliability. Eliminating clue: routine use does not prove current compliance.
- “The package insert says how to mix it, so that answers the whole question.” Tempting because product instructions are authoritative. Eliminating clue: the stem may really be about process governance rather than the drug’s reconstitution details.
- “The local SOP is enough.” Tempting because policy drives daily workflow. Eliminating clue: if the SOP appears outdated or conflicts with higher authority, it cannot be accepted without verification.
Tables
| Source | Best use in exam stems | Common trap |
|---|---|---|
| USP <797> | Nonhazardous sterile compounding process, environment, aseptic workflow, release-related practice standards | Ignoring it in favor of local habit or accreditation commentary |
| USP <800> | Hazardous drug handling, containment, PPE, decontamination, waste, exposure control | Applying it to every PPE question, even when the product is nonhazardous |
| FDA labeling / authoritative drug info | Diluent, reconstitution, concentration, storage, light protection, filter, product-specific instructions | Using it as the only source for process workflow questions |
| State law / board rules | Licensure, legal requirements, jurisdiction-specific rules, facility authority | Forgetting that legal overlays may be stricter than baseline standards |
| Institutional policy / SOP | Local implementation, forms, training, documentation steps, escalation chain | Assuming it is always current and valid without checking authority |
| Accreditation standards | System quality expectations and organizational oversight context | Treating accreditation language as the most direct source for technical compounding details |
| Question asks about | Choose first | Then consider |
|---|---|---|
| PEC workflow for cefazolin IV admixture | USP <797> | Current SOP and any stricter law/policy |
| Cyclophosphamide decontamination steps | USP <800> | Current hazardous compounding SOP |
| Whether a lyophilized vial must use SWFI or NS | FDA labeling / authoritative drug info | Compounding workflow controls and local worksheet accuracy |
| Whether the pharmacy may perform a regulated activity in a jurisdiction | State law / board rules | Institutional licensing and policy process |
| Internal release procedure when worksheet is outdated | Current governing source + institutional policy | Quality escalation and documentation |
| Differential source problem | Discriminator | Best response |
|---|---|---|
| Process standard vs product labeling | Is the stem about how compounding is performed or how this drug is prepared? | Choose USP for process; choose labeling/drug info for product specifics |
| USP vs local SOP | Is the SOP current and aligned with higher authority? | If uncertain, verify before relying on SOP |
| Hazardous standard vs nonhazardous garbing rule | Is the preparation hazardous? | Use hazardous standard only when the task involves hazardous handling |
| Accreditation note vs governing standard | Does the note directly answer the technical sterile compounding requirement? | Usually no; go back to the direct governing source |
| Old worksheet vs current reference | Could the discrepancy affect sterility, containment, or release? | Hold, verify, document, escalate |
| Authority type | Strength on exam | Typical wrong use |
|---|---|---|
| Compendial | Strong for sterile practice standards | Ignored when a local shortcut seems convenient |
| Regulatory/legal | Strong for jurisdiction and legal operation questions | Overapplied to technical product-specific details |
| Product-specific | Strong for reconstitution and storage details | Overapplied to all workflow questions |
| Institutional | Strong for implementation if current and valid | Assumed correct even when outdated |
| Informal/custom | Weak | Treated as if it were an official source |
Algorithm / Approach
Rapid Review
- USP <797> → first stop for nonhazardous sterile process questions, not drug-specific diluent questions.
- USP <800> → think hazardous handling, containment, PPE, decontamination, waste.
- FDA/product labeling → best for reconstitution, dilution, filter, storage, light-protection details.
- State law → legal authority and jurisdiction questions, not first-line for routine product-specific mixing instructions.
- Institutional SOP → implementer, not independent higher authority.
- Accreditation note → system-level clue, not usually the primary technical compounding source.
- Habit/tradition → never enough when the stem asks what governs.
- Outdated document → treat as a risk signal, not a convenience signal.
- Unclear authority → hold/verify/escalate beats guess-and-proceed.
- PPE question → first decide hazardous versus nonhazardous before selecting the source.
- Label complete but source uncertain → do not release until source validity is confirmed.
- Survey memory → weak compared with current governing standard text.
Self-check quiz
1. A pharmacist is reviewing workflow for ceftriaxone 1 g in 50 mL NS IV every 24 hours prepared as a nonhazardous CSP. A technician asks which source most directly governs the sterile compounding process near the PEC. Which is the most appropriate source?
- USP <797>
- USP <800>
- FDA package insert only
- Accreditation survey summary
2. A pharmacist must confirm whether a vial of meropenem 1 g should be reconstituted with a specific diluent before preparing an IV bag for a 70-year-old patient with CKD and COPD. Which source is the best first reference for that drug-specific question?
- Current institutional holiday staffing plan
- FDA-approved product labeling or authoritative drug information
- General garbing SOP
- Accreditation environment-of-care chapter
3. A pharmacist reviews an order for cyclophosphamide 750 mg IV once, to be compounded in the hazardous area. The technician asks which source should be checked first for decontamination steps after completion. The patient is 55 years old with breast cancer, diabetes, and hypertension; a distracting note mentions a prior contrast reaction. Which is the most appropriate next step?
- Use USP <800> as the primary source, then follow current local hazardous SOP
- Use USP <797> only because all sterile compounding starts there
- Use the manufacturer insert only because the drug is product-specific
- Ask the prescriber which cleaning sequence is preferred
4. A pharmacist is about to release norepinephrine 4 mg in 250 mL D5W IV continuous infusion for a 68-year-old patient with septic shock, atrial fibrillation, and CKD. The label is complete, but the worksheet used for compounding lacks a current revision date and may not match the latest source. A distracting lab shows low albumin. What is the safest compliant response?
- Release the bag because the label is complete and the drug is urgently needed
- Hold release, verify the current governing source and worksheet validity, then document and escalate if needed
- Discard immediately without verifying because any date gap proves contamination
- Ask nursing whether they have used this worksheet format before
5. A pharmacist must clarify whether liposomal amphotericin B 50 mg IV should be diluted in D5W or NS for a 62-year-old patient with AML, diabetes, and a central line infection history. A colleague points to a local chart; another mentions that “surveyors liked our documentation.” Which option is the best first source category for immediate clarification?
- Accreditation comments because they reflect external review
- Manufacturer labeling or authoritative drug information because the question is product-specific
- USP <800> because amphotericin is a high-risk IV medication
- Nursing administration handbook because it describes infusion handling
6. During evening shift, a pharmacist overseeing piperacillin/tazobactam 3.375 g in 100 mL NS IV every 6 hours learns that the unit-specific “cleanroom shortcut” allows staging supplies closer to the PEC than the current department compounding manual appears to allow. The patient is 73 years old with CKD, CHF, and delirium; a distracting note reports a remote latex sensitivity. Which action best reflects pharmacist-level source judgment?
- Continue using the shortcut because local workflow documents are always controlling
- Use the shortcut for urgent doses only, then review later
- Pause use of the shortcut, verify the governing sterile compounding source and current policy alignment, then escalate if inconsistent
- Call the accrediting body for immediate permission to proceed
7. A pharmacist is asked whether a technician can continue compounding a hazardous CSP after noticing that the posted cleaning sequence in the room conflicts with the newly issued hazardous drug SOP. The preparation is fluorouracil 4,000 mg in an ambulatory pump, and the patient is 49 years old with colon cancer, obesity, and poorly controlled nausea. A distracting issue is that the courier pickup is in 20 minutes. What is the best initial action?
- Continue using the posted sequence because posted signs are operationally approved
- Use the newer SOP without documenting the discrepancy so the dose is not delayed
- Stop the affected workflow, verify the governing hazardous source, document the conflict, and escalate per policy
- Ask the oncologist whether either cleaning sequence is acceptable
8. A pharmacist must decide which source to prioritize for a question about whether a lyophilized nonhazardous antibiotic requires a specific diluent and concentration limit before compounding. The local SOP is current, but it summarizes only workflow steps and does not list drug-specific instructions. The patient is 80 years old with ESRD and COPD; a distracting note mentions a family request for earlier discharge. Which option is the most appropriate first source?
- USP <797> only, because all sterile compounding details are contained there
- Manufacturer labeling or authoritative drug information, then apply institutional workflow controls
- Accreditation standards because they are external and broad
- State board rule first, because any preparation question is primarily jurisdictional
Answer key
1. Correct answer: A — USP <797>
- A: Tempting because it is the core sterile compounding standard for nonhazardous process questions; correct because the stem is about workflow near the PEC for a nonhazardous CSP. The discriminating clue is “nonhazardous CSP” and “process near the PEC”. Source: USP General Chapter <797>.
- B: Tempting because it is also a famous sterile compounding chapter; incorrect because USP <800> governs hazardous drug handling, not routine nonhazardous process workflow. The discriminating clue is absence of hazardous drug handling. Source: USP General Chapter <800>.
- C: Tempting because package inserts are authoritative for drug details; incorrect because the question is about compounding process governance, not ceftriaxone-specific reconstitution. The discriminating clue is workflow question rather than product instruction. Source: FDA labeling plus USP <797> framework.
- D: Tempting because surveys influence practice; incorrect because survey summaries are not the most direct technical source for PEC workflow. The discriminating clue is need for a direct governing practice standard. Source: USP <797> and accreditation framework distinctions.
2. Correct answer: B — FDA-approved product labeling or authoritative drug information
- A: Tempting because operational plans are part of local workflow; incorrect because staffing plans do not answer drug-specific reconstitution questions. The discriminating clue is specific diluent question. Source: FDA labeling and drug information references.
- B: Tempting because it directly addresses product-specific preparation; correct because reconstitution diluent is a product instruction. The discriminating clue is “should be reconstituted with a specific diluent”. Source: FDA label, AHFS, Lexicomp, Clinical Pharmacology.
- C: Tempting because garbing SOPs matter in sterile compounding; incorrect because they do not determine meropenem’s reconstitution diluent. The discriminating clue is drug-specific rather than process-garbing issue. Source: institutional SOP role distinction.
- D: Tempting because accreditation chapters are broad and official; incorrect because they are not the best first source for a product-specific reconstitution instruction. The discriminating clue is preparation detail tied to a specific vial. Source: accreditation versus product source distinctions.
3. Correct answer: A — Use USP <800> as the primary source, then follow current local hazardous SOP
- A: Tempting because it names both the governing hazardous standard and local implementation; correct because decontamination after hazardous compounding is a hazardous drug handling question. The discriminating clue is cyclophosphamide in the hazardous area with decontamination steps. Source: USP <800> and local SOP implementation.
- B: Tempting because all CSPs involve sterile compounding; incorrect because the specific issue is hazardous decontamination, making USP <800> more directly applicable. The discriminating clue is hazardous handling rather than general sterile workflow. Source: USP <800>.
- C: Tempting because product inserts can be authoritative; incorrect because manufacturer information does not primarily govern area decontamination steps. The discriminating clue is post-compounding cleaning workflow. Source: USP <800>.
- D: Tempting because prescribers are involved in patient therapy; incorrect because prescribers do not set hazardous cleaning protocol. The discriminating clue is operational compounding process within pharmacist scope. Source: pharmacist role and USP hazardous workflow standards.
4. Correct answer: B — Hold release, verify the current governing source and worksheet validity, then document and escalate if needed
- A: Tempting because urgency and a complete label make release feel reasonable; incorrect because worksheet validity may affect whether the product was prepared under a current compliant process. The discriminating clue is worksheet may not match the latest source. Source: USP quality/documentation principles and institutional quality management.
- B: Tempting because it is conservative; correct because unresolved source-document discrepancy affecting release should trigger hold, verification, documentation, and escalation. The discriminating clue is uncertain current source alignment before release. Source: USP practice framework and quality systems principles.
- C: Tempting because it seems safety-first; incorrect because lack of revision date does not automatically prove contamination or require discard before verification. The discriminating clue is documentation uncertainty, not confirmed product compromise. Source: deviation investigation and quality management principles.
- D: Tempting because nurses may know the product’s routine use; incorrect because nursing familiarity does not verify source authority or worksheet currency. The discriminating clue is need for authoritative source verification. Source: pharmacist verification role.
5. Correct answer: B — Manufacturer labeling or authoritative drug information because the question is product-specific
- A: Tempting because external review sounds strong; incorrect because accreditation comments do not directly answer amphotericin’s required diluent. The discriminating clue is product-specific diluent question. Source: product labeling hierarchy for drug-specific details.
- B: Tempting because it directly matches the question; correct because D5W versus NS is a drug-specific preparation issue. The discriminating clue is diluent selection for one drug product. Source: FDA labeling, AHFS, Lexicomp, Clinical Pharmacology.
- C: Tempting because amphotericin is clinically high risk; incorrect because hazard level in a clinical sense does not make USP <800> the right source unless the drug is being handled as a hazardous drug under that framework. The discriminating clue is product-specific diluent, not hazardous containment workflow. Source: USP source function distinctions.
- D: Tempting because nursing handbooks discuss infusion administration; incorrect because they are not the best first authority for compounding preparation instructions. The discriminating clue is preparation clarification before compounding. Source: product-specific authoritative references.
6. Correct answer: C — Pause use of the shortcut, verify the governing sterile compounding source and current policy alignment, then escalate if inconsistent
- A: Tempting because local documents usually direct daily work; incorrect because they are not automatically controlling if they conflict with the current governing sterile compounding source. The discriminating clue is apparent inconsistency with the current department compounding manual. Source: USP <797> and policy-alignment principles.
- B: Tempting because urgency invites a temporary workaround; incorrect because urgency does not justify using an unverified shortcut that may affect sterile workflow integrity. The discriminating clue is workflow may contradict the governing source. Source: USP <797> conservative safety approach.
- C: Tempting because it may delay work; correct because this is the proper pharmacist response to a possible source conflict affecting sterile process. The discriminating clue is shortcut versus current manual discrepancy near the PEC. Source: USP <797> and quality escalation expectations.
- D: Tempting because accrediting organizations matter; incorrect because calling the accreditor for operational permission is outside the expected immediate pharmacist response. The discriminating clue is need for internal verification and escalation first. Source: institutional quality pathways and pharmacist role boundaries.
7. Correct answer: C — Stop the affected workflow, verify the governing hazardous source, document the conflict, and escalate per policy
- A: Tempting because posted signs feel official and operational; incorrect because a visible sign does not resolve conflict with a newer hazardous SOP. The discriminating clue is posted sequence conflicts with newly issued SOP. Source: USP <800> and policy currency principles.
- B: Tempting because it uses the newer document and avoids delay; incorrect because silently switching without documenting the discrepancy fails quality traceability and conflict resolution expectations. The discriminating clue is documented conflict requiring formal response. Source: quality management and hazardous compounding policy principles.
- C: Tempting because it is conservative; correct because hazardous workflow conflict with safety implications requires stop, verify, document, and escalate. The discriminating clue is hazardous CSP plus conflicting cleaning instructions. Source: USP <800> and institutional escalation practice.
- D: Tempting because oncologists own cancer therapy decisions; incorrect because cleaning-sequence governance is not a prescriber decision. The discriminating clue is operational hazardous handling issue rather than therapeutic choice. Source: pharmacist scope and hazardous workflow standards.
8. Correct answer: B — Manufacturer labeling or authoritative drug information, then apply institutional workflow controls
- A: Tempting because USP <797> is central to sterile compounding; incorrect because it does not contain every drug-specific diluent and concentration instruction. The discriminating clue is specific diluent and concentration limit question. Source: USP <797> role distinction.
- B: Tempting because it directly matches the missing information; correct because drug-specific instructions should come from authoritative product information, with local workflow controls applied after. The discriminating clue is SOP lacks drug-specific instructions. Source: FDA labeling, AHFS, Lexicomp, Clinical Pharmacology.
- C: Tempting because external standards feel authoritative; incorrect because accreditation is too broad and indirect for a precise drug-specific preparation question. The discriminating clue is need for exact diluent/concentration instruction. Source: accreditation versus product-reference distinction.
- D: Tempting because board rules are legally important; incorrect because jurisdictional law is not usually the first source for a specific antibiotic’s diluent and concentration limit. The discriminating clue is technical product preparation rather than legal authority. Source: source function framework.
Keep going with the full BCSCP Prep Course (BCSCP)
You just studied the way members do, in the same lesson interface. Full access unlocks every lesson, the question bank and flashcards for a full year.
One payment · 1 year of access · No auto-renewal