1.1.1 - Pharmacist Scope Boundaries
Why it matters BCNSP questions often test not just what is clinically desirable…
- 1 Why it matters BCNSP questions often test not just what is clinically desirable… 1:47
- 2 Key Terms & Must-Know Facts Key terms Verify: pharmacist review of order accura… 4:29
- 3 Do not independently diagnose, prescribe, place feeding access, place central a… 2:20
- 4 Body 4:03
- 5 Body 2:11
- 6 Core content 1.1.1.1 Foundational boundary: what the pharmacist may do versus m… 4:34
- 7 3 Safe action Recommend, document, and notify the correct clinician rather than… 3:21
- 8 Verify → the safest next step is to hold the current PN release for peripheral… 4:56
- 9 C: Tempting because pharmacists understand formulation limits; wrong because in… 4:13
- 10 If a critical detail is missing and your next action would commit the patient t… 4:14
- 11 Extract key facts → order-label mismatch, incomplete critical order information… 4:40
- 12 C: Correct because the product label and formula conflict on a clinically meani… 4:35
- 13 They may recommend options or monitoring priorities, but they should not assume… 4:11
- 14 Extract key facts → home PN order copied forward, recent change in insulin ther… 4:10
- 15 “Nursing should decide whether the insulin amount seems reasonable before the b… 3:54
- 16 Hold is appropriate when there is unresolved uncertainty that could affect pati… 4:13
- 17 Patient weight and current labs are otherwise stable; the family is waiting for… 3:57
- 18 The label infusion duration auto-populated from an old template, but the curren… 4:00
- 19 The single discriminator between modify and hold is whether the issue can be fu… 3:41
- 20 3 Communication check Notify the right clinician with a specific issue and reco… 3:53
- 21 Single clue that eliminates it: Final verification and release are pharmacist s… 4:19
- 22 HOLD/CLARIFY/ESCALATE: escalate immediately if anyone requests release of a pro… 1:02
- 23 Exam Traps & Differentiators Most common wrong answer and why: The most common… 3:45
- 24 “Label can be fixed later” Release defect; do not send a mismatched or incomple… 2:26
- 25 Tables Reference action When it applies What the pharmacist does What the pharm… 4:25
- 26 verified order is clear Modify within workflow No new therapeutic decision is b… 2:43
- 27 Algorithm / Approach Concept flow: BCNSP scope-boundary decision algorithm 1 Id… 2:16
- 28 Rapid Review Out-of-scope option → reject if it requires diagnosis, prescribing… 2:58
- 29 Self-check quiz 1. 6:16
- 30 Compound and dispense using the typed order, then correct the label after deliv… 5:00
- 31 Hold release pending reconciliation of the compounding record and required labe… 5:14
- 32 Assume central access is intended because the order appears to be central PN. 3:27
- 33 Answer key 1. 3:15
- 34 The single clue is that the current verified order already clearly states the i… 3:35
- 35 Sources: ASPEN; ASHP; AHFS Drug Information for electrolyte salts. 3:56
- 36 If you missed this: Review 1.1.1.3 Pharmacist communication: recommend, documen… 3:10
- 37 Sources: ASPEN; ASHP; AHFS electrolyte references. 3:10
- 38 Incorrect because converting to peripheral PN is a therapeutic reformulation ch… 2:54
Why it matters
- BCNSP questions often test not just what is clinically desirable, but what the pharmacist should do next within pharmacist scope.
- Many exam distractors are attractive because they sound clinically helpful but actually require prescriber authority, procedural authority, or site-specific authority not granted in the stem.
- Nutrition support is high risk: sterility failures, compatibility errors, route mismatches, and unclear orders can harm patients quickly; the safest correct answer is often hold and clarify.
- Professional-practice items reward patient protection, documentation, and communication over convenience, speed, or assumptions.
Key Terms & Must-Know Facts
1.1.1.1 Key terms
- Verify: pharmacist review of order accuracy, appropriateness, dose/rate, route, compatibility, and required safeguards before preparation or dispensing.
- Clarify: obtain needed information before proceeding when the order or clinical context is incomplete, ambiguous, or conflicting.
- Hold: stop preparation, verification, release, or continuation until a safety concern is resolved.
- Escalate: notify the prescriber, nutrition support team, supervisor, or other appropriate clinician when risk exceeds routine correction.
- Dispense/release: final product issue only after formulation, labeling, sterility workflow, and documentation checks are acceptable.
- Compatibility: whether components can be mixed or co-administered safely without precipitate, emulsion destabilization, or other harm.
- Stability: ability of a formulation to maintain intended physical and chemical integrity over time.
- Sterility assurance: compounding and handling processes that reduce contamination risk consistent with applicable standards and policy.
- Out-of-scope action: task beyond pharmacist authority in the scenario, such as diagnosing disease, placing a line, or independently prescribing therapy.
- Continue vs modify vs hold: the central decision framework for BCNSP practice stems.
- Operational discrepancy: mismatch in order, label, workflow, ingredients, access route, timing, or documentation that creates release risk.
- Pharmacist recommendation: communication of concerns or options without assuming prescriber authority.
1.1.1.2 Must-know facts
- The pharmacist’s safest default in unresolved high-risk situations is hold, clarify, document, and communicate.
- If the stem asks you to do something outside pharmacist scope, reject that option even if the clinical idea sounds reasonable.
- Do not independently diagnose, prescribe, place feeding access, place central access, or perform procedures reserved to others.
- Do not release a nutrition support product that has unresolved compatibility, stability, labeling, sterility, or order discrepancy concerns.
- Patient safety outranks workflow speed; “send now and fix later” is usually wrong on this exam.
- When local policy or jurisdiction may vary, choose the answer that follows core pharmacist responsibilities and defers to current standards and institutional policy.
- In a board-style item, the “most appropriate next step” often hinges on the single unresolved safety fact.
- Documentation is part of the correct action, not an afterthought.
Memory anchor: Think V-H-C-E-D = Verify, Hold, Clarify, Escalate, Document. When the stem feels risky or incomplete, run this sequence before considering continuation.
Exam takeaway: Separate pharmacist actions from prescriber-only or procedure-only actions before choosing the next step.
flowchart LR
A[Order or patient issue appears] --> B{Within pharmacist scope?}
B -->|Yes| C[Verify, calculate, monitor, document, communicate]
B -->|No| D[Hold and clarify with prescriber or team]
C --> E{Safe and complete?}
E -->|Yes| F[Prepare or release per standards]
E -->|No| D
D --> G[Escalate unresolved safety concern]
See Fig 1. This figure is the central mental model for the lesson: first decide scope, then decide safety, then decide action.
Exam takeaway: An unresolved safety variable usually beats convenience, timing pressure, and incomplete assumptions.
flowchart TD
A[PN or EN order arrives] --> B{Order complete and interpretable?}
B -->|No| H[Hold and clarify]
B -->|Yes| C{Compatibility, stability, route, access, label all acceptable?}
C -->|No| H
C -->|Yes| D{Clinical monitoring acceptable for continuation?}
D -->|No| E[Recommend modify or monitor and communicate]
D -->|Yes| F[Proceed with verification and release]
H --> G[Document issue and notify appropriate clinician]
See Fig 2. Many test items reduce to this: if a key variable is unresolved, continuation is premature.
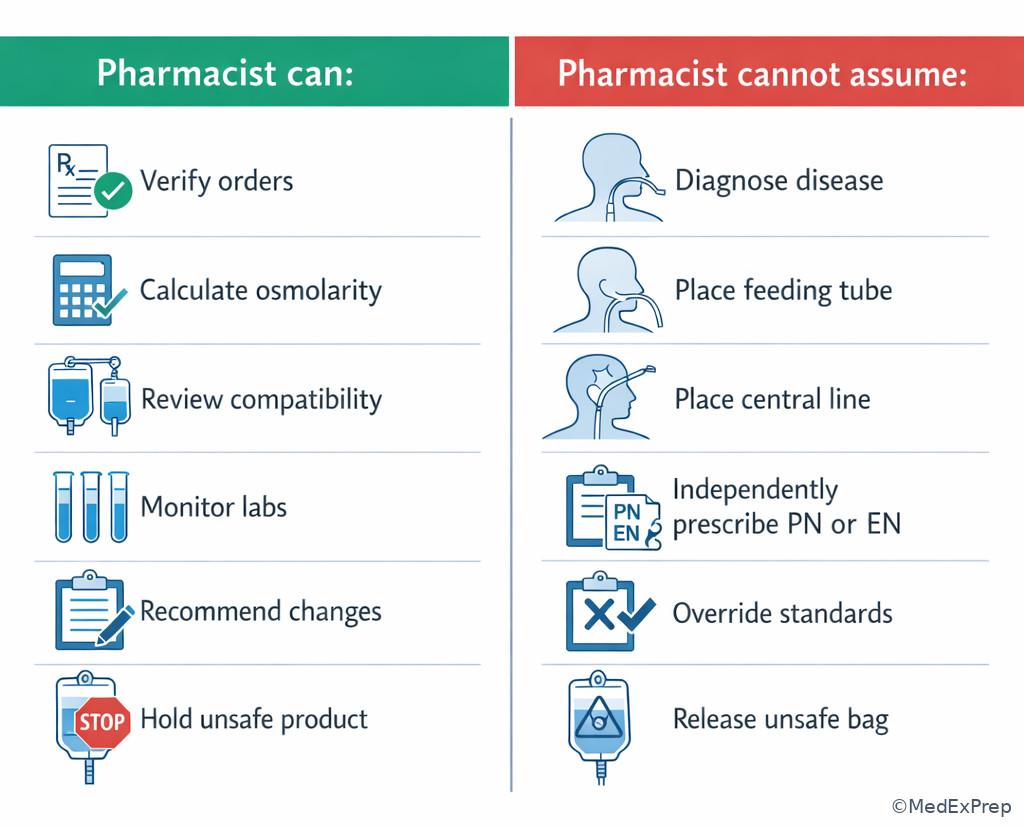
Exam takeaway: Pharmacists own verification, compounding oversight, release checks, monitoring support, and communication, not diagnosis or procedures.
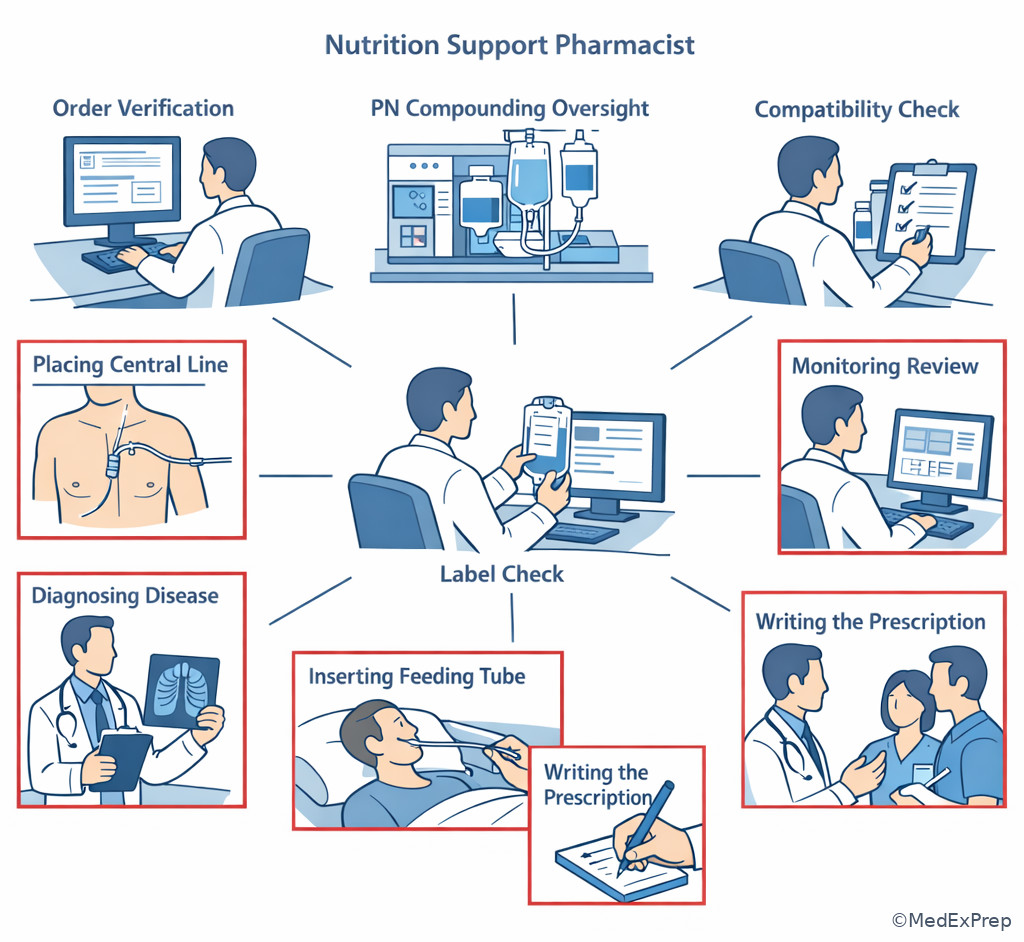
See Fig 3. Use it to rapidly sort “can do,” “can recommend,” and “must not do.”
Exam takeaway: Route mismatch, access mismatch, missing data, and compounding concerns are classic triggers to hold and clarify.
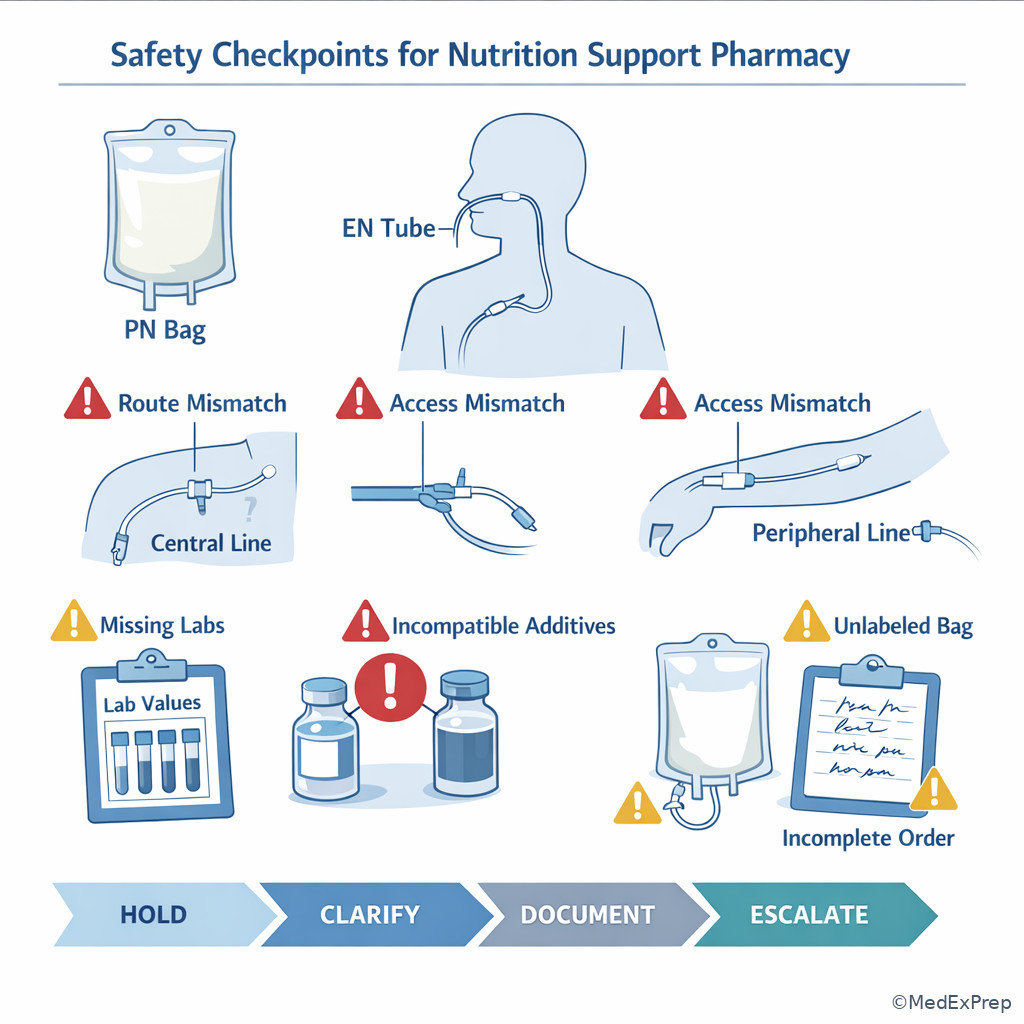
See Fig 4. This is the exam’s favorite safety pattern: one red flag is enough to stop release.
Exam takeaway: The correct answer often includes what to say, whom to notify, and what to document after the hold decision.
flowchart LR
A[Notice discrepancy] --> B[Pause verification or release]
B --> C[Gather exact missing or conflicting facts]
C --> D[Contact prescriber or team with specific concern]
D --> E[Recommend safe options within scope]
E --> F[Document action and outcome]
F --> G[Reassess before proceeding]
See Fig 5. High-scoring answers include both the safety action and the communication step.
Exam takeaway: A visual checklist helps you spot the one unresolved variable that controls the answer.
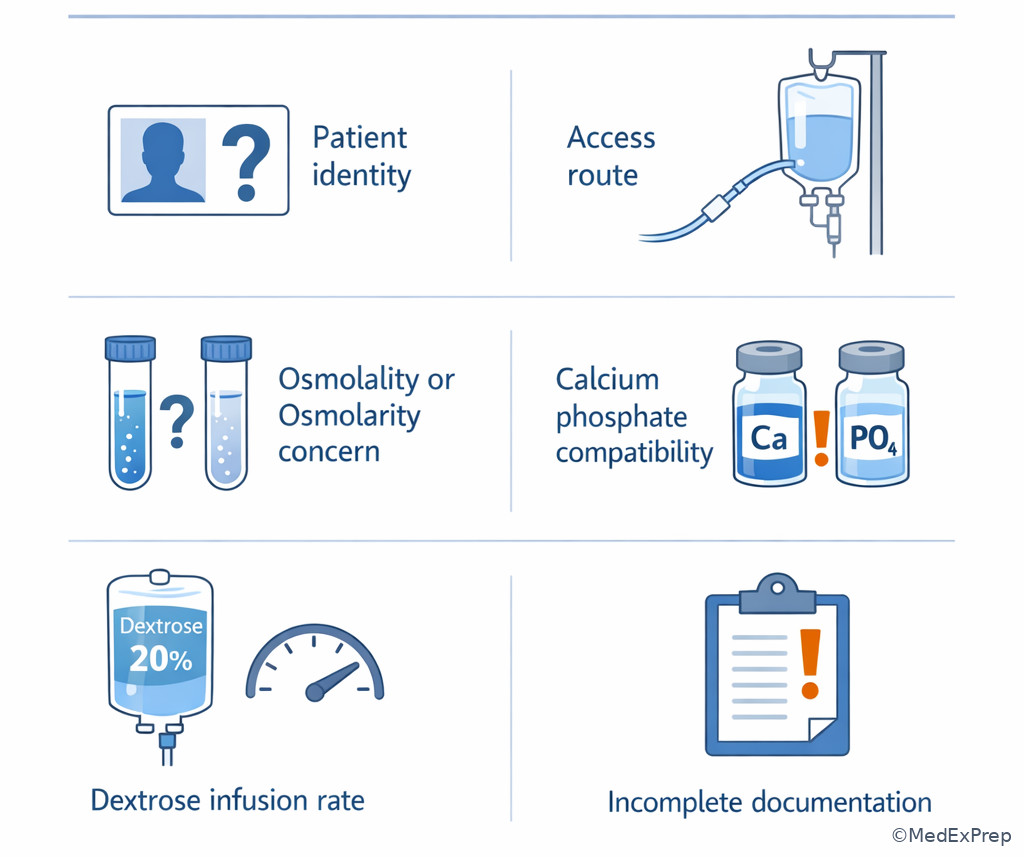
Exam takeaway: Release decisions should follow safety checkpoints rather than staffing pressure or timing pressure.
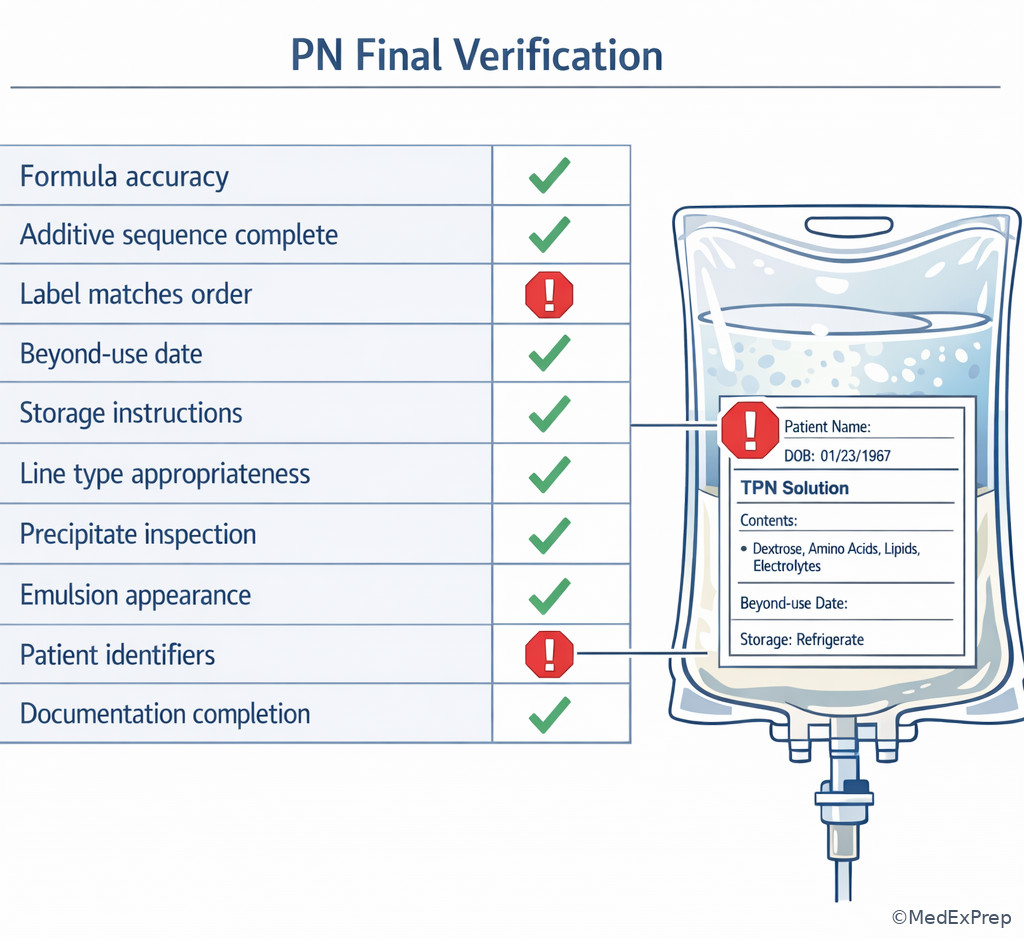
Exam takeaway: Pharmacists protect patients by escalating to the right team member, not by assuming another discipline’s role.

Exam takeaway: Knowing the forbidden actions is just as testable as knowing the appropriate pharmacist actions.
Core content
1.1.1.3 Foundational boundary: what the pharmacist may do versus must not do
A Explanation
A common BCNSP decision conflict is choosing between an action that seems clinically helpful and the action that is actually within pharmacist scope. The exam tests whether you can separate pharmacist responsibilities from prescriber or procedural responsibilities. The pharmacist may verify the order, assess whether it is safe to prepare or dispense, identify formulation or route concerns, calculate doses and rates, review compatibility and stability, monitor and interpret labs, recommend modifications, document, and communicate with the team. The pharmacist must reject options that require independently diagnosing the patient, writing or independently authorizing the nutrition support regimen as the treating clinician, placing access devices, inserting feeding tubes, or releasing an unsafe product simply because therapy is urgent.
WHY THIS IS TESTED: board questions frequently present a time-sensitive situation and tempt you to “solve the whole case.” The testable pattern is that the correct answer stays inside pharmacist authority while still protecting the patient. In practice terms, choose recommend and clarify, reject prescribe or perform.
Key rule: If the option asks you to act as the treating physician, proceduralist, or final diagnosing clinician, it is outside scope unless the stem explicitly grants authority.
Recall: In the course introduction, we framed this exam around pharmacist judgment rather than physician management. Here, we build on that by drawing a hard line between pharmacist-owned safety steps and out-of-role actions.
B Worked example
A 68-year-old man with short bowel syndrome, chronic kidney disease stage 3, and insulin-treated diabetes has a pending central PN order: dextrose 300 g/day, amino acids 90 g/day, SMOF lipid 50 g/day, potassium phosphate 30 mmol, magnesium sulfate 16 mEq, multivitamins, and trace elements. The nurse notes that the patient’s tunneled line was removed 2 hours ago for suspected infection, and a peripheral IV is currently in place. A resident verbally says, “Just start this now through the peripheral line until we sort out the central access.” The patient also has a mildly elevated AST, which is distracting but not the key issue.
Reasoning chain: Identify task → pharmacist must decide whether to verify/release and what to communicate. Extract key facts → central PN order, current access is peripheral only, urgent verbal request, suspected line infection. Apply rule → pharmacist can assess route appropriateness and hold unsafe administration; pharmacist cannot independently rewrite the regimen, place access, or authorize unsafe infusion. Eliminate distractors → do not send as-is through peripheral access; do not independently convert to peripheral PN unless prescriber clarification and site policy support a safe revised formula. Verify → the safest next step is to hold the current PN release for peripheral administration, notify the prescriber that access does not match the order and route limits must be clarified, document the intervention, and recommend evaluation of alternative nutrition support options consistent with policy.
C Exam trap
Common wrong answer: “Modify the current central PN yourself to a peripheral formulation and send it immediately.”
Why it is tempting: It sounds proactive and patient-centered, and pharmacists do perform calculations and formulation review.
Single clue that eliminates it: The stem never grants authority to independently prescribe or rewrite the nutrition regimen; the current order and current access are mismatched, so the pharmacist must hold and clarify rather than unilaterally create a new treatment plan.
D Checkpoint
Question: A pharmacist receives an order to begin a high-osmolarity PN formulation through a peripheral catheter because central access was lost overnight. Which is the most appropriate next step?
- A. Verify and dispense the PN because the patient still needs nutrition support.
- B. Hold the order, clarify route/access appropriateness with the prescriber, document the concern, and recommend a safe alternative if needed.
- C. Independently write a new lower-osmolarity peripheral PN order and dispense it.
- D. Ask nursing to temporarily infuse the PN at half-rate through the peripheral catheter until rounds.
Answer: B
- A: Tempting because nutrition should not be delayed; wrong because need for nutrition does not override route safety and order mismatch.
- B: Correct because it keeps the pharmacist within scope and addresses the access-risk conflict directly.
- C: Tempting because pharmacists understand formulation limits; wrong because independent prescribing or regimen rewriting is not granted.
- D: Tempting because rate reduction sounds safer; wrong because rate reduction does not fix the fundamental route/access problem.
Pharmacist Action: NOTICE: any order that assumes the wrong access type or requires a procedure. SAY: “The current access does not support this ordered therapy safely; I need to hold and clarify before release.” MONITOR: access type, order-route match, and urgency at each verification. HOLD/CLARIFY/ESCALATE: hold immediately when ordered therapy exceeds current route or access limits.
1.1.1.4 Safety triggers that require hold and clarify
A Explanation
The second foundational skill is recognizing the specific triggers that convert a routine order into a do not proceed yet situation. On the BCNSP exam, these triggers are often practical rather than dramatic: incomplete order elements, incompatible additives, route mismatch, impossible rate instructions, missing patient identifiers, unclear electrolyte salt or dose, unresolved allergy information, missing key labs in a high-risk patient, or product labeling that does not match the verified order. The decision conflict is whether to keep workflow moving or stop the process. The single finding that resolves it is any unresolved safety variable that materially affects formulation, administration, or monitoring.
WHY THIS IS TESTED: the exam wants pharmacists who protect patients from preventable harm. You are not rewarded for assumptions. If a critical detail is missing and your next action would commit the patient to a potentially unsafe product or administration route, you hold and clarify first. See Fig 4 and Fig 5.
Key rule: “I can probably infer what they meant” is usually dangerous exam reasoning. If the missing fact changes safety, the product is not ready for release.
High-Yield Connection: This concept is tested alongside Aseptic Technique Principles and Labeling And Product Release. Know both the clinical safety trigger and the operational release rule for exam day — they are frequently paired in stems.
B Worked example
A 54-year-old woman with metastatic ovarian cancer, severe malnutrition, and a history of recurrent catheter-related bloodstream infection is receiving home PN. Today’s order includes dextrose 220 g, amino acids 75 g, lipids 40 g, sodium acetate 80 mEq, potassium chloride 60 mEq, calcium gluconate 10 mEq, magnesium sulfate 12 mEq, multivitamins, and trace elements. The faxed order is missing patient weight, contains no phosphorus entry despite recent refeeding concern in the chart, and the printed label draft lists potassium acetate instead of potassium chloride. Her bilirubin is mildly elevated, which is distracting. The delivery deadline is in 30 minutes.
Reasoning chain: Identify task → decide whether to compound and release. Extract key facts → order-label mismatch, incomplete critical order information, recent refeeding concern, home PN setting, deadline pressure. Apply rule → unresolved mismatch and omitted clinically important information that may affect formulation require hold and clarification. Eliminate distractors → do not assume the intended potassium salt; do not release with a “note to fix later”; do not rely on deadline pressure. Verify → hold compounding or release, contact the prescriber/team to reconcile the discrepancy and current electrolyte plan, document the intervention, then proceed only when the final verified order matches the label and clinical plan.
C Exam trap
Common wrong answer: “Compound according to the typed order and add a note that the label will be corrected after delivery.”
Why it is tempting: It seems operationally efficient and avoids therapy delay.
Single clue that eliminates it: The label does not match the verified formula, which is a release-level safety problem, not a clerical detail to defer.
D Checkpoint
Question: Which unresolved issue most clearly requires the pharmacist to hold PN release rather than proceed?
- A. A mildly elevated bilirubin in a patient already receiving chronic PN.
- B. A delivery cutoff time that will be missed if clarification is requested.
- C. A mismatch between the PN order’s potassium salt and the printed label’s potassium salt.
- D. A stable patient who prefers infusion start at 8 PM instead of 7 PM.
Answer: C
- A: Tempting because hepatic markers matter in PN monitoring; wrong because this alone does not automatically prevent release of an otherwise correct order.
- B: Tempting because timing pressure is real in practice; wrong because deadlines never override a material safety discrepancy.
- C: Correct because the product label and formula conflict on a clinically meaningful component.
- D: Tempting because administration timing matters operationally; wrong because patient preference does not create a release-level safety stop.
Pharmacist Action: NOTICE: order-label mismatches, additive ambiguities, and missing data with safety implications. SAY: “I cannot release this PN until the formula, label, and clinical intent match.” MONITOR: order completeness and release documentation every verification cycle. HOLD/CLARIFY/ESCALATE: escalate when discrepancies remain unresolved despite attempted clarification.
- The safest default for an unresolved material discrepancy is hold and clarify.
- True or False: A delivery deadline can justify releasing a mislabeled PN product. False.
- Name 3 classic hold triggers: route/access mismatch, order-label mismatch, unresolved compatibility/stability concern.
1.1.1.5 Pharmacist communication: recommend, document, and escalate without overstepping
A Explanation
Once you identify that the order cannot proceed safely, the next tested skill is how the pharmacist should act. The exam is not satisfied with “hold” alone. You should also choose the option that communicates the concern clearly, gives a pharmacist-level recommendation when appropriate, documents the issue, and escalates if the risk remains unresolved. The decision conflict is between passively delaying and actively closing the loop. The resolving rule is simple: pharmacists should be specific about the problem, specific about the risk, and specific about what needs clarification. They may recommend options or monitoring priorities, but they should not assume prescriber authority.
WHY THIS IS TESTED: patient safety depends on action that is both limited and effective. A pharmacist who simply says “this seems wrong” without identifying the exact discrepancy has not completed the job. On the other hand, a pharmacist who writes a new therapy plan without authority has crossed the boundary. See Fig 5.
Key rule: A strong pharmacist response names the issue, the risk, the needed clarification, and the documentation step.
Memory anchor: Use I-R-A-D = Issue, Risk, Ask, Document. It turns vague concern into exam-ready pharmacist communication.
B Worked example
A 43-year-old man with Crohn disease, high-output ostomy, and recent acute kidney injury is admitted for dehydration and is being restarted on PN. The order includes dextrose 350 g/day and insulin regular 40 units in the bag. His current glucose today ranges from 88 to 116 mg/dL because he has been NPO with an insulin infusion that was discontinued one hour ago. A covering prescriber writes, “continue home PN exactly.” The patient’s magnesium is slightly low, which is relevant but not the decisive issue.
Reasoning chain: Identify task → pharmacist must determine the most appropriate communication and verification action. Extract key facts → home PN order copied forward, recent change in insulin therapy, current glucose lower than expected, inpatient context changed. Apply rule → pharmacist can identify that the copied insulin dose may no longer match the current clinical setting and should clarify the dextrose/insulin plan before release. Eliminate distractors → do not silently remove the insulin from the PN without discussion; do not compound “because it was the home dose”; do not diagnose the glycemic disorder. Verify → contact the prescriber/team with the specific discrepancy between historical PN insulin and current inpatient glucose context, recommend review of insulin-in-PN dosing strategy, document, and proceed only after clarification.
C Exam trap
Common wrong answer: “Just remove the insulin from the PN bag and send it, because the current glucose is normal.”
Why it is tempting: It looks like a cautious correction and uses pharmacist formulation expertise.
Single clue that eliminates it: The question tests communication and authority; the pharmacist identified a concern but cannot independently alter a therapeutically meaningful order component without clarification in this scenario.
D Checkpoint
Question: Which pharmacist statement best stays within scope while addressing a potentially unsafe copied-forward PN order?
- A. “I changed the insulin dose in the PN because the current glucose values look lower.”
- B. “The PN was continued as written because this was the patient’s home regimen.”
- C. “The copied insulin-in-PN dose may not reflect the current inpatient status; I am holding verification and requesting clarification of the dextrose and insulin plan.”
- D. “Nursing should decide whether the insulin amount seems reasonable before the bag is dispensed.”
Answer: C
- A: Tempting because pharmacists often identify dose concerns; wrong because it assumes independent therapeutic authority.
- B: Tempting because continuity with home therapy often matters; wrong because copied-forward regimens must still match current clinical conditions.
- C: Correct because it names the issue, states the action, and remains within pharmacist scope.
- D: Tempting because nurses are key partners; wrong because the pharmacist cannot offload the verification responsibility.
Pharmacist Action: NOTICE: copied-forward orders, verbal shortcuts, and “same as before” requests. SAY: “This historical regimen may not match the current clinical picture; I need clarification before verification.” MONITOR: handoff changes, prior-to-current order differences, and documented callback resolution. HOLD/CLARIFY/ESCALATE: escalate if urgent therapy pressure persists despite unresolved risk.
1.1.1.6 Distinguishing modify versus continue versus hold in real nutrition support workflows
A Explanation
The most nuanced foundational judgment is deciding among continue, modify, and hold. The exam often gives several plausible pharmacist actions from the same general category, so you need the discriminating rule. Continue is appropriate when the order is complete, safe, and consistent with the clinical situation. Modify is appropriate when a pharmacist-level adjustment is clearly within established authority or standard verification workflow in the stem or policy context. Hold is appropriate when there is unresolved uncertainty that could affect patient safety, formulation integrity, route suitability, or regulatory compliance. The decision conflict is whether an issue is a routine adjustment or a stop-level discrepancy. The single finding that resolves it is whether the pharmacist can fully correct the issue within authority and without assumption.
WHY THIS IS TESTED: this is the core operational reasoning model for BCNSP. Future topics will attach formulas, monitoring, compatibility, and complications to this same action grid. The exam rewards a structured answer: identify the discrepancy, decide if it is pharmacist-correctable, and if not, hold and clarify.
High-Yield Connection: This concept is tested alongside the upcoming Exam Reasoning Framework. Know the sequence identify task → extract key facts → apply rule → execute → verify; scope-boundary questions are the simplest place to build that habit.
B Worked example
A 59-year-old woman with chronic intestinal failure, heart failure with reduced ejection fraction, and chronic hyponatremia receives home PN five nights per week. Today’s refill order matches the prior formula except the bag label auto-populates the old infusion duration of 12 hours, while the current verified order says 14 hours because of prior intolerance at the faster rate. Patient weight and current labs are otherwise stable; the family is waiting for courier pickup. This is a real discrepancy, but unlike a route mismatch, the error is fully identifiable and correctable within pharmacist workflow.
Reasoning chain: Identify task → determine whether to continue, modify, or hold. Extract key facts → order-label mismatch on infusion duration, current intended schedule already verified, no need for new prescribing, release not yet final. Apply rule → when the pharmacist can correct a clerical or transcription-related release problem within established workflow and verify the corrected label matches the authorized order, modification/correction is appropriate. Eliminate distractors → do not send the old label; do not hold therapy indefinitely when the discrepancy is fully correctable before release; do not ask the patient to “remember the correct duration.” Verify → correct the label to match the verified order, complete standard final check, document per workflow, and release only after the corrected product is accurate.
C Exam trap
Common wrong answer: “Because every discrepancy is unsafe, hold the bag until tomorrow even though the error is only a correctable label duration typo.”
Why it is tempting: After learning “hold if unsafe,” learners can overapply the rule to issues the pharmacist can actually resolve before release.
Single clue that eliminates it: The discrepancy is fully correctable within pharmacist verification workflow and does not require new clinical authorization if the current verified order is already clear.
D Checkpoint
Question: Which situation most supports pharmacist correction and continuation rather than hold-and-clarify?
- A. The order specifies central PN, but the patient has only peripheral access.
- B. The label infusion duration auto-populated from an old template, but the current verified order clearly lists the intended duration and the product has not yet been released.
- C. The phosphate dose is missing from the order in a patient at refeeding risk.
- D. The prescriber requests a verbal change to “adjust electrolytes as needed” without specifics.
Answer: B
- A: Tempting because route issues can feel operationally fixable; wrong because route/access mismatch is a stop-level clinical safety issue.
- B: Correct because the pharmacist can correct the release documentation to match the already authorized and verified order.
- C: Tempting because pharmacists understand refeeding concerns; wrong because a missing therapeutic component in a high-risk patient requires clarification.
- D: Tempting because pharmacists often help adjust electrolytes; wrong because the requested change lacks specific authorized instructions.
Pharmacist Action: NOTICE: whether the problem is clerical-and-correctable or clinically unresolved. SAY: “This can be corrected within verification” versus “This requires prescriber clarification before release.” MONITOR: final label accuracy, release checklist completion, and documentation closure. HOLD/CLARIFY/ESCALATE: escalate when pressure to proceed persists despite an unresolved stop-level discrepancy.
- True or False: Every discrepancy requires prescriber clarification. False — some are pharmacist-correctable release errors.
- The single discriminator between modify and hold is whether the issue can be fully corrected within scope and without assumption.
- Name the three action buckets: continue, modify, hold.
1.1.1.7 Integrating scope boundaries with safety, sterility, compliance, and exam reasoning
A Explanation
The final integration step is understanding why scope boundaries matter beyond professional etiquette: they are the mechanism by which the pharmacist protects sterility assurance, compatibility standards, documentation integrity, and patient safety. A pharmacist who compounds or releases an unclear PN order does not merely cross a role boundary; that choice can create a mislabeled, unstable, incompatible, or otherwise unsafe product. The decision conflict is between solving the clinical need quickly and preserving the full safety chain. The single resolving rule is that unresolved process risk is still patient risk. Questions in this lesson are foundational, but the same structure will later appear in calcium-phosphate compatibility, aseptic workflow, labeling and release, and complication management.
WHY THIS IS TESTED: BCNSP is a pharmacist certification, not a pure therapeutics exam. The safest answer often combines pharmacist scope, operational standards, and the duty to prevent unsafe release. See Fig 1 through Fig 5.
Key rule: If a product is not safe to verify, not safe to compound, or not safe to release, the correct action is not “try your best.” It is to stop the unsafe step and close the gap.
B Worked example
A 72-year-old man with pancreatic cancer, cholestasis, and severe weight loss is receiving compounded PN in the hospital. During final verification, the pharmacist notices that the preparation record is incomplete, one additive entry is handwritten and difficult to read, and the final bag label omits storage instructions required by site process. The nurse calls twice asking for immediate delivery because the patient missed the previous evening’s infusion. The patient’s sodium is mildly low, which may catch attention but is not the release-determining fact.
Reasoning chain: Identify task → decide whether to release an already compounded product. Extract key facts → incomplete compounding record, ambiguous documentation, label omission, time pressure. Apply rule → the pharmacist is responsible for preventing unsafe or noncompliant release; unresolved documentation and labeling concerns can invalidate safe release. Eliminate distractors → do not release because therapy is overdue; do not “fix the chart later”; do not assume the handwritten entry was intended correctly. Verify → quarantine or hold release pending reconciliation according to policy, notify the appropriate team, document the issue, and only release after required verification elements are complete.
C Exam trap
Common wrong answer: “Because the bag is already compounded, release it now and complete the record afterward.”
Why it is tempting: Learners may think the main risk is during compounding rather than during release.
Single clue that eliminates it: Final verification and release are pharmacist safety functions; unresolved documentation and label defects mean the product is not ready to leave pharmacy control.
D Checkpoint
Question: During final PN verification, which finding most clearly requires the pharmacist to prevent product release until resolved?
- A. The patient missed the previous infusion and nursing requests immediate delivery.
- B. The patient has mild hyponatremia that is already known to the team.
- C. The compounding record is incomplete and the final label omits required release information.
- D. The patient’s infusion normally begins one hour earlier than today.
Answer: C
- A: Tempting because delayed therapy matters; wrong because urgency does not overrule release requirements.
- B: Tempting because electrolyte abnormalities are common PN monitoring triggers; wrong because this finding alone does not answer the release question.
- C: Correct because incomplete record and labeling defects are direct barriers to safe and compliant release.
- D: Tempting because infusion timing can matter operationally; wrong because timing change alone is not the primary release stop here.
Pharmacist Action: NOTICE: incomplete records, illegible entries, unlabeled or mismatched products, and requests to bypass release steps. SAY: “I cannot release this product until the verification and documentation requirements are complete.” MONITOR: final verification checklist, label completeness, and release documentation every batch. HOLD/CLARIFY/ESCALATE: escalate immediately if anyone requests release of a product that fails required safeguards.
Exam Traps & Differentiators
Most common wrong answer and why: The most common wrong answer is the option that sounds decisive and clinically helpful but requires authority not granted in the stem. Examples include independently changing the regimen, authorizing a different route, instructing a procedure, or releasing an unsafe product because “the patient needs nutrition.” These are tempting because they appear proactive. The differentiator is the single unresolved safety or authority variable.
| Looks similar | Actually means | Correct pharmacist response | Discriminator |
|---|---|---|---|
| Recommend a therapy adjustment | Communicate a pharmacist-level suggestion | Clarify with prescriber and document | No independent prescribing authority stated |
| Correct a label typo before release | Pharmacist-correctable workflow error | Modify within workflow, re-verify, then release | Current verified order is already clear |
| Proceed despite route mismatch | Unsafe administration risk | Hold and clarify | Current access cannot support ordered therapy safely |
| Release and document later | Bypassing final safety controls | Prevent release until complete | Required release elements are unresolved |
| Ask another discipline to decide if it is okay | Deflecting pharmacist verification duty | Own the safety screen and contact the right clinician | Verification remains pharmacist responsibility |
| If the stem says… | Think… |
|---|---|
| “Can you just send it now?” | Time pressure is probably a distractor; re-check for a release-level safety issue. |
| “Use the old order” or “same as home” | Copied-forward orders may not fit the current clinical picture; verify before continuing. |
| “The line was removed” or “peripheral access only” | Route/access mismatch is a classic hold-and-clarify trigger. |
| “Label can be fixed later” | Release defect; do not send a mismatched or incomplete product. |
| “The resident verbally said…” | Look for incomplete authorization details and clarify specifics before action. |
| “Missing weight/labs/electrolyte details” in a high-risk patient | Do not infer critical data that materially changes safety or formulation. |
Common traps & distractors: A safe recommendation is not the same as an authorized order; a compounded product is not automatically releasable; a copied-forward regimen is not automatically appropriate; and another team member’s urgency does not remove the pharmacist’s safety duty.
Related traps recur in Aseptic Technique Principles, Compounding Error Prevention, and Labeling And Product Release, where the confusing pair is often “workflow convenience” versus “required safeguard.”
Tables
| Reference action | When it applies | What the pharmacist does | What the pharmacist does not do |
|---|---|---|---|
| Continue | Order is complete, safe, and release-ready | Verify, prepare/release, document, monitor | Ignore new risks or skip final checks |
| Modify | Issue is correctable within workflow and authority | Correct, re-verify, document | Assume new therapeutic authority |
| Hold | Safety-critical issue unresolved | Pause process, clarify, document | Proceed based on assumption |
| Escalate | Risk persists or exceeds routine correction | Notify prescriber/team/supervisor per policy | Quietly release or ignore concern |
| Recommend | Therapeutic or operational concern identified | Suggest pharmacist-level options with rationale | Write or independently authorize treatment if not granted |
| Document | Every intervention or release decision | Record issue, communication, outcome | Rely on memory or verbal-only closure |
| Comparison point | Within pharmacist scope | Outside pharmacist scope in this exam context |
|---|---|---|
| Order review | Assess appropriateness, compatibility, stability, route, dose, rate | Assume medical diagnosis independently |
| Therapy changes | Recommend changes and clarify orders | Independently prescribe or rewrite regimen unless authority is explicitly granted |
| Access decisions | Identify mismatch between access and ordered therapy | Place central line or feeding tube |
| Compounding | Prepare, verify, and release only if standards are met | Release products with unresolved safety defects |
| Monitoring | Interpret labs and identify needed action or clarification | Ignore abnormal trends because another discipline is involved |
| Documentation | Document discrepancies and interventions | Bypass required records to save time |
| Differential scenario type | Best action | Why |
|---|---|---|
| Correctable label auto-population error before release, verified order is clear | Modify within workflow | No new therapeutic decision is being made |
| Central PN order but only peripheral access available | Hold and clarify | Route/access mismatch creates unsafe administration risk |
| Missing phosphorus in a patient at refeeding risk | Hold and clarify | Missing therapeutic component changes clinical safety |
| Incomplete compounding record at final check | Prevent release and escalate per workflow | Product is not release-ready |
| Stable, complete, correctly labeled, verified PN order | Continue | No unresolved safety or authority conflict |
| Prescriber asks pharmacist to “adjust as needed” without specifics | Clarify details before proceeding | Instruction is too vague for safe authorization |
Algorithm / Approach
This algorithm becomes the base framework for later lessons on calculations, route selection, compatibility, compounding, and monitoring.
Rapid Review
- Out-of-scope option → reject if it requires diagnosis, prescribing independently, or performing a procedure.
- Route/access mismatch → hold, clarify, do not “temporarily send.”
- Order-label mismatch → release stop until reconciled.
- Copied-forward regimen → verify against current clinical context, not past routine.
- Deadline pressure → distractor unless safety is already resolved.
- Correctable clerical release error → modify within workflow, then re-verify.
- Missing therapeutic detail that changes safety → clarify before compounding or release.
- Already compounded bag with unresolved defect → still do not release.
- Recommendation versus authorization → pharmacists may suggest; they do not assume prescriber authority unless explicitly granted.
- Final verification duty → cannot be delegated away because another discipline is busy.
- Strong intervention note → names issue, risk, contact, and outcome.
- Exam “best next step” → usually hinges on one unresolved material variable.
- Patient need for nutrition → does not justify bypassing sterility, compatibility, or release safeguards.
Self-check quiz
1. A pharmacist receives a PN order for dextrose 250 g IV continuous over 24 hours via central line, amino acids 80 g IV continuous, and potassium phosphate 20 mmol in the bag. The chart now shows only a peripheral catheter after the central line was removed. What is the most appropriate next step?
- A. Verify and dispense the PN through the peripheral catheter at half-rate.
- B. Hold the order, clarify route/access with the prescriber, document the concern, and recommend a safe alternative if needed.
- C. Independently rewrite the order as peripheral PN and dispense it.
- D. Ask nursing to decide whether peripheral infusion is acceptable.
2. A home PN refill for amino acids 70 g IV, dextrose 200 g IV, lipids 35 g IV, infused over 14 hours is otherwise unchanged. During final check, the printed label lists the prior duration of 12 hours, while the current verified order clearly states 14 hours. Which action is most appropriate?
- A. Correct the label within workflow, re-verify against the current order, document, and release if all else is accurate.
- B. Release the bag with the incorrect label because the patient knows the correct infusion time.
- C. Hold the bag until the prescriber writes an entirely new order.
- D. Ask the courier to explain the correct infusion duration at delivery.
3. A 61-year-old woman with metastatic gastric cancer, chronic kidney disease, and severe malnutrition has a PN order for dextrose 280 g/day IV, amino acids 90 g/day IV, SMOF lipid 50 g/day IV, calcium gluconate 12 mEq, and potassium chloride 50 mEq. The typed order lists potassium chloride, but the draft label lists potassium acetate. She is due for discharge this afternoon. What is the pharmacist’s most appropriate next step?
- A. Compound and dispense using the typed order, then correct the label after delivery.
- B. Hold release, clarify the intended potassium salt, reconcile the label and formula, document, and proceed only after the final verified order matches.
- C. Choose potassium acetate because it may be preferable in acidosis and dispense immediately.
- D. Release the product because both salts provide potassium and the difference is minor.
4. A 48-year-old man with Crohn disease, short bowel syndrome, and insulin-treated diabetes is admitted on home PN: dextrose 320 g IV, amino acids 100 g IV, regular insulin 36 units in the bag. Today his glucose values are 85 to 110 mg/dL after several changes in inpatient insulin therapy. The covering prescriber writes, “continue home PN as before.” What is the most appropriate pharmacist action?
- A. Remove the insulin from the PN bag independently and dispense the revised formulation.
- B. Verify the old PN formula because it has been tolerated at home.
- C. Hold verification, contact the prescriber to clarify whether the prior insulin-in-PN dose still matches the current inpatient plan, document, and then proceed.
- D. Tell nursing to use sliding-scale insulin instead of clarifying the PN order.
5. A 67-year-old man with pancreatic cancer, cholestasis, and weight loss has a compounded PN bag containing dextrose 240 g IV, amino acids 85 g IV, and lipids 45 g IV. During final verification, the compounding record is incomplete and the final label omits a required storage instruction. The nurse requests immediate delivery because the previous dose was delayed. What is the most appropriate next step?
- A. Release the bag now and complete the documentation later because the product is already compounded.
- B. Hold release pending reconciliation of the compounding record and required labeling elements, document the issue, and escalate per workflow if needed.
- C. Send the bag and verbally tell nursing the missing storage instruction.
- D. Ask the nurse to document the missing verification information on behalf of pharmacy.
6. A 72-year-old woman with chronic intestinal failure, heart failure, and recurrent electrolyte instability has a new PN order: dextrose 210 g IV nightly over 14 hours, amino acids 75 g IV nightly, sodium acetate 60 mEq, potassium phosphate 12 mmol, and magnesium sulfate 10 mEq. The prescriber also writes, “adjust electrolytes as needed.” Her current labs show sodium 132 mEq/L and phosphorus 2.5 mg/dL. Which pharmacist action is most appropriate?
- A. Increase phosphate and magnesium based on current labs, document the change, and dispense.
- B. Verify the order as written because the phrase “as needed” gives adequate flexibility.
- C. Clarify the specific electrolyte changes authorized before modifying the order, document the communication, and proceed only once the therapeutic intent is explicit.
- D. Omit all electrolytes from the bag to avoid making an unauthorized change.
7. A 58-year-old man with sepsis, acute kidney injury, and severe protein-calorie malnutrition has an urgent PN order: dextrose 300 g IV continuous, amino acids 95 g IV continuous, lipids 40 g IV daily. The resident verbally asks pharmacy to “just start it through whatever access is available,” but the line documentation is conflicting: one note says central venous catheter, another says peripheral midline, and bedside nursing cannot confirm. Which is the most appropriate pharmacist action?
- A. Proceed with compounding and let nursing determine the line type at administration.
- B. Assume central access is intended because the order appears to be central PN.
- C. Hold verification until the access type is definitively confirmed, communicate the route-safety concern, document, and then reassess the order.
- D. Convert the formulation to peripheral PN and send it to avoid delay.
8. A 63-year-old woman on home PN for chronic bowel obstruction has a refill order for dextrose 230 g IV, amino acids 80 g IV, lipids 40 g IV, multivitamins, and trace elements. The prescriber’s office sends a signed order, but the fax is partially cut off so the electrolyte section is unreadable. The prior month’s formula is available in the chart, and courier pickup is scheduled in 20 minutes. What is the most appropriate pharmacist action?
- A. Use last month’s electrolyte formula because continuity is usually appropriate in home PN.
- B. Omit electrolytes and send the bag to avoid missing the delivery window.
- C. Hold preparation or release until the electrolyte section is clarified, document the incomplete order, and communicate promptly with the prescriber’s office.
- D. Ask the patient to confirm the usual electrolytes from memory and proceed.
Answer key
1.1.1.8 1. Answer: B
A: Tempting because nutrition support delay feels harmful and rate reduction sounds like a compromise. Incorrect because the single discriminating clue is the loss of central access; reducing rate does not solve a route/access mismatch. Core pharmacist practice and nutrition support safety standards favor holding and clarifying rather than infusing a central-type PN through inappropriate access. Sources: ASPEN PN practice guidance; ASHP nutrition support references.
B: Correct because the pharmacist stays within scope, recognizes the access conflict, prevents unsafe administration, documents the issue, and communicates with the prescriber. The PK/PD angle is not about drug metabolism here; it is about route suitability and safe delivery of a high-risk formulation. This is the guideline-consistent pharmacist action. Sources: ASPEN; ASHP.
C: Tempting because pharmacists understand formulation adjustments and peripheral PN limits. Incorrect because the single clue is that the stem does not grant independent prescribing authority. Rewriting the regimen is not the pharmacist’s autonomous next step here. Sources: ASHP; professional practice standards.
D: Tempting because nurses are critical administration partners. Incorrect because the pharmacist cannot defer the verification decision to nursing; access-route verification is part of pharmacist safety judgment before release. Sources: ASPEN; ASHP.
1.1.1.9 2. Answer: A
A: Correct because the discrepancy is a pharmacist-correctable release error, not a new therapeutic decision. The single clue is that the current verified order already clearly states the intended 14-hour duration. Correcting the label, re-verifying, documenting, and then releasing aligns with workflow safety. Sources: ASHP compounding and labeling references.
B: Tempting because experienced home PN patients may know their routine. Incorrect because patient familiarity does not permit pharmacy to release a mislabeled product. The label must match the verified order before release. Sources: ASHP; labeling and release standards.
C: Tempting because a mismatch can feel like an automatic hold. Incorrect because the key clue is that the order itself is already clear; this is not a new clinical ambiguity requiring a full new order, but a correctable workflow issue. Sources: ASHP.
D: Tempting because courier and home infusion staff often reinforce instructions. Incorrect because counseling or delivery communication does not replace accurate product labeling at release. Sources: ASHP professional standards.
1.1.1.10 3. Answer: B
A: Tempting because the typed order seems authoritative and discharge timing adds pressure. Incorrect because the single discriminating clue is the clinically meaningful mismatch between intended potassium salt and printed label. Release with a discrepancy is unsafe. Sources: ASPEN; ASHP.
B: Correct because it addresses both therapeutic clarity and release accuracy. Potassium salts are not interchangeable by assumption in a verification stem; the pharmacist must reconcile the formula and label before dispensing. This follows nutrition support verification standards. Sources: ASPEN; ASHP; AHFS Drug Information for electrolyte salts.
C: Tempting because acid-base reasoning can make acetate sound attractive. Incorrect because the stem is not asking what salt might be preferable in another context; it asks for the pharmacist’s next step when the order and label conflict. The single clue is the discrepancy itself. Sources: AHFS; ASPEN.
D: Tempting because both options deliver potassium. Incorrect because the accompanying anion matters clinically and operationally, and a label-formula mismatch is never minor at release. Sources: AHFS; ASHP.
1.1.1.11 4. Answer: C
A: Tempting because lower current glucose can make insulin removal look conservative. Incorrect because the single clue is the copied-forward order in a changed inpatient context; the pharmacist should clarify rather than independently altering a therapeutically significant component. Sources: ASPEN; ASHP; Lexicomp for insulin product considerations.
B: Tempting because home tolerance is reassuring. Incorrect because prior tolerance does not guarantee current appropriateness after recent insulin-management changes. Sources: ASPEN; DiPiro.
C: Correct because it identifies a clinically relevant mismatch between historical formulation and current condition, then uses the proper pharmacist action: hold verification, clarify, document, proceed after resolution. Sources: ASPEN; ASHP.
D: Tempting because it offers a workaround using another glucose-management strategy. Incorrect because it does not solve the immediate order-verification issue and improperly shifts decision-making without clarifying the PN order. Sources: Lexicomp; ASPEN.
1.1.1.12 5. Answer: B
A: Tempting because the product is already prepared and delay feels harmful. Incorrect because the single clue is incomplete compounding record plus omitted label element; release safeguards are not optional after compounding. Sources: USP-aligned sterile compounding principles; ASHP.
B: Correct because the pharmacist’s role includes preventing release of a product that fails documentation or labeling requirements. The operational safety chain is incomplete, so release must wait pending reconciliation. Sources: ASHP; USP-informed practice standards.
C: Tempting because verbal reinforcement can sometimes supplement counseling. Incorrect because spoken instructions do not replace required label content and verified release documentation. Sources: ASHP.
D: Tempting because nursing is involved in administration. Incorrect because the missing verification data are pharmacy release responsibilities and cannot be completed by another discipline as a workaround. Sources: ASHP professional practice standards.
1.1.1.13 6. Answer: C
A: Tempting because pharmacists routinely assess electrolytes and the labs suggest possible adjustment. Incorrect because the phrase “adjust as needed” is too vague to serve as a specific therapeutic authorization in this stem. The single discriminating clue is lack of explicit authorized modification details. Sources: ASPEN; ASHP; AHFS electrolyte references.
B: Tempting because ambiguity may seem intentionally permissive. Incorrect because vague wording cannot replace clear order parameters when therapeutic components may change materially. Sources: ASHP professional standards.
C: Correct because the pharmacist identifies that a change may be appropriate but clarification is required before making a therapeutically meaningful modification. This is the right boundary-preserving action. Sources: ASPEN; ASHP.
D: Tempting because it avoids unauthorized adjustment. Incorrect because omitting all electrolytes is itself a major therapeutic change and does not solve the ambiguity appropriately. Sources: AHFS; ASPEN.
1.1.1.14 7. Answer: C
A: Tempting because administration staff will ultimately handle the line. Incorrect because the pharmacist must verify route/access suitability before release; the single clue is conflicting access documentation that directly affects safety. Sources: ASPEN; ASHP.
B: Tempting because the formula looks like central PN and that may be the intended plan. Incorrect because intent cannot substitute for confirmed current access. Sources: ASPEN.
C: Correct because it prevents unsafe assumption, targets the exact unresolved variable, and uses appropriate communication and documentation. This is the board-style safest next step. Sources: ASPEN; ASHP.
D: Tempting because it avoids delay by changing the route strategy. Incorrect because converting to peripheral PN is a therapeutic reformulation choice not authorized in the stem, and the actual access status is still unconfirmed. Sources: ASHP; professional role standards.
1.1.1.15 8. Answer: C
A: Tempting because home PN often continues prior formulas and continuity is common. Incorrect because the single clue is that the current signed order is unreadable in the electrolyte section; last month’s formula may not reflect current needs. Sources: ASPEN; ASHP.
B: Tempting because sending something may seem better than delaying. Incorrect because omitting electrolytes creates a major unauthorized therapeutic change. Sources: AHFS; ASPEN.
C: Correct because the order is incomplete in a way that changes formulation safety and therapeutic content. Holding preparation or release, documenting, and clarifying with the office is the appropriate pharmacist action. Sources: ASHP; ASPEN.
D: Tempting because patients on long-term home PN may know their regimen. Incorrect because patient memory cannot substitute for a complete, verified current order when electrolytes are missing or unreadable. Sources: ASHP professional standards.
Keep going with the full BCNSP Prep Course (BCNSP)
You just studied the way members do, in the same lesson interface. Full access unlocks every lesson, the question bank and flashcards for a full year.
One payment · 1 year of access · No auto-renewal