1.1.1 - Age-Related PK Changes
Why it matters Many board questions hide the real issue inside a standard adult…
- 1 Why it matters Many board questions hide the real issue inside a standard adult… 2:04
- 2 Key Terms & Must-Know Facts Key terms Bioavailability: Fraction of administered… 4:33
- 3 The exam tests whether you can separate aging effect from acute illness effect… 0:57
- 4 Core content 1.1.1.1 Foundational PK framework: what changes, what does not A. 3:36
- 5 Body 3:02
- 6 Serum creatinine is 0.8 mg/dL, BP 126/68 mm Hg, and there is a note that she so… 4:02
- 7 Marked loss of oral absorption for most medications Reduced renal clearance des… 4:34
- 8 The single rule that resolves it is body composition: older adults generally ha… 3:39
- 9 Body composition shift and drug distributionExam takeaway: Less total body wate… 4:40
- 10 Verify: this patient also needs renal assessment and careful serum-level strate… 4:04
- 11 SAY: “The standard dose may not distribute the same way in this patient.” MONIT… 3:26
- 12 Body 3:27
- 13 4 Recommend safely Start lower, choose safer alternatives, and monitor sedation… 4:18
- 14 Lorazepam is not associated with falls in older adults Lorazepam has no hepatic… 4:03
- 15 Older adults often have reduced muscle mass, so serum creatinine can look norma… 3:49
- 16 Body 3:32
- 17 The pharmacist performing discharge reconciliation is asked what requires immed… 3:27
- 18 Assume renal function is normal because serum creatinine is below 1 mg/dL Estim… 4:21
- 19 HOLD/CLARIFY/ESCALATE: clarify standard doses of DOACs, digoxin, gabapentin/pre… 3:51
- 20 Body 3:42
- 21 4 Monitor with intent Track a parameter linked to the expected harm: sedation,… 4:05
- 22 Increase the loading dose to overcome age-related absorption changes Lower the… 3:03
- 23 Exam Traps & Differentiators Common traps & distractors: The most common wrong… 2:22
- 24 Stem clue Think Reject Frail older adult, low weight, SCr 0.7–0.9 mg/dL, renall… 5:00
- 25 If the stem says “why prefer lorazepam to diazepam” → think relative preservati… 1:40
- 26 Tables PK domain Typical age-related change Drug consequence Pharmacist respons… 4:34
- 27 certain cardiovascular agents First few doses cause unexpectedly high serum exp… 6:07
- 28 Algorithm / Approach Concept flow: Practical pharmacist approach to age-related… 2:09
- 29 Rapid Review Absorption in aging → usually weaker exam answer than renal cleara… 3:15
- 30 Self-check quiz 1. 4:39
- 31 Continue gabapentin at the same dose because serum creatinine is normal Recomme… 5:07
- 32 An 87-year-old man in assisted living with atrial fibrillation, CKD, diabetes,… 5:08
- 33 Gabapentin accumulation from reduced renal clearance plus diazepam prolongation… 1:30
- 34 Answer key 1. 2:09
- 35 Correct answer: B — Cockcroft-Gault or the drug-specific dosing estimate should… 2:58
- 36 It is incorrect because 44 kg frailty and CKD make hidden renal impairment like… 2:20
- 37 B: Tempting because it fits the body-composition model, and it is correct becau… 3:24
- 38 D: Tempting because diazepam is familiar and a lower dose may look reasonable. 2:45
- 39 It is incorrect because not every agent has a straightforward substitute and th… 2:53
- 40 If you missed this: Review 1.1.1.3 Hepatic metabolism: reduced blood flow, redu… 2:50
- 41 If you missed this: Review 1.1.1.5 Integration: translating PK changes into saf… 1:26
Why it matters
- Many board questions hide the real issue inside a standard adult regimen that becomes unsafe because the older adult clears or distributes the drug differently.
- Age-related PK changes often interact with frailty, low body weight, dehydration, heart failure, and polypharmacy, making toxicity more likely even before symptoms are obvious.
- The safest pharmacist recommendation is often not “stop the drug,” but “clarify the renal estimate, lower the dose, extend the interval, and monitor the right parameter.”
- PK and PD are tested together: this lesson gives the concentration side; the next lesson adds tissue sensitivity and homeostatic vulnerability.
Key Terms & Must-Know Facts
1.1.1.1 Key terms
- Bioavailability: Fraction of administered dose reaching systemic circulation.
- First-pass metabolism: Presystemic hepatic or gut metabolism before systemic entry.
- Volume of distribution (Vd): Apparent extent of drug distribution outside plasma.
- Clearance (CL): Volume of plasma cleared of drug per unit time.
- Half-life: Time for concentration to fall by 50%; depends on both Vd and CL.
- Lipophilic drug: Drug distributing more into fat tissue.
- Hydrophilic drug: Drug staying more in plasma/extracellular water.
- Phase I metabolism: Oxidation, reduction, hydrolysis; often CYP-mediated.
- Phase II metabolism: Conjugation such as glucuronidation.
- Creatinine clearance (CrCl): Estimate used traditionally for drug dosing.
- Serum creatinine trap: “Normal” creatinine can mask reduced kidney function in low-muscle-mass older adults.
- Loading dose: Dose based mainly on Vd.
- Maintenance dose: Dose based mainly on clearance.
1.1.1.2 Must-know facts
- Absorption changes with aging are usually less clinically important than distribution, metabolism, and excretion changes.
- Older adults generally have less total body water and more body fat.
- Lipophilic drugs often have longer half-lives in older adults.
- Hydrophilic drugs may reach higher peak concentrations at standard doses.
- Hepatic blood flow and liver mass tend to decrease with age.
- Phase I metabolism is more affected by aging than Phase II metabolism.
- Renal elimination declines with age even when serum creatinine appears normal.
- For many drugs, CrCl using Cockcroft-Gault remains the dosing standard because drug studies and labeling are commonly tied to it.
- A longer half-life does not always mean the loading dose should change; it often means the maintenance strategy should change.
- The exam tests whether you can separate aging effect from acute illness effect such as dehydration or AKI.
Core content
1.1.1.3 Foundational PK framework: what changes, what does not
A Explanation
The first exam decision conflict is this: when an older adult has a medication problem, should you blame absorption, or should you focus on distribution, metabolism, and excretion? The correct choice is usually to reject absorption as the main culprit unless the stem gives a specific reason such as achlorhydria affecting a pH-dependent drug, enteral feed interaction, constipation/ileus, malabsorption, or administration error. Aging alone produces variable absorption changes, but the biggest clinically actionable shifts are usually reduced renal clearance, altered body composition, and reduced hepatic blood flow.
WHY THIS IS TESTED: exam stems often include many age-related physiologic facts, but only one explains why a usual dose becomes unsafe. The tested pattern is choosing the PK domain that actually changes the concentration-time curve in a meaningful way.
Use a simple hierarchy. First ask: does the drug depend on kidney clearance? If yes, renal change often dominates. If not, ask whether the drug is lipophilic or hydrophilic, then whether hepatic oxidative metabolism is important. Maintenance dosing tracks clearance; loading dose tracks distribution. So if the issue is a higher peak with an aminoglycoside, think reduced total body water and altered Vd. If the issue is prolonged sedation with diazepam, think increased fat stores and longer half-life. If the issue is accumulation of digoxin or gabapentin, think reduced renal elimination.
Key rule: In older adults, the highest-yield PK defaults are: absorption usually modestly changed, distribution predictably changed, hepatic Phase I often reduced, and renal elimination commonly reduced.
Recall: In the upcoming topic Age-Related PD Changes, we will add the second layer: even when concentration changes are small, tissue sensitivity to sedatives, anticoagulants, and anticholinergics may still be increased.
Exam takeaway: Start with renal clearance, then body composition, then hepatic metabolism because those changes usually explain standard-dose toxicity in older adults.
flowchart TD
A[Older adult with possible drug toxicity] --> B{Which PK domain best explains it?}
B --> C[Renal elimination reduced]
B --> D[Distribution altered by less water and more fat]
B --> E[Hepatic Phase I metabolism reduced]
B --> F[Absorption change only if stem gives specific clue]
C --> G[Lower dose or extend interval]
D --> H[Hydrophilic higher peak or lipophilic prolonged effect]
E --> I[Watch high extraction and oxidized drugs]
F --> J[Check administration, pH, feeds, GI disease] B Worked example
An 84-year-old woman in assisted living is reviewed after increased morning confusion. Her medications include diazepam 5 mg by mouth nightly, metoprolol succinate 50 mg daily, calcium carbonate 500 mg three times daily, and omeprazole 20 mg daily. She has osteoarthritis and chronic constipation. Serum creatinine is 0.8 mg/dL, BP 126/68 mm Hg, and there is a note that she sometimes takes her medications with yogurt. The team asks which age-related PK change best explains the prolonged sedation.
Identify task: choose the most likely PK change producing toxicity. Extract key facts: lipophilic benzodiazepine, nightly dosing, morning carryover, no clear renal injury signal, distracting clue is calcium/omeprazole/yogurt suggesting absorption interactions. Apply rule: diazepam is highly lipophilic; increased body fat increases Vd and prolongs half-life. Eliminate distractors: reduced gastric acidity can alter absorption of some drugs, but not the best explanation for next-day sedation with diazepam. “Normal” serum creatinine is irrelevant here because diazepam toxicity is not mainly from renal accumulation. Verify: safest pharmacist recommendation is to flag the long-acting benzodiazepine and suggest taper/alternative rather than focusing on food administration.
C Exam trap
Common wrong answer: reduced absorption due to increased gastric pH.
Why it is tempting: stems often include proton pump inhibitors, calcium products, or food timing, making learners chase a familiar drug-absorption interaction.
Single clue that eliminates it: the problem is prolonged effect from a lipophilic sedative, which points to increased fat distribution and longer half-life, not failed absorption.
D Checkpoint
Question: Which age-related PK change most often explains why standard adult maintenance doses become unsafe in older adults?
- Marked loss of oral absorption for most medications
- Reduced renal clearance despite apparently normal serum creatinine
- Universal increase in Phase II hepatic conjugation
- Consistent increase in first-pass metabolism for all high-extraction drugs
Answer: B
- A: Tempting because GI physiology changes with age, but most drugs are still adequately absorbed; absorption alone is not the main high-yield explanation.
- B: Correct because age-related decline in kidney function is common and clinically important for maintenance dosing and toxicity prevention.
- C: Tempting if you remember Phase II is often preserved, but it is not universally increased.
- D: Tempting if you associate aging with liver changes, but first-pass metabolism does not consistently increase; if anything, reduced blood flow may increase bioavailability for some high-extraction drugs.
Pharmacist Action: NOTICE: standard adult doses of renally cleared, sedating, or narrow-therapeutic-index drugs in very old adults. SAY: “This regimen may be safe in younger adults but may accumulate differently here.” MONITOR: adverse effects, renal function, and timing of symptoms after dose changes; frequency depends on drug and instability. HOLD/CLARIFY/ESCALATE: clarify when toxicity appears after a new start, dose increase, dehydration, or transition of care.
1.1.1.4 Distribution changes: less water, more fat, different peaks and half-lives
A Explanation
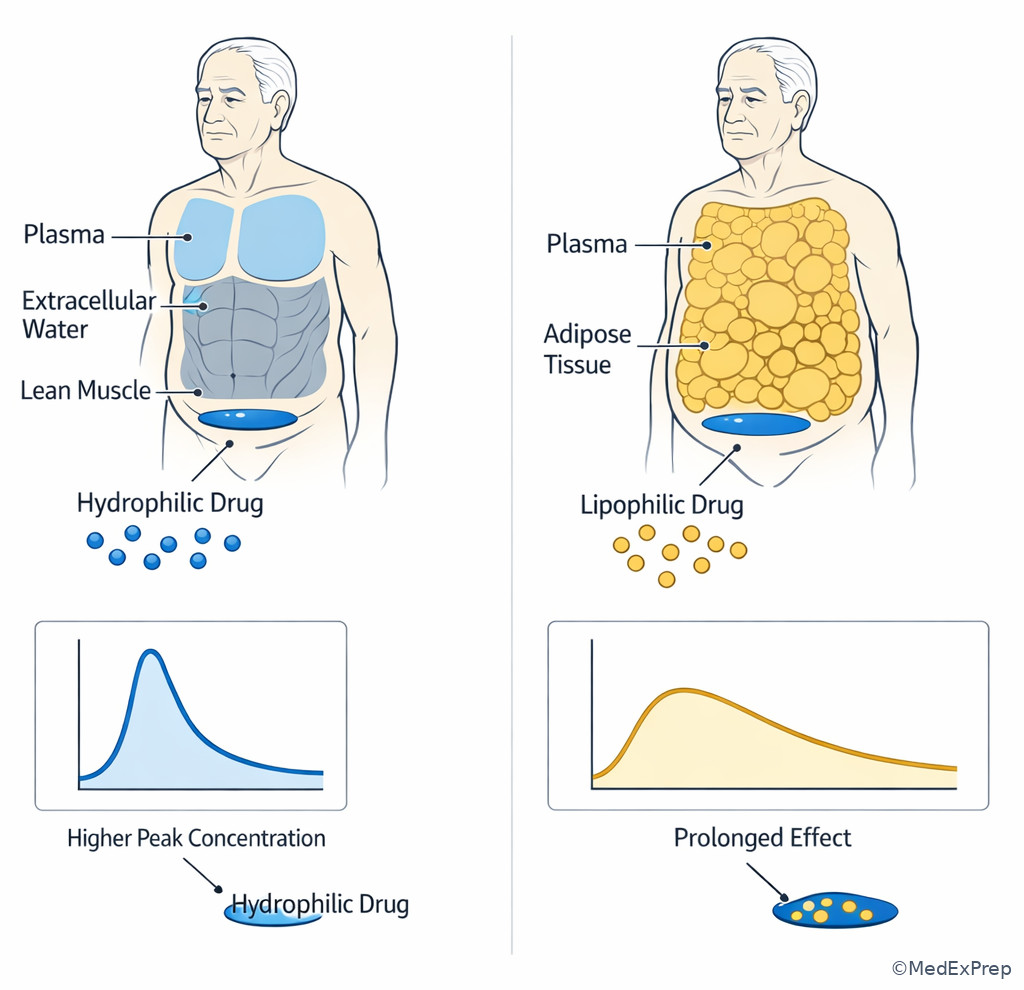
The decision conflict here is whether to adjust because a drug is hydrophilic or because it is lipophilic. The single rule that resolves it is body composition: older adults generally have reduced total body water and lean body mass plus increased body fat percentage. Hydrophilic drugs have a smaller Vd, so a standard dose can yield a higher plasma concentration. Lipophilic drugs have a larger Vd, so they redistribute into fat and may have a longer terminal half-life with prolonged effects.
WHY THIS IS TESTED: board stems often ask why one older adult gets a higher peak concentration while another gets prolonged sedation. The tested pattern is matching drug physicochemical behavior to age-related body composition.
High-yield examples: aminoglycosides, ethanol, and lithium are relatively hydrophilic; diazepam is classically lipophilic. Digoxin also deserves special care because reduced lean body mass can reduce Vd, increasing serum concentration sensitivity, though kidney function is also crucial. This means loading doses and initial dose selection may change for hydrophilic drugs, while interval or maintenance strategy often changes for lipophilic drugs with long half-lives. The exam may also combine low body weight or cachexia with aging, which strengthens the hydrophilic concentration effect further.
Do not overgeneralize: not every lipophilic drug must be avoided, and not every hydrophilic drug needs a lower dose. The question is whether the observed toxicity pattern fits a Vd problem. Fast toxicity after a standard loading dose suggests smaller Vd for a water-soluble drug. Slow accumulation with persistent sedation suggests larger fat distribution and delayed elimination.
Memory anchor: Water shrinks, Fat spreads. Hydrophilic drugs hit harder; lipophilic drugs last longer.
Exam takeaway: Less total body water raises concentrations of hydrophilic drugs, while more body fat prolongs effects of lipophilic drugs.
B Worked example
A 79-year-old man in a skilled nursing facility receives gentamicin 5 mg/kg IV as part of a facility protocol pending prescriber review for gram-negative bacteremia. He has frailty, heart failure, and chronic kidney disease; weight is 54 kg. He also takes furosemide 40 mg daily and sertraline 50 mg daily. The nurse notes dizziness after the first dose. Serum creatinine is 1.0 mg/dL, which is close to his baseline. The pharmacist is asked which age-related PK principle should guide the immediate dosing review.
Identify task: choose the governing PK change. Extract key facts: hydrophilic drug, low body weight, frailty, older adult, possible higher concentration after initial dose. Ototoxic loop diuretic is a distracting but relevant risk amplifier, not the core PK principle. Apply rule: reduced total body water and lean mass can shrink Vd for hydrophilic drugs, increasing peak concentration. Eliminate distractors: increased body fat explains lipophilic drug prolongation, not aminoglycoside early peak concerns. Reduced gastric acidity is irrelevant because the drug is IV. Verify: this patient also needs renal assessment and careful serum-level strategy, but the first-dose concentration problem is distribution-based.
C Exam trap
Common wrong answer: increased body fat causing gentamicin accumulation.
Why it is tempting: learners memorize “older adults have more fat” and overapply it to every medication.
Single clue that eliminates it: gentamicin is a hydrophilic IV drug; the more relevant issue is smaller water compartment and higher concentration, not fat sequestration.
D Checkpoint
Question: Which drug is most likely to have a prolonged half-life in an older adult primarily because of increased body fat?
- Diazepam
- Gentamicin
- Lithium
- Atenolol
Answer: A
- A: Correct because diazepam is lipophilic and distributes into fat, prolonging its effect.
- B: Tempting because gentamicin toxicity is common in older adults, but its major issue is hydrophilic distribution and renal clearance, not fat-related prolongation.
- C: Tempting because lithium is narrow therapeutic index, but it is not the classic fat-distribution example.
- D: Tempting because atenolol can accumulate in kidney impairment, but prolonged half-life from increased body fat is not the main mechanism.
- The smaller compartment in many older adults is total body water.
- True or False: Increased body fat usually shortens diazepam half-life. False.
- Name the pattern: hydrophilic drug + standard dose + frail low-weight older adult = higher concentration.
Pharmacist Action: NOTICE: low body weight, frailty, cachexia, and hydrophilic or highly lipophilic drugs. SAY: “The standard dose may not distribute the same way in this patient.” MONITOR: peak-related toxicity for hydrophilic agents and prolonged sedation or delayed toxicity for lipophilic agents; follow drug-specific levels if indicated. HOLD/CLARIFY/ESCALATE: clarify loading dose choices when the patient is frail, underweight, or develops toxicity after the first few doses.
1.1.1.5 Hepatic metabolism: reduced blood flow, reduced Phase I, preserved Phase II
A Explanation
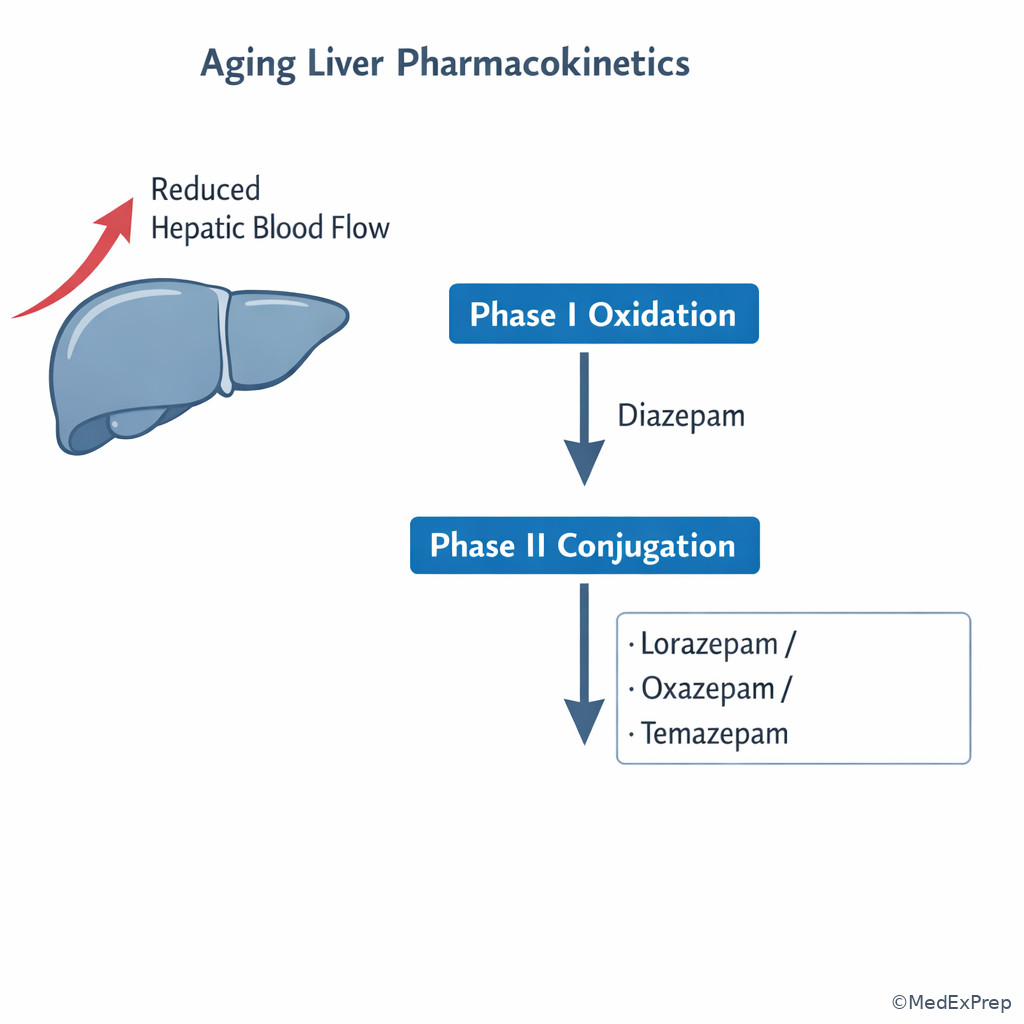
The exam conflict here is whether aging reduces all hepatic metabolism equally. Reject that oversimplification. The single rule is that hepatic blood flow and liver mass tend to decline with age, and Phase I oxidative metabolism is more affected than Phase II conjugation. This matters most for drugs with significant first-pass extraction or reliance on oxidative clearance. As a result, some drugs may have increased bioavailability or reduced clearance, especially when hepatic extraction and blood flow are important.
WHY THIS IS TESTED: the stem may ask why an older adult has greater effect from an oral dose or why a sedative lasts longer even without kidney failure. The testable pattern is choosing reduced Phase I metabolism or reduced hepatic blood flow rather than assuming global liver failure.
Examples matter. Diazepam is a classic Phase I example and can have prolonged effects. Lorazepam, oxazepam, and temazepam are often favored when a benzodiazepine is unavoidable because they rely more on conjugation. This does not make them harmless in older adults; it just explains why some short-acting conjugated agents are pharmacokinetically preferable to long-acting oxidized ones. Similarly, high-extraction drugs may show higher oral bioavailability if first-pass extraction falls. On the exam, you are not expected to turn every liver-metabolized drug into a memorization list. You are expected to recognize the pattern: Phase I is more vulnerable than Phase II.
Key rule: “LOT” benzodiazepines (lorazepam, oxazepam, temazepam) are remembered as conjugation-favored options; the PK reason is relative preservation of Phase II metabolism compared with Phase I oxidation.
High-Yield Connection: This concept is tested alongside Age-Related PD Changes. Know both the PK reason some benzodiazepines last longer and the PD reason all benzodiazepines still raise delirium and falls risk in older adults.
Exam takeaway: Prefer the pattern “Phase I down more than Phase II” when the stem asks why a hepatically cleared drug has prolonged effects in an older adult.
flowchart LR
A[Aging liver changes] --> B[Reduced liver mass]
A --> C[Reduced hepatic blood flow]
A --> D[Phase I oxidation reduced more]
A --> E[Phase II conjugation relatively preserved]
D --> F[Longer effect for oxidized drugs]
C --> G[Higher bioavailability for some high-extraction drugs]
E --> H[Conjugated options may be PK-preferred]
Exam takeaway: Reduced hepatic blood flow and reduced oxidative metabolism explain why some orally administered drugs have greater exposure in older adults.
B Worked example
An 81-year-old woman in primary care is taking diazepam 2 mg by mouth twice daily as needed for muscle spasm after a hospitalization. Comorbidities include osteoporosis, chronic insomnia, and mild heart failure. She reports daytime grogginess and one near-fall. Serum creatinine is 0.7 mg/dL, AST/ALT are normal, and she asks whether “her liver tests being normal” means the dose is fine. A tempting clue is that she also takes omeprazole, which may suggest an interaction-focused answer.
Identify task: determine the age-related PK principle behind prolonged effect. Extract key facts: oxidatively metabolized long-acting benzodiazepine, older adult, grogginess and near-fall, normal transaminases. Apply rule: age-related hepatic blood flow reduction and reduced Phase I metabolism can prolong diazepam effect even when routine liver tests are normal. Eliminate distractors: a normal AST/ALT does not rule out reduced functional clearance with aging. Omeprazole may interact with some agents, but the core tested principle is physiologic aging of hepatic metabolism. Verify: recommend deprescribing discussion or alternative therapy with safer risk profile, not reassurance based on liver tests.
C Exam trap
Common wrong answer: normal liver enzymes mean hepatic handling is preserved.
Why it is tempting: learners confuse injury markers with functional drug-metabolism capacity.
Single clue that eliminates it: the stem tests age-related clearance and blood flow, not hepatocellular damage.
D Checkpoint
Question: Which statement best supports selecting lorazepam over diazepam when a benzodiazepine cannot be avoided in an older adult?
- Lorazepam is not associated with falls in older adults
- Lorazepam has no hepatic metabolism
- Lorazepam relies more on conjugation, which is relatively preserved with aging
- Diazepam is safer because its lipophilicity prevents accumulation
Answer: C
- A: Tempting because lorazepam is often viewed as safer, but all benzodiazepines still increase fall and cognitive risk.
- B: Tempting because “LOT” is a famous memory aid, but lorazepam is hepatically handled; it is not free of hepatic metabolism.
- C: Correct because conjugation is relatively preserved compared with oxidative metabolism in aging.
- D: Tempting if you misremember lipophilicity as protective, but lipophilicity contributes to diazepam’s prolonged half-life in older adults.
Pharmacist Action: NOTICE: long-acting oxidatively metabolized sedatives and high-extraction oral drugs. SAY: “Normal liver enzymes do not guarantee normal drug clearance in an older adult.” MONITOR: sedation, falls, confusion, and cumulative adverse effects after starts or dose changes. HOLD/CLARIFY/ESCALATE: escalate when persistent sedation, recurrent falls, or poor functional recovery occurs after adding a long-acting hepatically cleared drug.
1.1.1.6 Renal elimination: the serum creatinine trap and dosing decisions
A Explanation
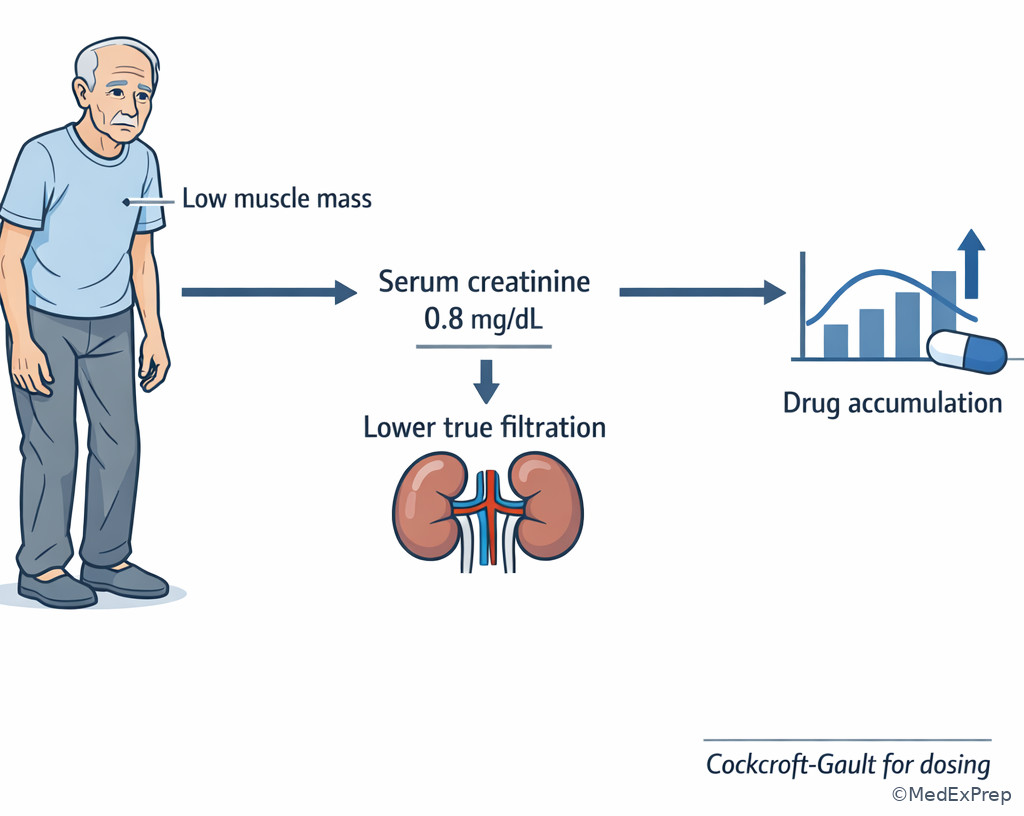
This is the highest-yield section for the BCGP exam. The decision conflict is whether a “normal” serum creatinine means kidney function is adequate for dosing. The single rule that resolves it is that serum creatinine reflects both filtration and muscle mass. Older adults often have reduced muscle mass, so serum creatinine can look normal even when true filtration is reduced. For medication dosing, the exam usually expects you to think in terms of estimated creatinine clearance using Cockcroft-Gault, because many drug labels and studies use it.
WHY THIS IS TESTED: many wrong answers occur because learners equate SCr 0.8 mg/dL with “normal kidneys.” The testable pattern is recognizing hidden renal impairment in a small, frail, older adult.
Key consequence: maintenance dosing of renally cleared drugs may need a lower dose, longer interval, or both. High-yield examples include digoxin, DOACs, gabapentin, pregabalin, metformin, aminoglycosides, and many antimicrobials. Also distinguish chronic age-related decline from acute kidney injury. Aging lowers reserve; dehydration, diuretics, infection, ACE inhibitors, NSAIDs, or contrast can push the patient into a more dangerous range quickly. The exam may ask what requires immediate clarification: it is often a newly started renally cleared drug at a standard dose in a frail older adult with low body weight and “normal” SCr.
Do not automatically round low serum creatinine values upward without a specific local protocol; that practice can misestimate function and is not universally recommended. Use an evidence-based approach and the dosing method tied to the drug reference or label.
Common pitfall: eGFR reported by the lab may be useful clinically, but when the question asks about drug dosing, default to the dosing standard used by the reference for that medication, commonly Cockcroft-Gault CrCl.
High-Yield Connection: This concept overlaps strongly with the later topic Cockcroft-Gault And Renal Dosing. Here you learn the aging principle; later you will execute the calculation and compare dose-adjustment cutoffs in board-style stems.
Exam takeaway: In a frail older adult, a normal serum creatinine does not rule out the need for renal dose adjustment.
flowchart TD
A[Older adult on renally cleared drug] --> B[Check age, weight, baseline SCr, hydration]
B --> C{Is SCr deceptively normal?}
C --> D[Yes: low muscle mass may mask reduced function]
C --> E[No: still estimate dosing function]
D --> F[Use Cockcroft-Gault or drug-specific dosing standard]
E --> F
F --> G{Drug has renal cutoff?}
G --> H[Adjust dose or interval]
G --> I[Monitor and reassess if no adjustment needed] Exam takeaway: Low muscle mass can make serum creatinine appear reassuring even when drug-clearing kidney function is reduced.
B Worked example
An 88-year-old woman is discharged from the hospital to home with apixaban 5 mg by mouth twice daily for atrial fibrillation, gabapentin 300 mg by mouth three times daily for neuropathy, and lisinopril 10 mg daily. She weighs 47 kg, has hypertension and mild cognitive impairment, and uses a walker. Serum creatinine today is 0.8 mg/dL; last week she had poor oral intake after influenza. The pharmacist performing discharge reconciliation is asked what requires immediate clarification.
Identify task: prioritize the PK risk needing pharmacist action. Extract key facts: very old age, low body weight, frailty signal, renally relevant medications, apparently normal SCr, recent dehydration as distracting acute factor. Apply rule: SCr may overestimate kidney function; renally relevant regimens require dose review using the appropriate dosing standard. Eliminate distractors: lisinopril may need monitoring, but the most urgent clarification is whether apixaban and gabapentin doses fit current renal function and patient-specific criteria. Verify: recommend CrCl-based dose review, confirm weight and age criteria, reassess renal function after discharge, and monitor bleeding/sedation.
C Exam trap
Common wrong answer: keep the regimen because serum creatinine is normal.
Why it is tempting: the number looks reassuring and exam takers may anchor on the laboratory reference range.
Single clue that eliminates it: 88 years old and 47 kg strongly suggest low muscle mass, so the creatinine may not reflect true drug-clearing function.
D Checkpoint
Question: A frail 86-year-old woman weighing 45 kg has serum creatinine 0.7 mg/dL and is prescribed a standard dose of a renally eliminated medication. What is the most appropriate pharmacist recommendation?
- Assume renal function is normal because serum creatinine is below 1 mg/dL
- Estimate CrCl using the dosing-standard method and assess whether dose or interval adjustment is needed
- Ignore kidney function and reduce the dose only because of age
- Increase the dose because low serum creatinine suggests augmented clearance
Answer: B
- A: Tempting because reference ranges can falsely reassure, but low muscle mass can mask renal impairment.
- B: Correct because dosing should be tied to an appropriate estimate of renal function, commonly Cockcroft-Gault for drug dosing.
- C: Tempting because “start low” is common in geriatrics, but dosing should be individualized rather than reduced solely by chronological age.
- D: Tempting only if one misunderstands the creatinine trap; low SCr in frailty does not imply augmented clearance.
- The dosing equation most often expected on older board-style renal dosing items is Cockcroft-Gault CrCl.
- True or False: A serum creatinine of 0.8 mg/dL always excludes significant renal dose adjustment. False.
- The most dangerous assumption in a frail older adult is that a normal creatinine equals normal clearance.
Pharmacist Action: NOTICE: frailty, low body weight, dehydration, heart failure, and renally cleared drugs. SAY: “This creatinine may look normal, but the dosing estimate may still be low.” MONITOR: renal function trend, efficacy endpoints, and concentration-linked toxicities; recheck after acute illness or regimen changes. HOLD/CLARIFY/ESCALATE: clarify standard doses of DOACs, digoxin, gabapentin/pregabalin, antimicrobials, and other renally cleared agents at transitions of care.
1.1.1.7 Integration: translating PK changes into safer geriatric medication decisions
A Explanation
The final conflict is practical: when a board stem shows possible PK risk, should you recommend a lower dose, a longer interval, an alternative medication, or more monitoring? The single rule is to match the intervention to the PK problem. If the drug has a smaller Vd in aging and the issue is high peak concentration, consider a lower initial or loading dose. If the issue is reduced clearance and longer half-life, adjust the maintenance dose, extend the interval, or both. If the problem is persistent toxicity from a long-acting or high-risk drug, selecting an alternative may be safer than “micro-adjusting” the same agent.
WHY THIS IS TESTED: the exam is not satisfied with recognizing the PK change; it asks whether you can make a pharmacist-level recommendation that is safe, specific, and within scope.
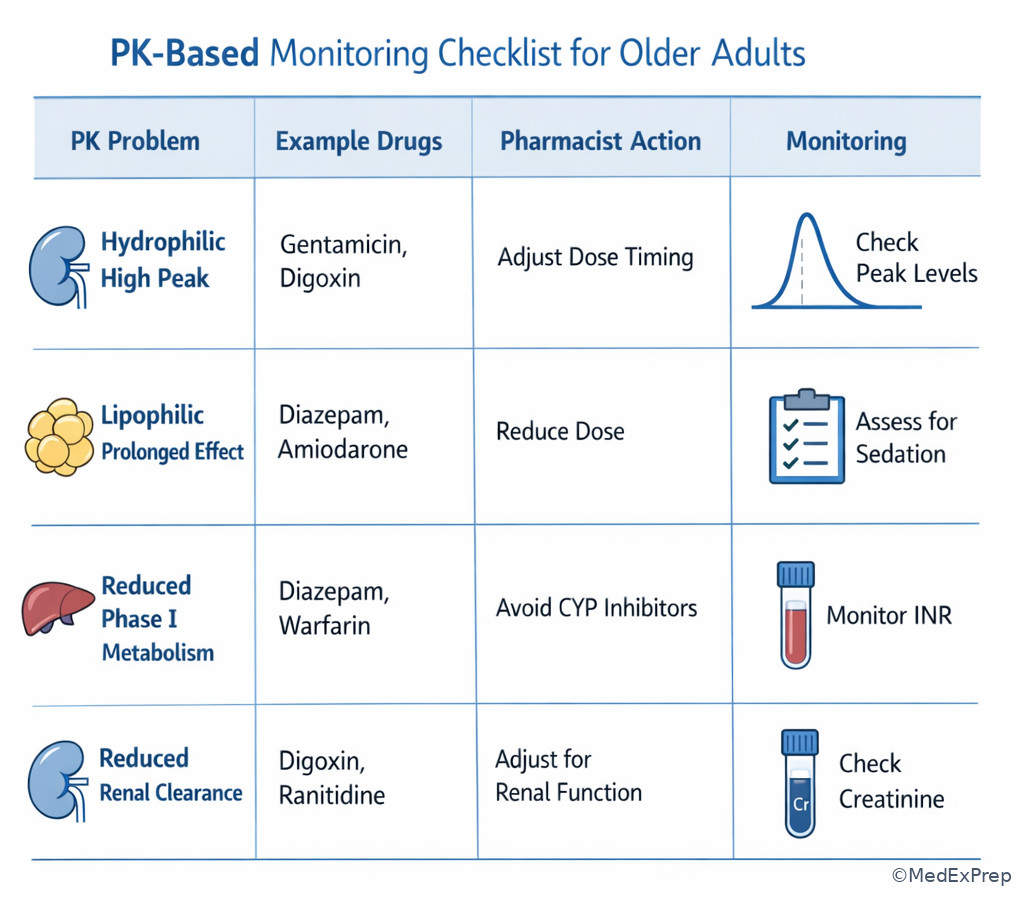
Use a structured approach. First, identify whether the harm is concentration-related, duration-related, or interaction-amplified. Second, assess whether the drug is high value, replaceable, or inappropriate for geriatric use. Third, choose the narrowest effective intervention: adjust dose, adjust interval, slow titration, recommend a safer alternative, or deprescribe. Fourth, define monitoring tied to the expected toxicity. For example, with gabapentin accumulation, monitor sedation, dizziness, gait instability, and renal trend. With digoxin, monitor symptoms, heart rate, renal function, and if appropriate levels. With long-acting benzodiazepines, monitor confusion, falls, and withdrawal risk if tapering.
Memory anchor: \(PK = Peak\), Keep, Kidney. Peak problem → think Vd/initial dose. Keep lingering too long → think half-life/maintenance. Kidney drug → check CrCl before trusting the dose.
Recall: In the upcoming topic Pathophysiology In Older Adults, symptoms may be atypical and overlap with drug effects. Here, we build on that by asking whether the symptom is disease progression or PK-driven accumulation.
Exam takeaway: Match the intervention to the PK problem—lower dose for high peak, extend interval for slow clearance, or switch drugs when the risk profile remains unfavorable.
flowchart TD
A[Possible PK-related adverse effect] --> B{What pattern fits best?}
B --> C[Early high concentration]
B --> D[Delayed accumulation or prolonged effect]
B --> E[Hidden renal impairment]
C --> F[Lower initial or loading dose]
D --> G[Lower maintenance dose or extend interval]
E --> H[Recalculate dosing function and adjust]
F --> I{Drug still appropriate?}
G --> I
H --> I
I --> J[If not, recommend safer alternative or deprescribing]
J --> K[Set monitoring for efficacy, toxicity, withdrawal] Exam takeaway: Tie monitoring to the predicted PK problem instead of ordering generic follow-up.
B Worked example
An 83-year-old man in long-term care has chronic neuropathic pain, stage 3b CKD, diabetes, and a recent fall. His MAR shows gabapentin 600 mg by mouth three times daily, trazodone 50 mg nightly, and hydrocodone/acetaminophen 5/325 mg every 6 hours as needed. He is more somnolent after supper but requests that pain therapy not be stopped completely. A recent sodium of 132 mEq/L is mildly low and may distract toward trazodone as the sole issue.
Identify task: recommend the safest pharmacist action. Extract key facts: renally cleared gabapentin at a potentially excessive dose for CKD, fall, somnolence, competing sedatives. Apply rule: clearance problem means maintenance dose or interval should be adjusted to renal function; if toxicity persists, deprescribe or switch strategy. Eliminate distractors: trazodone contributes to sedation, but the signature PK issue is gabapentin accumulation in reduced renal function. Simply adding monitoring without a dose recommendation is too passive. Verify: recommend renal dose reassessment, dose reduction or interval change per reference, sedation/fall monitoring, and communication with the prescriber/team.
C Exam trap
Common wrong answer: lower every medication equally because “older adults need lower doses.”
Why it is tempting: it sounds geriatric-friendly and cautious.
Single clue that eliminates it: safe recommendations are drug-specific and mechanism-specific; the best answer matches the adjustment to the PK driver, not age alone.
D Checkpoint
Question: Which recommendation best fits an older adult with toxicity from a renally cleared maintenance medication and hidden renal impairment?
- Increase the loading dose to overcome age-related absorption changes
- Lower the maintenance dose or extend the interval based on the drug’s renal dosing guidance
- Keep the current dose and monitor only because serum creatinine is normal
- Switch automatically to another drug in the same class at an equivalent standard dose without reassessing renal handling
Answer: B
- A: Tempting if one wrongly assumes poor absorption drives most geriatric toxicity, but the issue is impaired clearance.
- B: Correct because maintenance dosing must match reduced renal elimination.
- C: Tempting because “monitoring” feels safe, but it ignores the need for an active dosing correction.
- D: Tempting if the class is familiar, but an equivalent standard dose may recreate the same PK problem.
Pharmacist Action: NOTICE: whether the problem is peak-related, duration-related, or kidney-related. SAY: “The dose strategy should match the pharmacokinetic reason for harm.” MONITOR: one efficacy endpoint and one toxicity endpoint after every recommendation. HOLD/CLARIFY/ESCALATE: escalate persistent toxicity, recurrent falls, delirium, or any regimen where the drug remains inappropriate even after adjustment.
Exam Traps & Differentiators
Common traps & distractors: The most common wrong answer is to overfocus on absorption changes. That is tempting because GI changes are easy to remember and many stems include food, antacids, or PPIs. The better discriminator is the toxicity pattern: higher peak with hydrophilic drugs, prolonged effect with lipophilic drugs, prolonged exposure with reduced Phase I metabolism, and accumulation with reduced renal clearance.
See Fig 1 for the triage map that helps you sort these mechanisms quickly. See Fig 4 and Fig 5 when the stem is trying to lure you into trusting a normal serum creatinine. See Fig 2 and Fig 3 when you need to separate distribution from hepatic metabolism. For the action step after identifying the PK problem, See Fig 6.
| Stem clue | Think | Reject |
|---|---|---|
| Frail older adult, low weight, SCr 0.7–0.9 mg/dL, renally cleared drug | Hidden renal impairment; estimate CrCl for dosing | “Renal function is normal because creatinine is normal” |
| Long-acting benzodiazepine with daytime sedation | Lipophilic distribution + reduced Phase I metabolism | General absorption problem |
| Hydrophilic IV drug causes early toxicity after standard dose | Smaller Vd due to less total body water | Increased body fat as main explanation |
| Question compares diazepam with lorazepam | Phase I reduced more than Phase II | All benzodiazepines are PK-equivalent |
| High-extraction oral drug has greater effect in aging | Reduced first-pass extraction from lower hepatic blood flow | Universal increase in metabolism |
| Looks similar | But isn't | Single discriminator |
|---|---|---|
| Age-related renal decline | Acute kidney injury | Trend, recent illness, dehydration, or nephrotoxin exposure |
| Distribution-driven high peak | Clearance-driven accumulation | Early first doses versus delayed persistence over time |
| Normal liver enzymes | Normal hepatic drug clearance | AST/ALT do not directly prove preserved metabolic capacity |
| Age-related absorption change | Administration problem | Enteral feeds, chelation, dysphagia, or formulation mismatch suggest the latter |
| PK toxicity | PD sensitivity | Concentration/dosing pattern versus exaggerated effect at usual concentration |
- If the stem says “normal serum creatinine” in a frail 85-year-old → think hidden renal impairment until proven otherwise.
- If the stem says “daytime grogginess on diazepam” → think prolonged half-life from lipophilic distribution and reduced Phase I metabolism.
- If the stem says “toxicity after first IV dose of a hydrophilic drug” → think smaller water compartment and higher concentration.
- If the stem says “why prefer lorazepam to diazepam” → think relative preservation of conjugation.
- If the stem says “what needs clarification at discharge” with a renally cleared drug → think dose verification, monitoring plan, and recent renal trend.
Tables
| PK domain | Typical age-related change | Drug consequence | Pharmacist response |
|---|---|---|---|
| Absorption | Variable; usually modest effect | Usually not the main cause of toxicity unless specific stem clue | Check formulation, food, pH, feeds, administration timing |
| Distribution: water | Decreased total body water | Higher concentrations of hydrophilic drugs | Consider lower initial dose; monitor peak-related toxicity |
| Distribution: fat | Increased body fat percentage | Longer half-life of lipophilic drugs | Avoid long-acting sedatives when possible; slow titration |
| Hepatic metabolism | Reduced liver mass and blood flow; Phase I down more than Phase II | Reduced clearance or higher bioavailability for some drugs | Favor safer alternatives; monitor cumulative CNS effects |
| Renal excretion | Declines with age; masked by low muscle mass | Accumulation of renally cleared drugs | Use dosing-standard renal estimate; adjust dose/interval |
| Comparison | Hydrophilic pattern | Lipophilic pattern | Best example |
|---|---|---|---|
| Body compartment affected | Reduced body water | Increased body fat | — |
| Main PK effect | Smaller Vd, higher concentration | Larger Vd, longer half-life | — |
| Typical exam presentation | Early toxicity after standard dose | Persistent sedation or delayed washout | — |
| Representative drugs | Gentamicin, lithium | Diazepam | See Fig 2 |
| Preferred action | Reassess initial dose and concentration risk | Avoid long-acting agents or reduce ongoing exposure | Drug-specific monitoring |
| Differential / classification issue | Most likely mechanism | Best discriminating clue | High-yield drug examples |
|---|---|---|---|
| Standard oral dose gives stronger-than-expected effect | Reduced first-pass extraction or lower clearance | High-extraction or oxidatively metabolized drug | Some sedatives, certain cardiovascular agents |
| First few doses cause unexpectedly high serum exposure | Reduced Vd for hydrophilic drug | IV or water-soluble agent, frailty/low weight | Gentamicin, lithium |
| Days to weeks of worsening somnolence | Long half-life from lipophilic distribution and/or low clearance | Persistent next-day carryover | Diazepam |
| Toxicity despite normal SCr | Overestimated renal function from low muscle mass | Advanced age, low body weight, frailty | Gabapentin, digoxin, DOACs |
| Safer benzodiazepine choice question | Phase II conjugation relatively preserved | Lorazepam/oxazepam/temazepam comparison | Lorazepam, oxazepam, temazepam |
| Drug / class | Main PK aging concern | Common exam harm | What to monitor |
|---|---|---|---|
| Diazepam | Lipophilic distribution + reduced Phase I clearance | Daytime sedation, falls, confusion | Sedation, gait, cognition |
| Gabapentin | Renal accumulation | Somnolence, dizziness, falls | Renal function, sedation, balance |
| Digoxin | Renal clearance; altered Vd sensitivity | Bradycardia, GI or CNS toxicity | HR, renal function, symptoms, level when appropriate |
| Aminoglycosides | Hydrophilic concentration + renal elimination | Nephrotoxicity, ototoxicity | Drug levels, renal trend, hearing/balance symptoms |
| DOACs | Renal cutoff sensitivity | Bleeding or under/overdosing | CrCl, weight, bleeding, adherence |
Algorithm / Approach
Rapid Review
- Absorption in aging → usually weaker exam answer than renal clearance or distribution.
- Hydrophilic drug in frailty → smaller Vd, higher concentration.
- Lipophilic sedative in aging → longer half-life, prolonged carryover.
- Diazepam vs lorazepam → Phase I sensitivity versus relative Phase II preservation.
- Normal SCr in low-muscle-mass elder → does not equal normal drug clearance.
- Maintenance dose problem → think clearance first.
- Loading dose problem → think Vd first.
- High-extraction oral drug stronger than expected → think reduced hepatic blood flow and less first-pass extraction.
- Renally cleared CNS drug plus falls → dose review beats passive observation.
- Frail low-weight older adult → do not trust reference ranges without context.
- Normal AST/ALT → does not prove normal hepatic drug metabolism.
- Early toxicity after IV hydrophilic drug → distribution clue, not absorption clue.
- Chronic sedation after long-acting benzodiazepine → distribution plus metabolism clue, not merely insomnia severity.
- Transition-of-care reconciliation → verify renal dosing before continuing hospital-start regimens.
Self-check quiz
1. A 77-year-old woman in ambulatory care takes diazepam 5 mg by mouth nightly, temazepam 15 mg nightly as needed, lorazepam 0.5 mg twice daily as needed, and oxazepam 10 mg three times daily as needed listed from prior encounters. The pharmacist is asked which agent is most likely to have a prolonged half-life in aging primarily because of increased body fat distribution. What is the most appropriate answer?
- Diazepam
- Lorazepam
- Oxazepam
- Temazepam
2. A 84-year-old man weighing 48 kg is prescribed gabapentin 300 mg by mouth three times daily, pregabalin 75 mg twice daily, levetiracetam 500 mg twice daily, and metformin 500 mg twice daily appears on his medication list. Serum creatinine is 0.8 mg/dL. Which principle most requires immediate clarification before assuming the renal dose is safe?
- Low serum creatinine proves normal renal clearance in older adults
- Cockcroft-Gault or the drug-specific dosing estimate should be reviewed because low muscle mass may mask reduced kidney function
- Renal function is irrelevant if the patient is asymptomatic
- Only eGFR matters for every medication without exception
3. A 82-year-old frail woman in long-term care with CKD and neuropathy is taking gabapentin 600 mg by mouth three times daily, acetaminophen 650 mg three times daily, and sertraline 50 mg daily. She has new dizziness and two near-falls; serum creatinine is 0.9 mg/dL, weight 44 kg, and staff report poor oral intake last week. Which is the most appropriate pharmacist recommendation?
- Continue gabapentin at the same dose because serum creatinine is normal
- Recommend renal-function-based reassessment of gabapentin with dose reduction or interval extension and monitor sedation/falls
- Increase gabapentin to 800 mg three times daily because symptoms suggest uncontrolled neuropathy
- Switch to pregabalin at an equivalent standard dose without reassessing kidney function
4. A 79-year-old man in a health system receives gentamicin 5 mg/kg IV once for suspected bacteremia under protocol. He weighs 52 kg and has frailty, heart failure, and CKD. After the first dose he develops dizziness. Which age-related PK change best explains why a standard first dose may produce a higher concentration?
- Increased body fat leading to larger Vd for a hydrophilic drug
- Reduced total body water leading to smaller Vd for a hydrophilic drug
- Increased first-pass metabolism
- Improved renal clearance from low serum creatinine
5. A 81-year-old woman with insomnia, osteoarthritis, and prior fall is taking diazepam 2 mg by mouth twice daily as needed after a recent hospitalization. She reports next-day sedation. AST and ALT are normal; serum creatinine is 0.7 mg/dL. Which explanation best supports a pharmacist recommendation to clarify ongoing diazepam use?
- Normal liver enzymes exclude age-related changes in drug handling
- Phase I metabolism and hepatic blood flow can be reduced with aging, prolonging diazepam exposure
- Older adults absorb all oral benzodiazepines poorly, so the patient is likely overusing it
- Diazepam is preferred over lorazepam because lipophilic drugs clear faster in aging
6. An 87-year-old man in assisted living with atrial fibrillation, CKD, diabetes, and recent dehydration after viral illness is discharged on apixaban 5 mg by mouth twice daily, gabapentin 300 mg three times daily, and furosemide 40 mg daily. Weight is 49 kg; serum creatinine is 1.0 mg/dL. Which pharmacist action is most appropriate at transition of care?
- Accept all doses because serum creatinine is within a common adult reference range
- Clarify renal and patient-specific dosing criteria, especially for renally sensitive agents, before assuming standard doses are appropriate
- Hold all medications until a nephrologist independently rewrites the regimen
- Recommend switching all renally cleared agents to hepatically cleared alternatives immediately
7. A 85-year-old woman with chronic anxiety, mild cognitive impairment, constipation, and two falls is taking diazepam 5 mg by mouth nightly. A prescriber asks which alternative is pharmacokinetically preferable if a benzodiazepine must temporarily continue. Which is the best recommendation?
- Clonazepam 0.5 mg nightly because it is long acting and smoother
- Lorazepam 0.5 mg nightly because conjugation is relatively preserved compared with oxidation
- Chlordiazepoxide 10 mg nightly because its metabolites are less active in aging
- Diazepam 2 mg twice daily because dividing the dose overcomes the long half-life problem
8. A 83-year-old frail man with CKD, heart failure, neuropathy, and chronic insomnia is taking gabapentin 600 mg by mouth three times daily, diazepam 2 mg nightly, and metoprolol succinate 25 mg daily. He is somnolent in the morning and unsteady after breakfast. Which pharmacist interpretation best integrates the likely age-related PK contributors?
- Gabapentin accumulation from reduced renal clearance plus diazepam prolongation from lipophilic distribution and reduced Phase I metabolism
- Gabapentin toxicity from increased first-pass metabolism plus diazepam accumulation from reduced body water
- Metoprolol accumulation explains all symptoms because beta-blockers are always the main PK driver of morning sedation
- Age-related absorption failure is the most likely shared explanation for both drugs
Answer key
1. Correct answer: A — Diazepam.
- A. Diazepam: Tempting because it is the classic long-acting benzodiazepine you are trained to flag, and that surface logic is correct here. It is correct because diazepam is highly lipophilic, distributes into increased body fat, and also relies on oxidative metabolism, producing prolonged effect in older adults; this is consistent with standard geriatric pharmacotherapy references and Beers-oriented safety teaching (Lexicomp; DiPiro; 2023 AGS Beers Criteria).
- B. Lorazepam: Tempting because it is still a benzodiazepine and still causes sedation. It is incorrect for this specific question because although lorazepam remains risky from a PD and safety standpoint, it is not the prototypical answer for prolonged half-life from increased fat distribution; the discriminating clue is the wording “primarily because of increased body fat distribution” (Lexicomp; DiPiro).
- C. Oxazepam: Tempting because it belongs to the same class and appears in comparisons with diazepam. It is incorrect because oxazepam relies more on conjugation and is not the classic lipophilic prolonged-half-life answer in aging; the single clue is the question asking for the best body-fat example (Lexicomp; AHFS).
- D. Temazepam: Tempting because it is also used for sleep and may seem likely to cause carryover. It is incorrect because the strongest pharmacokinetic teaching point remains diazepam, not temazepam, for increased fat distribution and prolonged half-life in older adults (Lexicomp; DiPiro).
2. Correct answer: B — Cockcroft-Gault or the drug-specific dosing estimate should be reviewed because low muscle mass may mask reduced kidney function.
- A: Tempting because clinicians often glance at whether SCr is above or below 1 mg/dL. It is incorrect because serum creatinine alone can be misleading in low-muscle-mass older adults; the discriminating clue is 84 years old and 48 kg (Lexicomp; FDA labeling conventions for many renal-dose drugs; DiPiro).
- B: Tempting because it sounds more work-intensive, but it is correct because medication dosing should use the dosing-standard renal estimate, commonly Cockcroft-Gault, especially in frail older adults where SCr may overestimate function (Lexicomp; Clinical Pharmacology; DiPiro).
- C: Tempting because the patient is not yet symptomatic. It is incorrect because renal dose problems are often detected before toxicity becomes obvious; the single clue is the presence of renally relevant drugs in a frail patient (Lexicomp; AHFS).
- D: Tempting because eGFR appears on lab reports and is clinically useful. It is incorrect because the exam asks for a drug-dosing principle, and many dosing references remain tied to Cockcroft-Gault or drug-specific labeling rather than a universal eGFR rule (FDA labeling; Lexicomp).
3. Correct answer: B — Recommend renal-function-based reassessment of gabapentin with dose reduction or interval extension and monitor sedation/falls.
- A: Tempting because serum creatinine appears normal and continuing the medication avoids undertreating pain. It is incorrect because 44 kg frailty and CKD make hidden renal impairment likely, and gabapentin is renally cleared; the discriminating clue is dizziness with near-falls plus low body weight (Lexicomp; AHFS).
- B: Tempting because it is more conservative and targeted, and it is correct because gabapentin exposure rises as renal clearance falls; the proper pharmacist action is to reassess the dose using renal guidance and monitor sedation and falls risk (Lexicomp; FDA labeling; DiPiro).
- C: Tempting because neuropathy can remain undertreated and clinicians may chase symptom control. It is incorrect because the immediate problem is possible accumulation toxicity, not treatment failure; the single clue is new dizziness and near-falls (Lexicomp).
- D: Tempting because pregabalin is a closely related alternative and keeping class effect may seem reasonable. It is incorrect because pregabalin is also renally cleared, so switching without renal reassessment recreates the same PK risk; the discriminator is same therapeutic neighborhood but same renal dependence (Lexicomp; Clinical Pharmacology).
4. Correct answer: B — Reduced total body water leading to smaller Vd for a hydrophilic drug.
- A: Tempting because increased body fat is a famous aging change. It is incorrect because gentamicin is hydrophilic, so fat expansion is not the main determinant; the discriminating clue is the hydrophilic IV drug context (Lexicomp; DiPiro).
- B: Tempting because it fits the body-composition model, and it is correct because reduced total body water can reduce Vd and raise concentration after a standard dose of a hydrophilic drug such as gentamicin (Lexicomp; AHFS).
- C: Tempting if you remember hepatic metabolism facts generally. It is incorrect because first-pass metabolism is irrelevant for an IV aminoglycoside; the key clue is route of administration (Lexicomp).
- D: Tempting only if one misreads low serum creatinine as enhanced kidney function. It is incorrect because low SCr in frailty does not imply improved clearance, and the first-dose question points toward Vd rather than renal accumulation (DiPiro; Clinical Pharmacology).
5. Correct answer: B — Phase I metabolism and hepatic blood flow can be reduced with aging, prolonging diazepam exposure.
- A: Tempting because liver enzymes are commonly used as shorthand for liver status. It is incorrect because normal AST/ALT do not prove preserved drug-metabolizing capacity or hepatic blood flow; the clue is persistent sedation despite normal labs (Lexicomp; DiPiro).
- B: Tempting because it sounds mechanistic, and it is correct because diazepam is a classic example of prolonged exposure in older adults due to reduced oxidative metabolism and distribution changes (Lexicomp; 2023 AGS Beers Criteria; DiPiro).
- C: Tempting because oral absorption problems are easy to overapply. It is incorrect because aging does not cause universal poor oral benzodiazepine absorption, and that would not explain next-day accumulation (AHFS; DiPiro).
- D: Tempting because diazepam is familiar and a lower dose may look reasonable. It is incorrect because lipophilic drugs do not clear faster in aging; increased fat distribution generally prolongs their half-life, and lorazepam is often PK-preferred if one must use a benzodiazepine (Lexicomp; AHFS).
6. Correct answer: B — Clarify renal and patient-specific dosing criteria, especially for renally sensitive agents, before assuming standard doses are appropriate.
- A: Tempting because SCr of 1.0 mg/dL may appear acceptable to a busy clinician. It is incorrect because age 87, weight 49 kg, CKD history, and recent dehydration all increase the chance that true dosing function is lower than assumed; the discriminating clue is the frail post-illness transition (Lexicomp; FDA labeling; DiPiro).
- B: Tempting because it requires extra verification, and it is correct because the pharmacist’s transition-of-care role is to reconcile dosing using renal and patient-specific criteria rather than rubber-stamp the discharge list (Lexicomp; ASHP transitions-of-care principles; FDA labeling for renal dose-sensitive drugs).
- C: Tempting because the regimen may be risky and full interruption feels safer. It is incorrect because it exceeds what is usually the highest-value immediate action and may cause harm such as undertreated atrial fibrillation; the clue is to clarify and collaborate, not to stop everything reflexively (scope-appropriate geriatric pharmacist practice; Lexicomp).
- D: Tempting because hepatically cleared drugs may seem simpler. It is incorrect because not every agent has a straightforward substitute and the right first step is to assess whether current therapy can be dose-adjusted safely; the clue is “most appropriate at transition of care” (DiPiro; Lexicomp).
7. Correct answer: B — Lorazepam 0.5 mg nightly because conjugation is relatively preserved compared with oxidation.
- A: Tempting because a long-acting drug may sound smoother and more effective. It is incorrect because clonazepam remains a problematic long-acting benzodiazepine in older adults, and the specific PK discriminator here is relative preservation of conjugation, not smoother symptom control (Lexicomp; Beers Criteria).
- B: Tempting because lorazepam is a familiar “safer if unavoidable” answer, and it is correct because it relies more on Phase II conjugation, which is relatively preserved with aging compared with oxidative metabolism (Lexicomp; AHFS; DiPiro).
- C: Tempting because chlordiazepoxide is another benzodiazepine and some may confuse metabolite properties. It is incorrect because it is not the PK-preferred option in older adults and has long-acting features that can worsen accumulation; the clue is the question asking for the best pharmacokinetic alternative (Lexicomp).
- D: Tempting because dose splitting can sometimes reduce peak effects. It is incorrect because dividing diazepam does not fix its prolonged half-life and active-metabolite burden in aging; the single clue is that the underlying problem is oxidative long-acting exposure, not just dose timing (DiPiro; Lexicomp).
8. Correct answer: A — Gabapentin accumulation from reduced renal clearance plus diazepam prolongation from lipophilic distribution and reduced Phase I metabolism.
- A: Tempting because it combines two mechanisms rather than forcing a single cause, and it is correct because the case is intentionally multimodal: gabapentin is renally cleared, whereas diazepam is prolonged by lipophilic distribution and oxidative metabolism changes; the discriminating clue is morning somnolence plus CKD and diazepam exposure together (Lexicomp; DiPiro; Beers Criteria).
- B: Tempting because first-pass metabolism and reduced body water are real PK concepts. It is incorrect because gabapentin is not the classic first-pass issue, and diazepam’s major aging pattern is increased fat distribution plus reduced Phase I metabolism rather than reduced body water (Lexicomp).
- C: Tempting because metoprolol can contribute to fatigue or dizziness. It is incorrect because the stem’s strongest PK signals point to gabapentin and diazepam; the clue is CKD plus a long-acting lipophilic sedative rather than bradycardia-focused beta-blocker toxicity (Clinical Pharmacology; Lexicomp).
- D: Tempting because multiple oral drugs are present. It is incorrect because age-related absorption failure is not the best shared explanation for somnolence and unsteadiness in this case; the single clue is the classic renal plus sedative PK combination (DiPiro; AHFS).
Keep going with the full BCGP Prep Course (BCGP)
You just studied the way members do, in the same lesson interface. Full access unlocks every lesson, the question bank and flashcards for a full year.
One payment · 1 year of access · No auto-renewal